Related Experiment Video
Updated: May 17, 2026
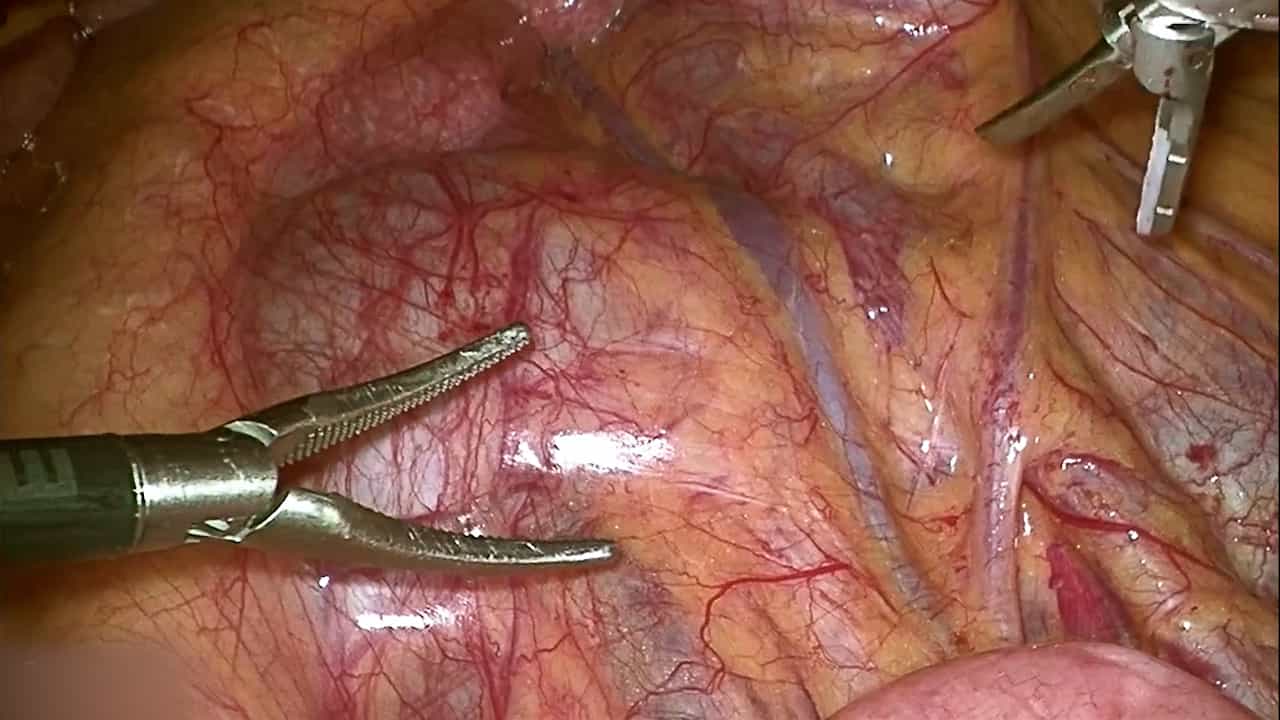

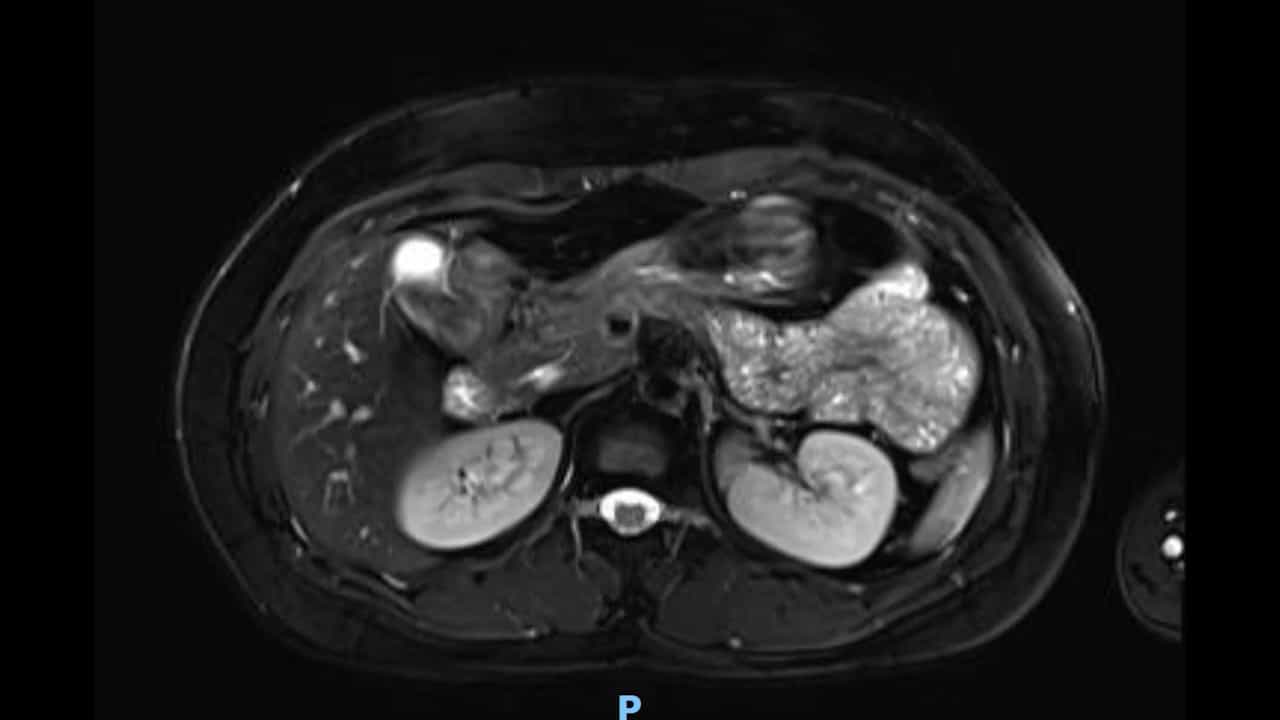
Transmesenteric Laparoscopic Pyeloplasty in Trendelenburg Position for Horseshoe Kidney with Hydronephrosis
Published on: July 8, 2025
[Laparoscopic pyeloplasty in pediatric patients: our experience]
S Fuentes Carretero1, D Cabezalí Barbancho, Andrés Gómez Fraile
1Servicio de Cirugía Pediátrica, Hospital Universitario 12 de Octubre, Madrid. sarafuentesc@yahoo.es

Insights
Laparoscopic pyeloplasty is effective for ureteropelvic junction obstruction. Technical refinements reduced surgical time and complications, showing improved outcomes with experience.
Area of Science:
- Urology
- Minimally Invasive Surgery
- Pediatric Surgery
Context:
- Ureteropelvic junction (UPJ) obstruction is a common cause of pediatric kidney issues.
- Open pyeloplasty has been the traditional treatment, but minimally invasive approaches are gaining traction.
- Laparoscopic pyeloplasty offers a less invasive alternative for UPJ obstruction.
Purpose:
- To present initial experiences with laparoscopic pyeloplasty.
- To evaluate the impact of specific technical modifications on surgical outcomes.
- To compare early and late results of laparoscopic pyeloplasty for UPJ obstruction.
Summary:
- A retrospective chart review of 13 patients undergoing laparoscopic pyeloplasty for UPJ obstruction was conducted.
- Patients were stratified into early and late groups, with the latter benefiting from a laterocolic approach and modified ureteric stenting.
- Surgical time decreased from a mean of 184 to 142 minutes, and complication rates were reduced in the later group.
Impact:
- Laparoscopic pyeloplasty demonstrates efficacy comparable to open surgery for UPJ obstruction.
- Surgical experience and technical advancements significantly improve outcomes and reduce complications.
- This minimally invasive technique offers a viable alternative for managing UPJ obstruction.
Abstract:
The aim of this essay is to present our initial experience with laparoscopic pyeloplasty and highlight how some specific technical changes allowed us to improve our results. We performed a chart review of the patients that underwent laparoscopic pyeloplasty in our institution. We included patients older than 6 months old with proved stenosis of the ureteropelvic junction. We compared our first patients with the last ones in which we performed laterocolic approach in all left pyeloplasties and included a modification of the technique to place an external ureteric stent. We performed 13 laparoscopic pyeloplasties, 8 male patients and 5 female. There were 3 right pyeloplasties (23%) and 10 left ones (77%). We performed transmesocolic approach in 2 cases (left) and laterocolic approach in 11. Mean surgical time was 184 minutes in the first 8 cases and 142 in the 5 last ones. We had three cases of complications in the first group, two stents migrated to ureter and one postsurgical infection. In the last cases we had a postoperative bleeding. Laparoscopic approach is an effective option for pyeloplasty with similar results to those of the open approach in spite of a longer surgical time. Experience and specific surgical details allow us to reduce complication rate and surgical time.