Related Experiment Video
Updated: May 5, 2026


Use of Ultra-high Field MRI in Small Rodent Models of Polycystic Kidney Disease for In Vivo Phenotyping and Drug Monitoring
Published on: June 23, 2015
Tolvaptan in patients with autosomal dominant polycystic kidney disease
Vicente E Torres1, Arlene B Chapman, Olivier Devuyst
1Division of Nephrology and Hypertension, Department of Internal Medicine, Mayo Clinic, Rochester, MN 55905, USA. torres.vicente@mayo.edu

Background:
The course of autosomal dominant polycystic kidney disease (ADPKD) is often associated with pain, hypertension, and kidney failure. Preclinical studies indicated that vasopressin V(2)-receptor antagonists inhibit cyst growth and slow the decline of kidney function.
Methods:
In this phase 3, multicenter, double-blind, placebo-controlled, 3-year trial, we randomly assigned 1445 patients, 18 to 50 years of age, who had ADPKD with a total kidney volume of 750 ml or more and an estimated creatinine clearance of 60 ml per minute or more, in a 2:1 ratio to receive tolvaptan, a V(2)-receptor antagonist, at the highest of three twice-daily dose regimens that the patient found tolerable, or placebo. The primary outcome was the annual rate of change in the total kidney volume. Sequential secondary end points included a composite of time to clinical progression (defined as worsening kidney function, kidney pain, hypertension, and albuminuria) and rate of kidney-function decline.
Results:
Over a 3-year period, the increase in total kidney volume in the tolvaptan group was 2.8% per year (95% confidence interval [CI], 2.5 to 3.1), versus 5.5% per year in the placebo group (95% CI, 5.1 to 6.0; P<0.001). The composite end point favored tolvaptan over placebo (44 vs. 50 events per 100 follow-up-years, P=0.01), with lower rates of worsening kidney function (2 vs. 5 events per 100 person-years of follow-up, P<0.001) and kidney pain (5 vs. 7 events per 100 person-years of follow-up, P=0.007). Tolvaptan was associated with a slower decline in kidney function (reciprocal of the serum creatinine level, -2.61 [mg per milliliter](-1) per year vs. -3.81 [mg per milliliter](-1) per year; P<0.001). There were fewer ADPKD-related adverse events in the tolvaptan group but more events related to aquaresis (excretion of electrolyte-free water) and hepatic adverse events unrelated to ADPKD, contributing to a higher discontinuation rate (23%, vs. 14% in the placebo group).
Conclusions:
Tolvaptan, as compared with placebo, slowed the increase in total kidney volume and the decline in kidney function over a 3-year period in patients with ADPKD but was associated with a higher discontinuation rate, owing to adverse events. (Funded by Otsuka Pharmaceuticals and Otsuka Pharmaceutical Development and Commercialization; TEMPO 3:4 ClinicalTrials.gov number, NCT00428948.).
More Related Videos
 08:46
Implementing Patch Clamp and Live Fluorescence Microscopy to Monitor Functional Properties of Freshly Isolated PKD Epithelium
Published on: September 1, 2015
 08:44
Continuous IV Infusion is the Choice Treatment Route for Arginine-vasopressin Receptor Blocker Conivaptan in Mice to Study Stroke-evoked Brain Edema
Published on: September 1, 2016
Related Concept Videos
 01:28
Antihypertensive Drugs: Potassium-Sparing Diuretics
 01:15
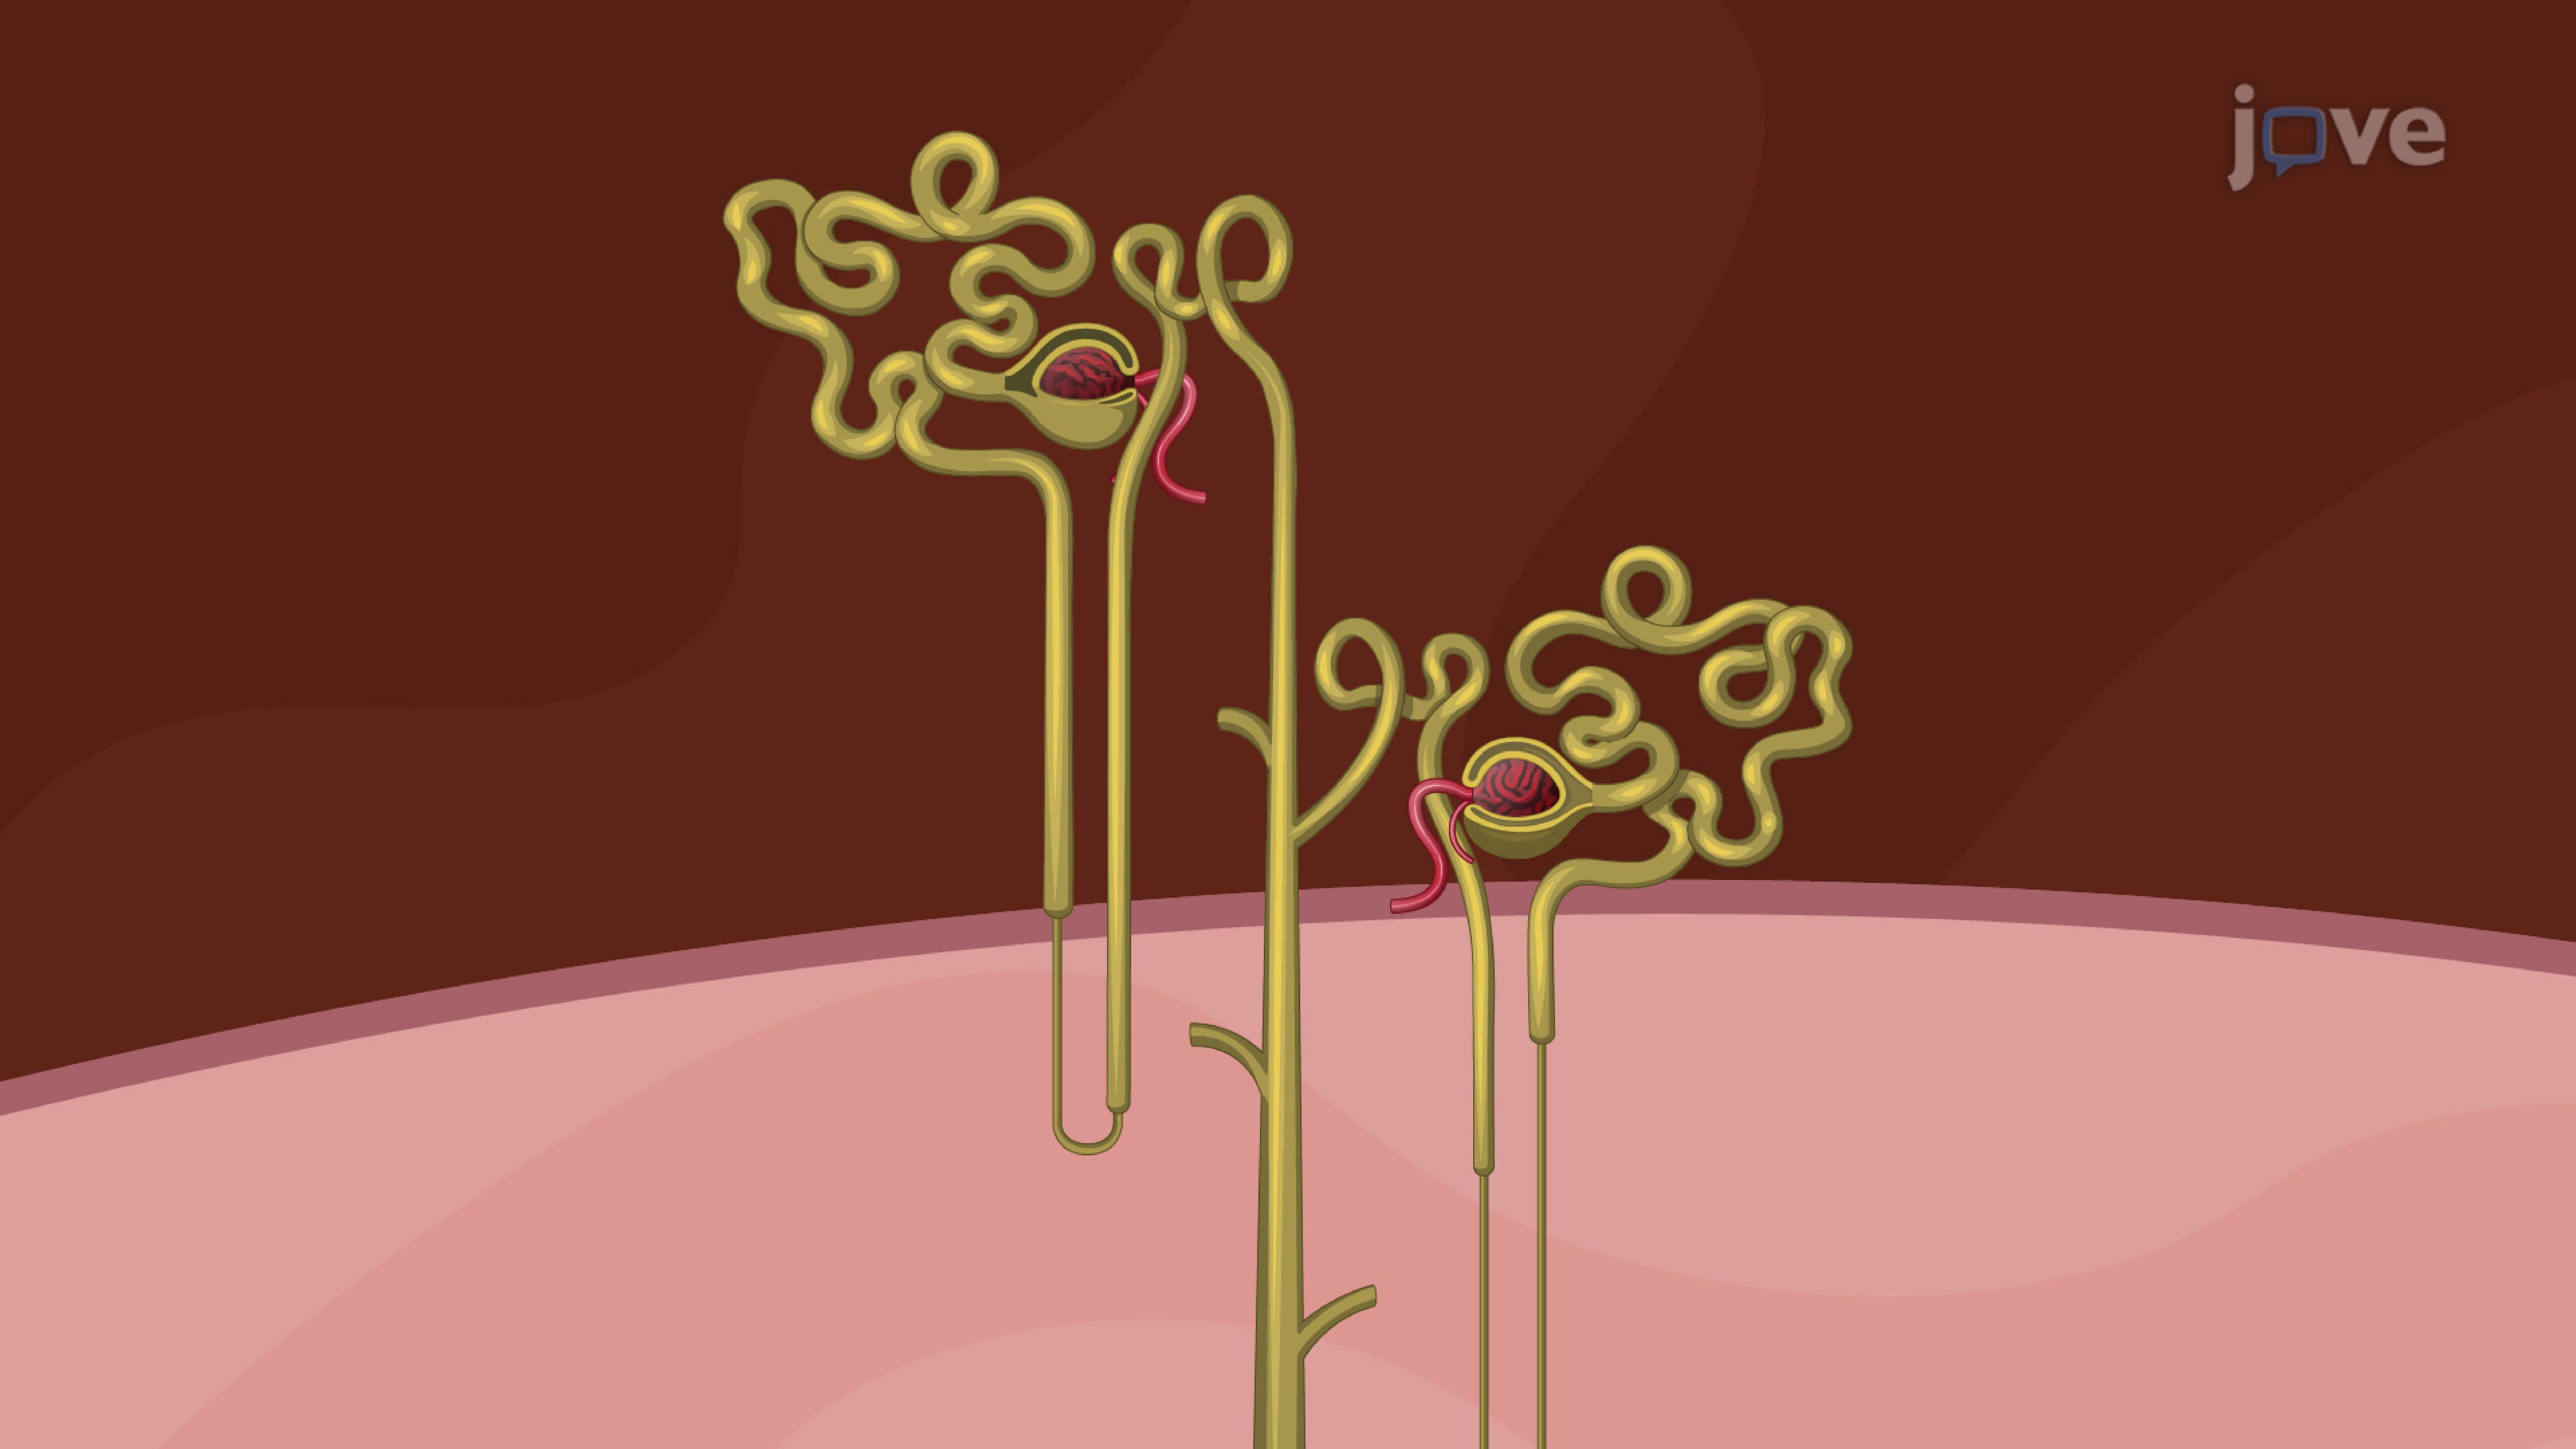
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:25
Renal Drug Excretion: Tubular Reabsorption
 01:28
Renal Drug Excretion: Tubular Secretion
 01:06
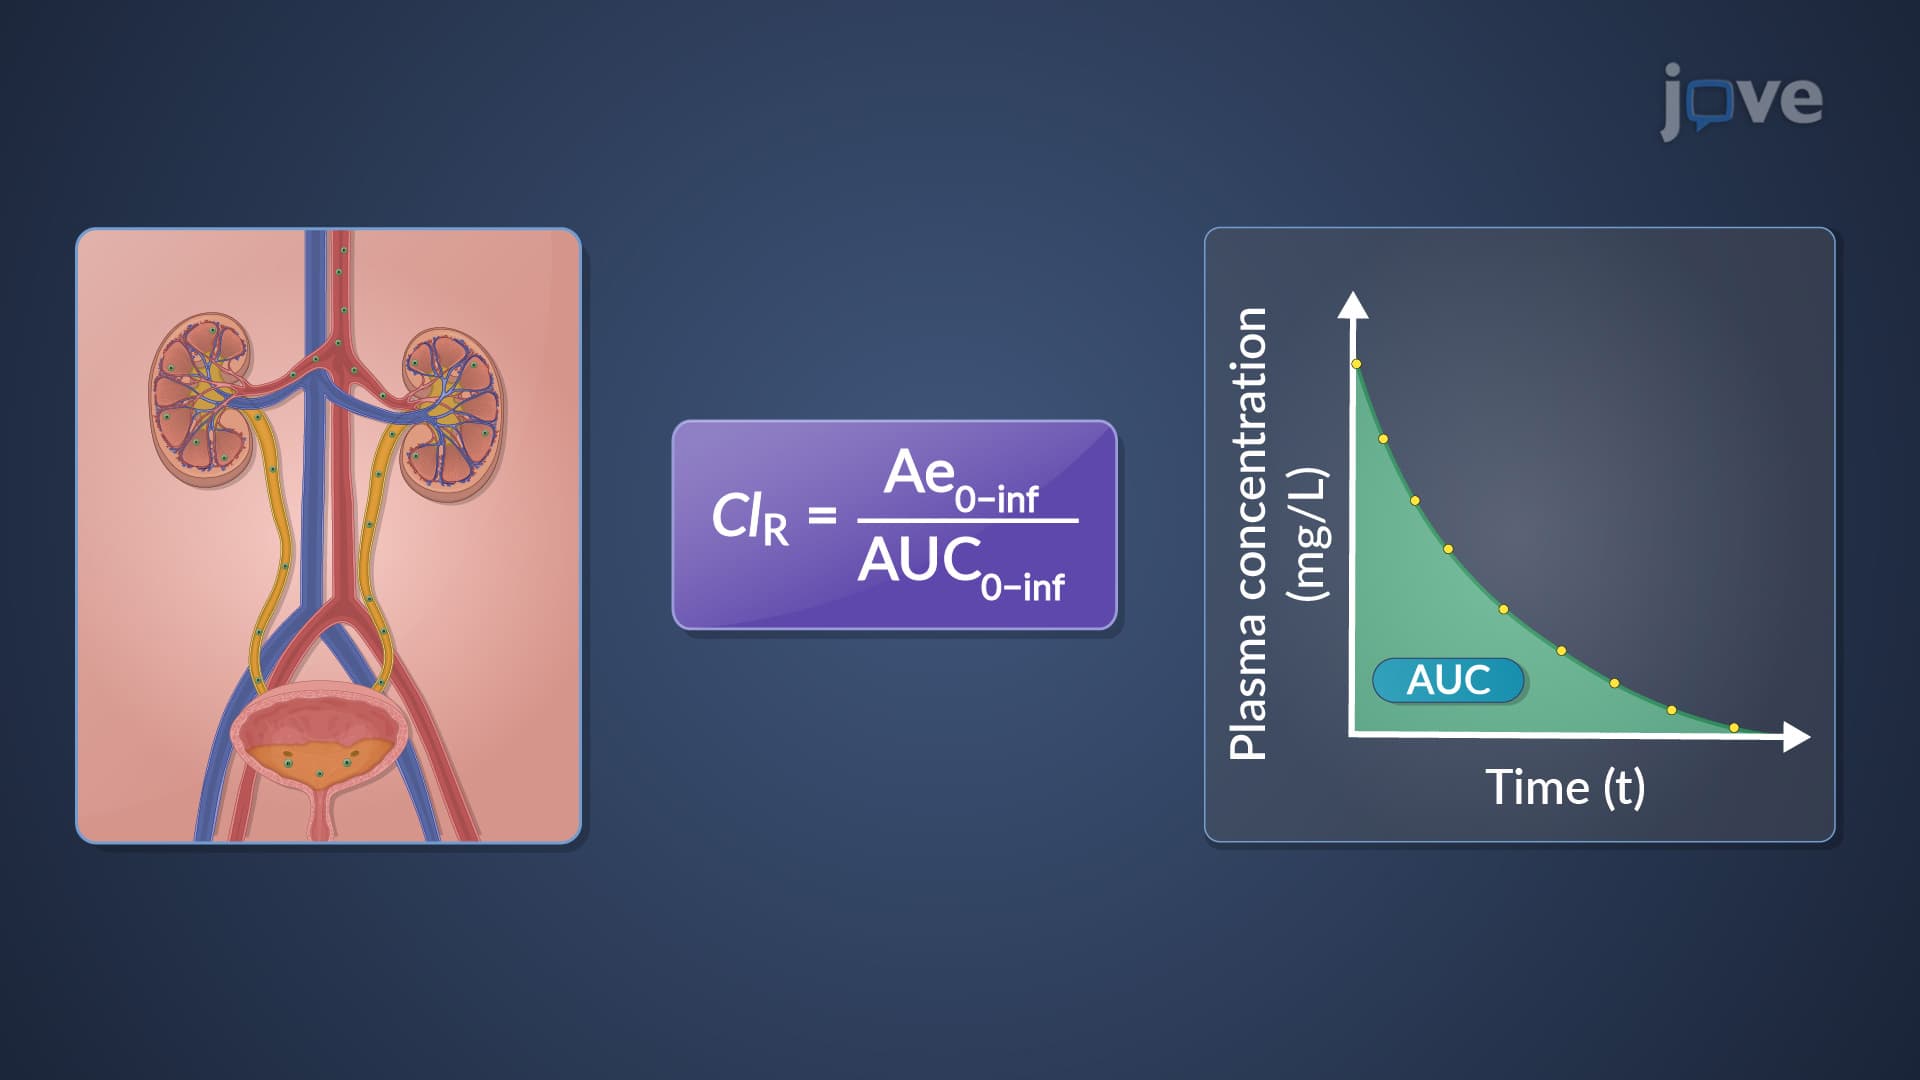
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention