Related Experiment Video
Updated: May 17, 2026

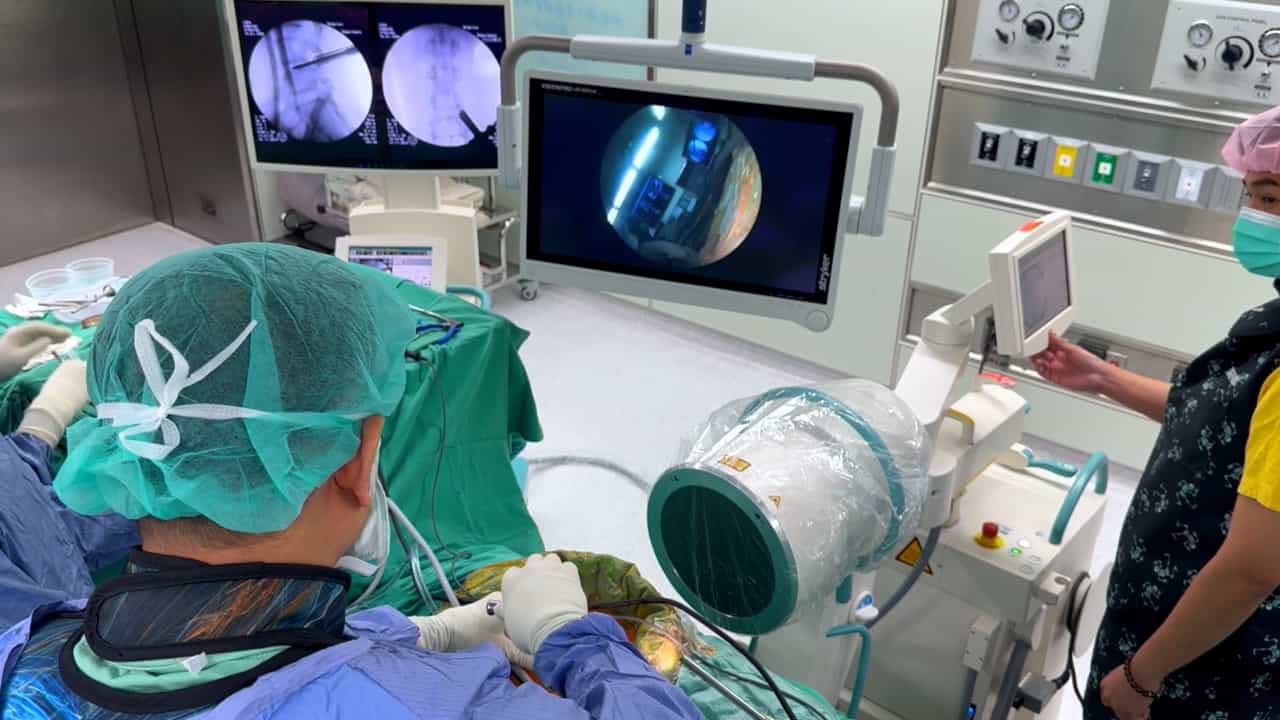
C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
Grade 2 spondylolisthesis at L4-5 treated by XLIF: safety and midterm results in the "worst case scenario"
W B Rodgers1, Jeffrey A Lehmen, Edward J Gerber
1Spine Midwest, Inc., Suite 301, 200 St. Mary's Medical Plaza, Jefferson City, MO 65101, USA.

Unlabelled:
Spondylolisthesis is one of the most common indications for spinal surgery. However, no one approach has been proven to be more effective in treating spondylolisthesis. Recent advances in minimally invasive spine technology have allowed for different approaches to be applied to this indication, notably extreme lateral interbody fusion (XLIF). The risk, however, of using XLIF in treating grade II spondylolisthesis is the ventral position of the lumbar plexus, particularly at L4-5.
Objective:
This study reports the safety and midterm clinical and radiographic outcomes of patients with grade II lumbar spondylolisthesis treated with XLIF.
Methods:
63 patients with grade II spondylolisthesis and spinal stenosis were treated with XLIF and were available for 12-month followup. Of those, 61 (97%) were treated at L4-5. Clinical (VAS, complications, and reoperation rate) and radiographic (anterolisthesis, disk height, and fusion) parameters were assessed.
Study Design:
Data were collected via a prospective registry and analyzed retrospectively.
Results:
Sixty-three patients were available for evaluations at least one year postoperatively. Average pain (visual analog scale) decreased from a score of 8.7 at baseline to 2.2 at 12 months postoperatively. Average anterior slippage was reduced by 73% and was well maintained. Average disk height (4.6 mm pre-op and 9.0 mm post-op) nearly doubled after surgery. Slight settling (average 1.3 mm) occurred over the twelve-month follow-up period. There were no neural injuries and no nonunions noted.
Conclusions:
XLIF is a safe and effective minimally invasive treatment alternative for grade II spondylolisthesis. Real-time neurological monitoring and attention to technique are mandatory.