Related Experiment Video
Updated: May 16, 2026

Assessment of Chimeric Antigen Receptor T Cell-Associated Toxicities Using an Acute Lymphoblastic Leukemia Patient-Derived Xenograft Mouse Model
Published on: February 10, 2023
A risk-adapted protocol for delayed administration of filgrastim after high-dose chemotherapy and autologous stem
Amit Khot1, Michael Dickinson, Kerrie Stokes
1Department of Haematology, Peter MacCallum Cancer Centre, Melbourne, Victoria, Australia. amit.khot@petermac.org

Introduction:
The routine use of recombinant human granulocyte-colony stimulating factor (rhG-CSF) after high-dose chemotherapy and autologous stem cell transplantation (auto-SCT) is associated with increased costs. We prospectively explored a strategy that used prophylactic delayed filgrastim only in patients with risk factors.
Patients And Methods:
This sequential cohort analysis compared the outcomes of consecutive patients, treated on the risk-adapted protocol (RAP) (risk factors: prior febrile neutropenia; age >60 years; and CD34+ cell infused dose of <2 × 10(6/)/kg), who received filgrastim from day +6 after auto-SCT with a historical cohort (historical day-1 cohort [HD1]), who received filgrastim from day +1.
Results:
Eighty-two patients were treated in the RAP cohort and compared with 115 patients in the HD1 cohort. There were no differences in median age (55 years) or median CD34+ cell dose (5.21 × 10(6)/kg [range, 2-62.2 × 10(6)/kg] vs. 5.24 × 10(6)/kg [range, 2.4-29.8 × 10(6)/kg]). Filgrastim was used for 6 fewer days in the RAP cohort (median 5 days [range, 0-11 days] vs. 11 days [range, 9-47 days]). There was a small absolute but significant difference in median time to neutrophil recovery in the HD1 cohort for the whole group, 10 days (range, 8-46 days) vs. 11 days (range, 9-22 days) (P = .03) and in patients with myeloma; 10 days (range, 9-14 days) vs. 11 days (range, 9-18 days) (P < .0001) as compared to the RAP cohort. There was no difference in median inpatient duration, 13 days (range, 10-26 days) vs. 12 days (range, 1-38 days) (P = .22) and 3-year survival (79% vs. 83% [P = .43]) between HD1 and RAP cohorts respectively.
Conclusions:
The use of a RAP to identify patients likely to benefit from prophylactic filgrastim is safe and results in cost savings. Patients with myeloma benefit from earlier introduction of filgrastim in terms of neutrophil recovery; this disease-specific observation is an important consideration for future studies.
More Related Videos
 11:55
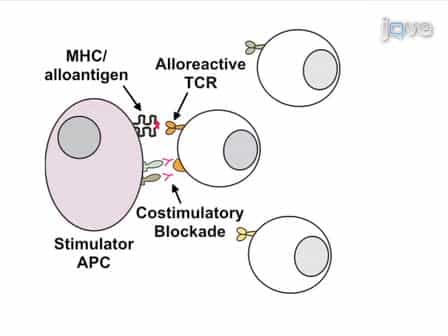
Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
 08:31
Murine Model of Leukemia Relapse to Induction Chemotherapy for Acute Lymphoblastic Leukemia
Published on: October 17, 2025
Related Concept Videos
 01:21
Stem Cell Therapy for Tissue Regeneration
Types of Stem Cells used in Stem Cell Therapy
The two main cell types that...
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy the...