Related Experiment Video
Updated: May 16, 2026
A Reference Broth Microdilution Method for Dalbavancin In Vitro Susceptibility Testing of Bacteria that Grow Aerobically
Published on: September 9, 2015
Systematic review and meta-analysis of vancomycin-induced nephrotoxicity associated with dosing schedules that
S J van Hal1, D L Paterson, T P Lodise
1Department of Microbiology & Infectious Diseases, Royal Prince Alfred Hospital, Sydney, Australia. Sebastian.vanhal@sswahs.nsw.gov.au

Abstract:
In an effort to maximize outcomes, recent expert guidelines recommend more-intensive vancomycin dosing schedules to maintain vancomycin troughs between 15 and 20 mg/liter. The widespread use of these more-intensive regimens has been associated with an increase in vancomycin-induced nephrotoxicity reports. The purpose of this systematic literature review is to determine the nephrotoxicity potential of maintaining higher troughs in clinical practice. All studies pertaining to vancomycin-induced nephrotoxicity between 1996 and April 2012 were identified from PubMed, Embase, Cochrane Controlled Trial Registry, and Medline databases and analyzed according to Cochrane guidelines. Of the initial 240 studies identified, 38 were reviewed, and 15 studies met the inclusion criteria. Overall, higher troughs (≥ 15 mg/liter) were associated with increased odds of nephrotoxicity (odds ratio [OR], 2.67; 95% confidence interval [CI], 1.95 to 3.65) relative to lower troughs of <15 mg/liter. The relationship between a trough of ≥ 15 mg/liter and nephrotoxicity persisted when the analysis was restricted to studies that examined only initial trough concentrations (OR, 3.12; 95% CI, 1.81 to 5.37). The relationship between troughs of ≥ 15 mg/liter and nephrotoxicity persisted after adjustment for covariates known to independently increase the risk of a nephrotoxicity event. An incremental increase in nephrotoxicity was also observed with longer durations of vancomycin administration. Vancomycin-induced nephrotoxicity was reversible in the majority of cases, with short-term dialysis required only in 3% of nephrotoxic episodes. The collective literature indicates that an exposure-nephrotoxicity relationship for vancomycin exists. The probability of a nephrotoxic event increased as a function of the trough concentration and duration of therapy.
Insights
Higher vancomycin troughs (15-20 mg/L) increase nephrotoxicity risk. This systematic review found higher vancomycin troughs are linked to increased odds of kidney damage, emphasizing careful dosing.
Area of Science:
- Pharmacology
- Nephrology
- Clinical Pharmacy
Background:
- Recent guidelines advocate intensive vancomycin dosing (troughs 15-20 mg/L) to optimize treatment outcomes.
- Increased reports of vancomycin-induced nephrotoxicity have emerged with these intensive regimens.
Purpose of the Study:
- To systematically evaluate the nephrotoxicity risk associated with maintaining higher vancomycin trough concentrations in clinical practice.
Main Methods:
- A systematic literature review of studies published between 1996 and April 2012 was conducted.
- Searches included PubMed, Embase, Cochrane Controlled Trial Registry, and Medline databases.
- Fifteen studies met inclusion criteria for analysis according to Cochrane guidelines.
Main Results:
- Higher vancomycin troughs (≥ 15 mg/L) were significantly associated with increased odds of nephrotoxicity (OR, 2.67; 95% CI, 1.95-3.65) compared to lower troughs (<15 mg/L).
- This association persisted when analyzing initial trough concentrations and after adjusting for known risk factors.
- Increased nephrotoxicity risk was also observed with longer vancomycin therapy durations.
Conclusions:
- A clear exposure-nephrotoxicity relationship exists for vancomycin.
- Higher trough concentrations and longer treatment durations increase the probability of vancomycin-induced kidney injury.
- Vancomycin-induced nephrotoxicity is generally reversible, with rare need for dialysis.

Related Concept Videos
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:15
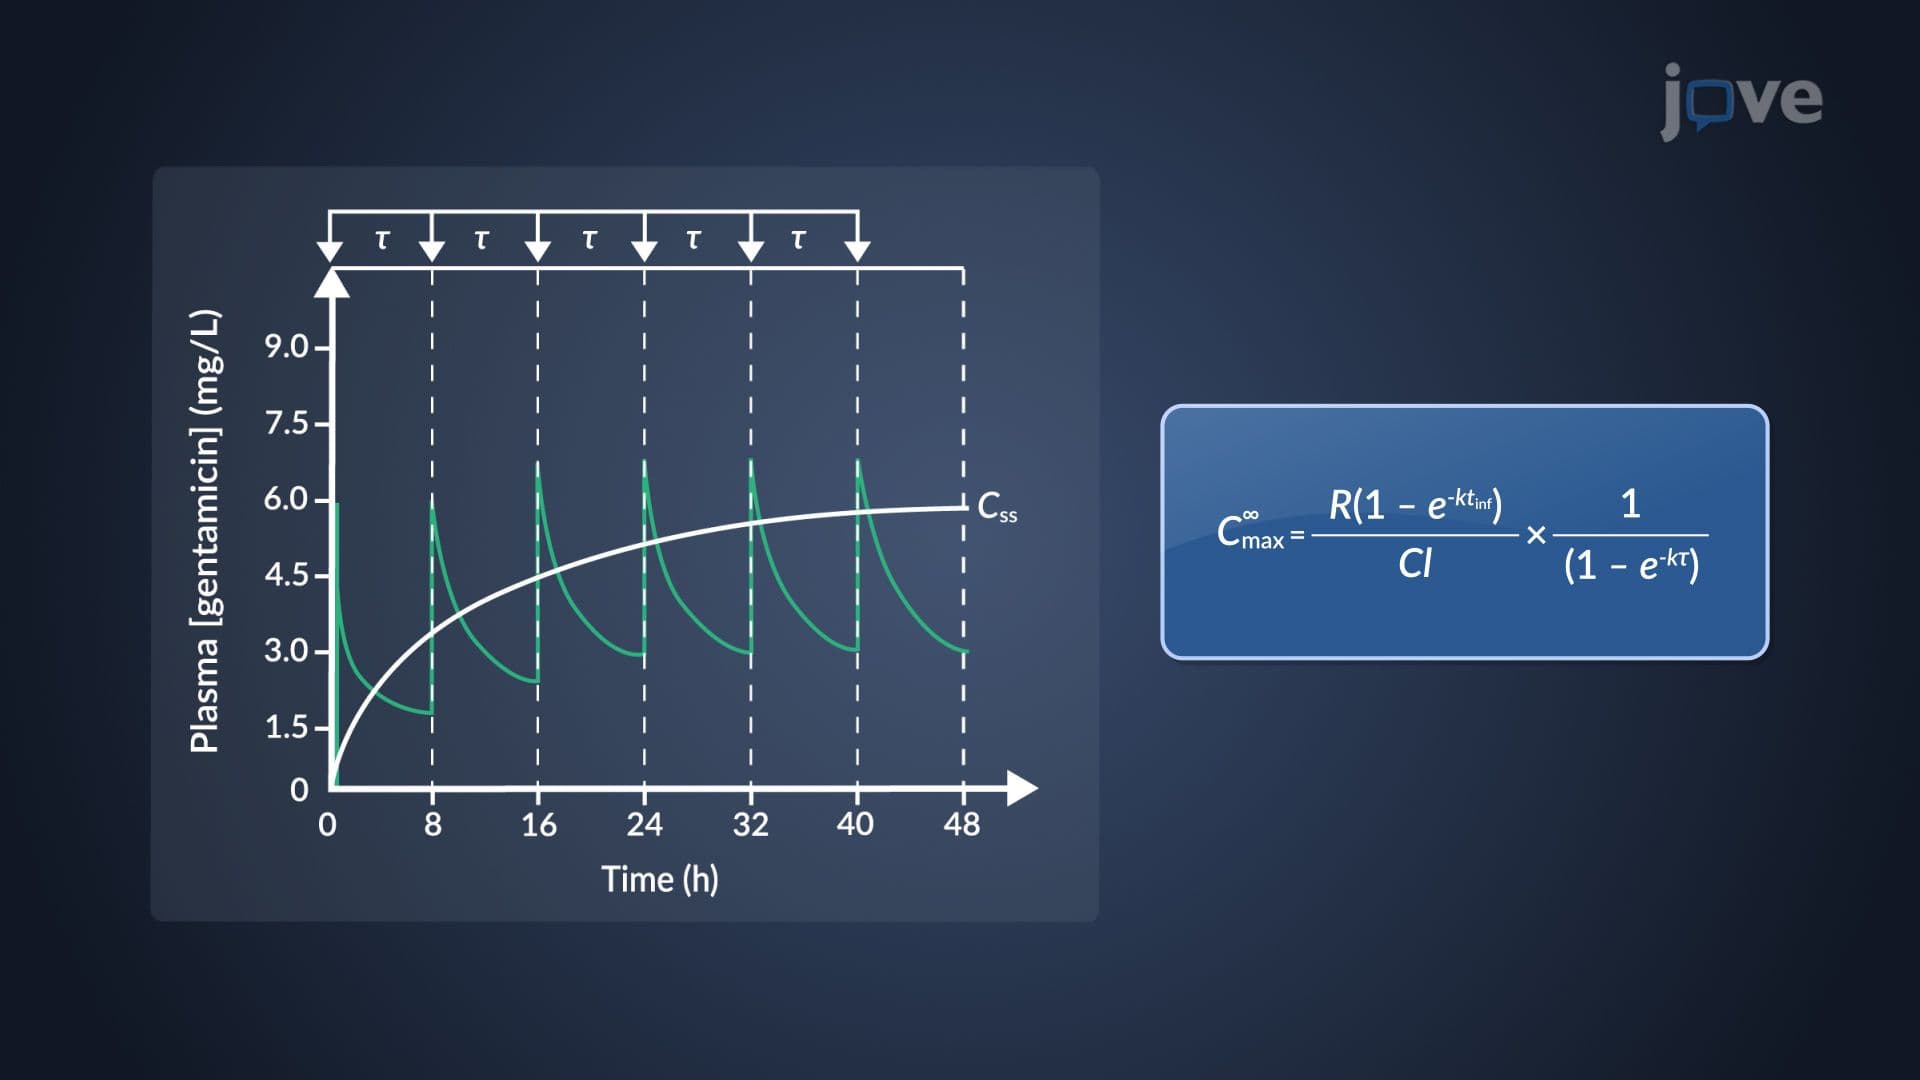
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:20
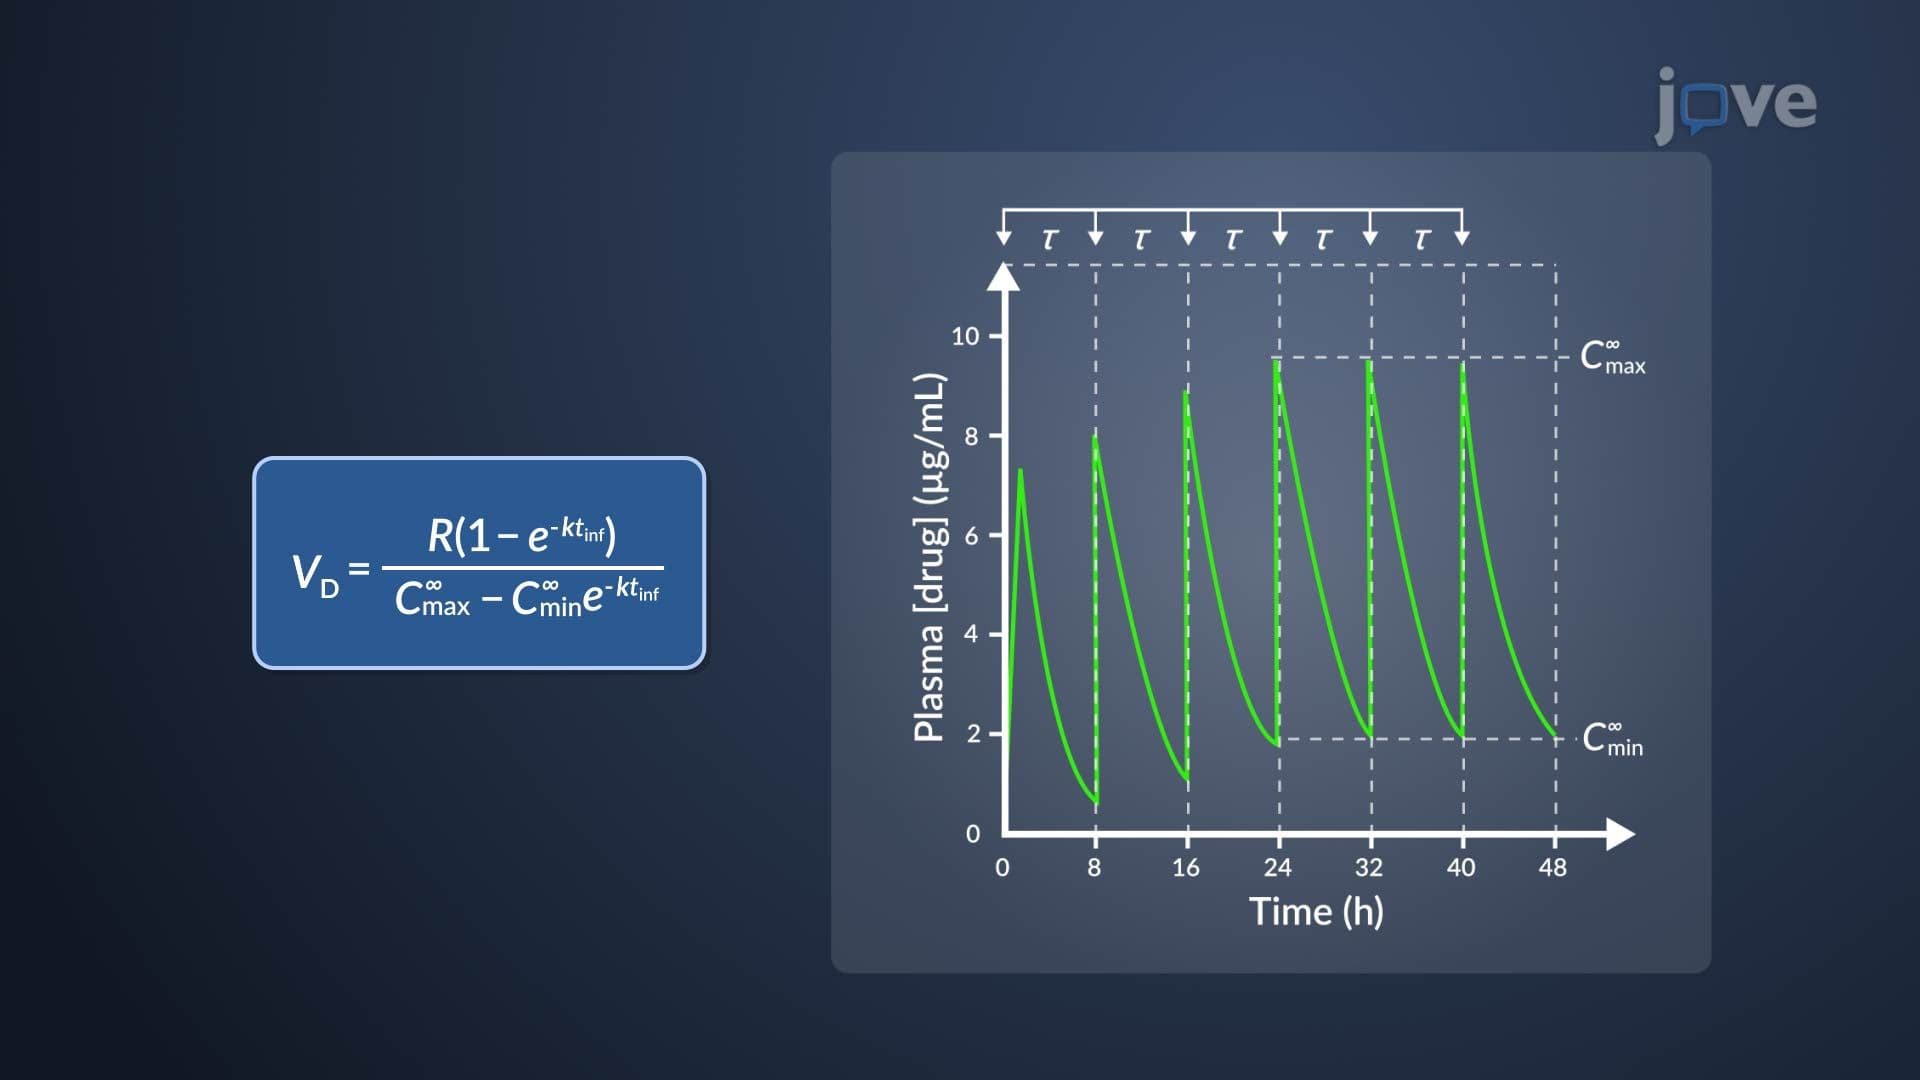
Estimation of k and VD of Aminoglycosides
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion