Related Experiment Video
Updated: May 16, 2026
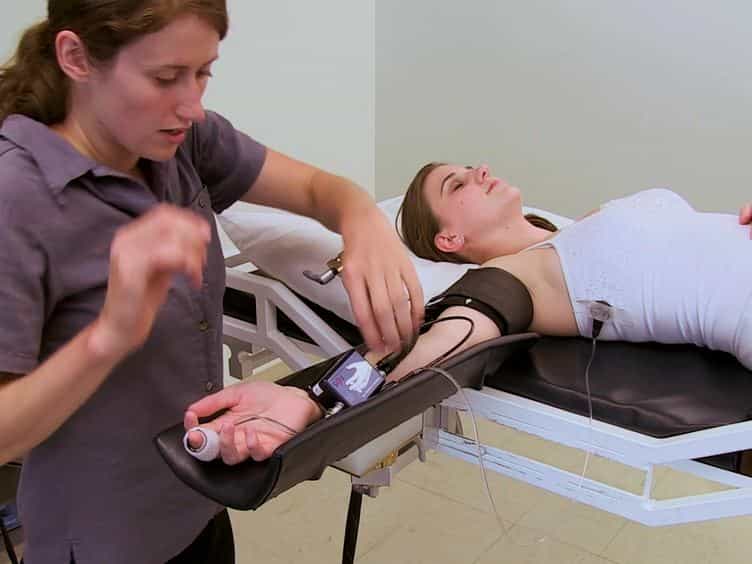

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Initial orthostatic hypotension and cerebral blood flow regulation: effect of α1-adrenoreceptor activity
Nia C S Lewis1, Philip N Ainslie, Greg Atkinson
1Centre for Heart, Lung and Vascular Health, School of Health and Exercise Sciences, Development, University of British Columbia, Kelowna, British Columbia, Canada. Nia.Lewis@ubc.ca

Abstract:
We examined the hypothesis that α(1)-adrenergic blockade would lead to an inability to correct initial orthostatic hypotension (IOH) and cerebral hypoperfusion, leading to symptoms of presyncope. Twelve normotensive humans (aged 25 ± 1 yr; means ± SE) attempted to complete a 3-min upright stand, 90 min after the administration of either α(1)-blockade (prazosin, 1 mg/20 kg body wt) or placebo. Continuous beat-to-beat measurements of middle cerebral artery velocity (MCAv; Doppler), blood pressure (finometer), heart rate, and end-tidal Pco(2) were obtained. Compared with placebo, the α(1)-blockade reduced resting mean arterial blood pressure (MAP) (-15%; P < 0.01); MCAv remained unaltered (P ≥ 0.28). Upon standing, although the absolute level of MAP was lower following α(1)-blockade (39 ± 10 mmHg vs. 51 ± 14 mmHg), the relative difference in IOH was negligible in both trials (mean difference in MAP: 2 ± 2 mmHg; P = 0.50). Compared with the placebo trial, the declines in MCAv and Pet(CO(2)) during IOH were greater in the α(1)-blockade trial by 12 ± 4 cm/s and 4.4 ± 1.3 mmHg, respectively (P ≤ 0.01). Standing tolerance was markedly reduced in the α(1)-blockade trial (75 ± 17 s vs. 180 ± 0 s; P < 0.001). In summary, while IOH was little affected by α(1)-blockade, the associated decline in MCAv was greater in the blockade condition. Unlike in the placebo trial, the extent of IOH and cerebral hypoperfusion failed to recover toward baseline in the α(1)-blockade trial leading to presyncope. Although the development of IOH is not influenced by the α(1)-adrenergic receptor pathway, this pathway is critical in the recovery from IOH to prevent cerebral hypoperfusion and ultimately syncope.
Related Concept Videos
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
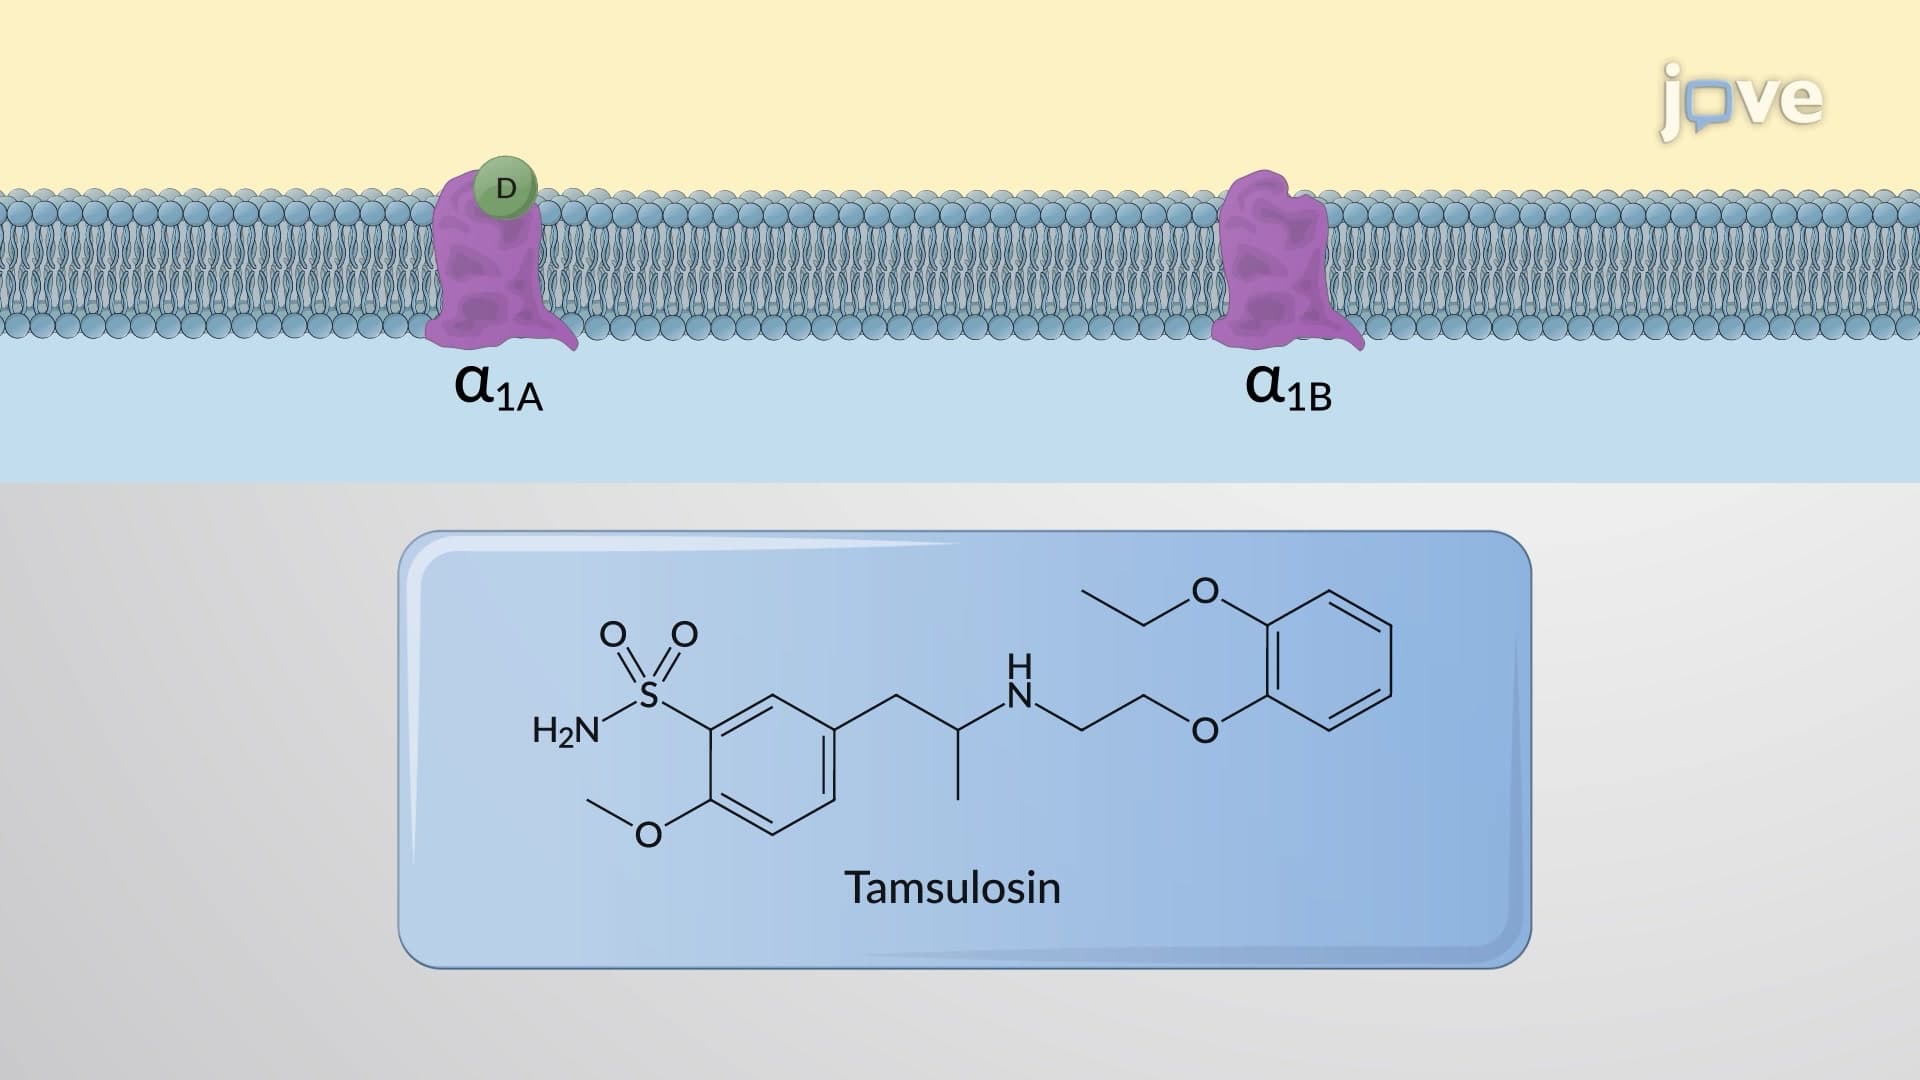
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:17
Antihypertensive Drugs: Action of β1 Blockers
 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors, which are found on postsynaptic...