Related Experiment Video
Updated: May 16, 2026
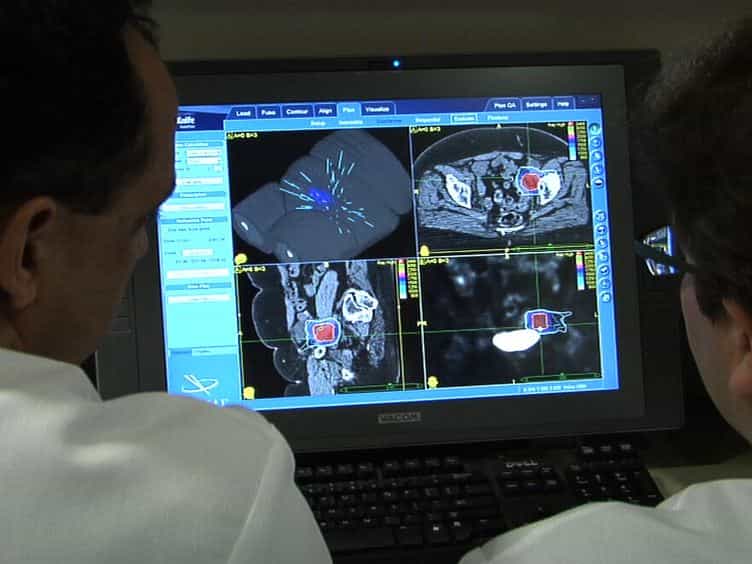

Stereotactic Radiosurgery for Gynecologic Cancer
Published on: April 17, 2012
Evaluation of quality indices during multifractionated pelvic interstitial brachytherapy for cervical cancer
Supriya Chopra1, Pragya Shukla, Siji Nojin Paul
1Department of Radiation Oncology, Advanced Centre for Treatment, Research and Education in Cancer, Tata Memorial Centre, Navi Mumbai, Maharashtra, India. schopra@actrec.gov.in

Purpose:
To evaluate the impact of needle displacements on quality indices during multifractionated pelvic interstitial brachytherapy (IBT).
Methods And Materials:
Patients undergoing boost IBT were included. Postprocedure planning and verification CT scans were obtained. Three-dimensional needle displacements were measured. Clinical target volume and organ at risk were delineated. Coverage index (CI), dose homogeneity index (DHI), dose nonuniformity ratio (DNR), V170, V200, V250, and dose received by 2cc of organs at risk were obtained at baseline. The displacements were simulated by shifting dwell positions, and dose point optimized and graphically optimized plans were generated. Wilcoxon test determined statistical significance of differences in quality indices.
Results:
Fifteen patients were included and received five fractions of IBT over 3 days. Maximum displacements were observed in caudal direction (average, 19.1mm). At baseline, CI of 0.94 (range, 0.91-0.99), DHI of 0.90 (range, 0.80-0.94), and DNR of 0.10 (range, 0.05-0.10) were attained. The CI, DHI, and DNR in Day 3 dose point optimized plans were 0.76 (range, 0.4-0.99), 0.76 (range, 0.40-0.94), and 0.23 (range, 0.06-0.64), respectively. The difference in CI, DHI, and DNR between baseline and Day 3 dose point optimized plans was statistically significant (p = 0.002, 0.007, and 0.001, respectively). Day 3 graphically optimized plans were superior to Day 3 dose point optimized plans (CI, 0.82 vs. 0.76; p = 0.01). Graphically optimized could however improve CI without compromise in DHI, DNR, V170, V200, and V250 only in patients wherein caudal displacements ≤15mm.
Conclusions:
Caudal needle displacements during multifractionated IBT cause significant deterioration of quality indices. Replanning with graphically optimized and/or needle repositioning maybe required for maintaining the quality of IBT.
More Related Videos
 08:29
Measurement of Four Uterine NK Cell Subtypes Using Multiplexed Fluorescent Immunohistochemical Staining in Women with Repeated Implantation Failure
Published on: October 25, 2024
 05:18
Radiation Planning Assistant - A Web-based Tool to Support High-quality Radiotherapy in Clinics with Limited Resources
Published on: October 6, 2023