Related Experiment Video
Updated: May 16, 2026


Evaluation of Capnography Sampling Line Compatibility and Accuracy when Used with a Portable Capnography Monitor
Published on: September 29, 2020
Changes in end-tidal carbon dioxide and volumetric carbon dioxide as predictors of volume responsiveness in
Alisha Young1, Paul E Marik, Steven Sibole
1Division of Pulmonary and Critical Care Medicine, Eastern Virginia Medical School, Norfolk, VA 23507, USA.

Objective:
The purpose of this study was to determine whether changes in PETCO2 and exhaled CO2 (VCO2) can predict fluid responsiveness after a preload challenge.
Design:
A retrospective review of prospectively recorded data.
Setting:
A medical intensive care unit of a university-affiliated tertiary care hospital.
Participants:
Mechanically ventilated patients undergoing a preload challenge.
Interventions:
In the authors' intensive care unit, fluid responsiveness is determined by a passive leg raising (PLR) maneuver and/or a 500-mL crystalloid challenge. An increase in the stroke volume index >10% as measured by a NICOM bioreactance cardiac output monitor (Cheetah Medical, Inc, Vancouver, WA) is used to determine fluid responsiveness. PETCO2 and volumetric capnography (VCO2) were monitored via a combined CO2 and flow sensor capnostat (Respironics NM3 Monitor; Philips Healthcare, Eindhoven, Netherlands). Patients were mechanically ventilated with tidal volumes controlled at 8 mL/kg, allowing for consistent minute ventilation.
Measurements And Main Results:
During the study period, 44 challenges (10 PLR and 34 fluid boluses) were performed on 34 patients. There were 24 (54%) positive "fluid" responses. PETCO2 increased by 5.9% ± 7.6% in the responders compared with 1.4% ± 4.4% in the nonresponders (p = 0.02). Similarly, VCO2 increased by 11.0% ± 8.6% in the responders compared with 0.8% ± 5.6% in the nonresponders (p = 0.001). The area under the receiver operating characteristic curve was 0.67 (95% confidence interval, 0.48-0.80) for PETCO2 and 0.79 (95% confidence interval, 0.63-0.89) for VCO2. PETCO2 and VCO2 were predictive of fluid responsiveness only in those patients without underlying lung disease. The stroke volume variation was 15.8 ± 3.7 in the responders compared with 13.6 ± 4.8 in the nonresponders (p = 0.15).
Conclusions:
Dynamic changes in PETCO2 and VCO2 may be used as adjunctive indicators of fluid responsiveness in patients without underlying lung disease.

Related Concept Videos
 01:17
Assessment of Diffusion and Perfusion
The Role of Diffusion in Respiration
Diffusion is the process by which molecules move from an area of higher concentration to an area of lower concentration. In the respiratory system, this principle...
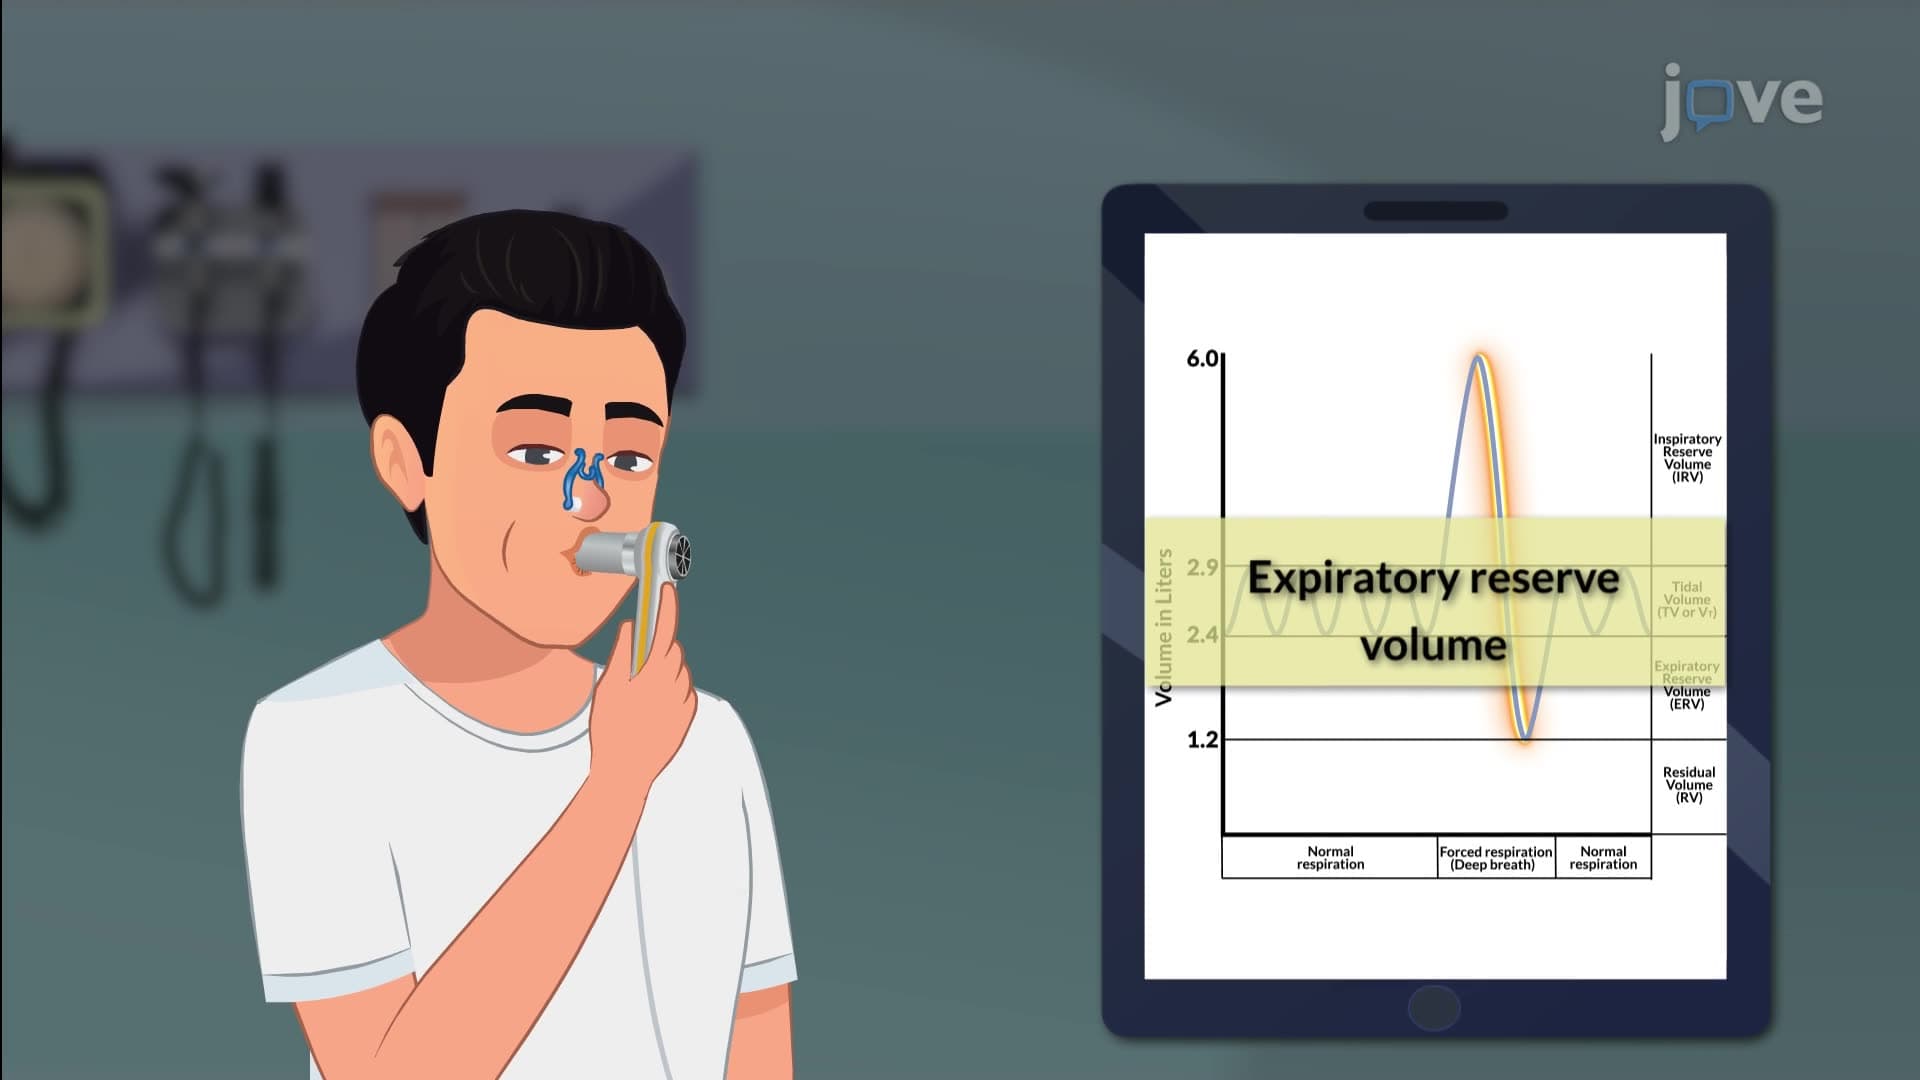 01:15
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:30
Acute Respiratory Failure-III
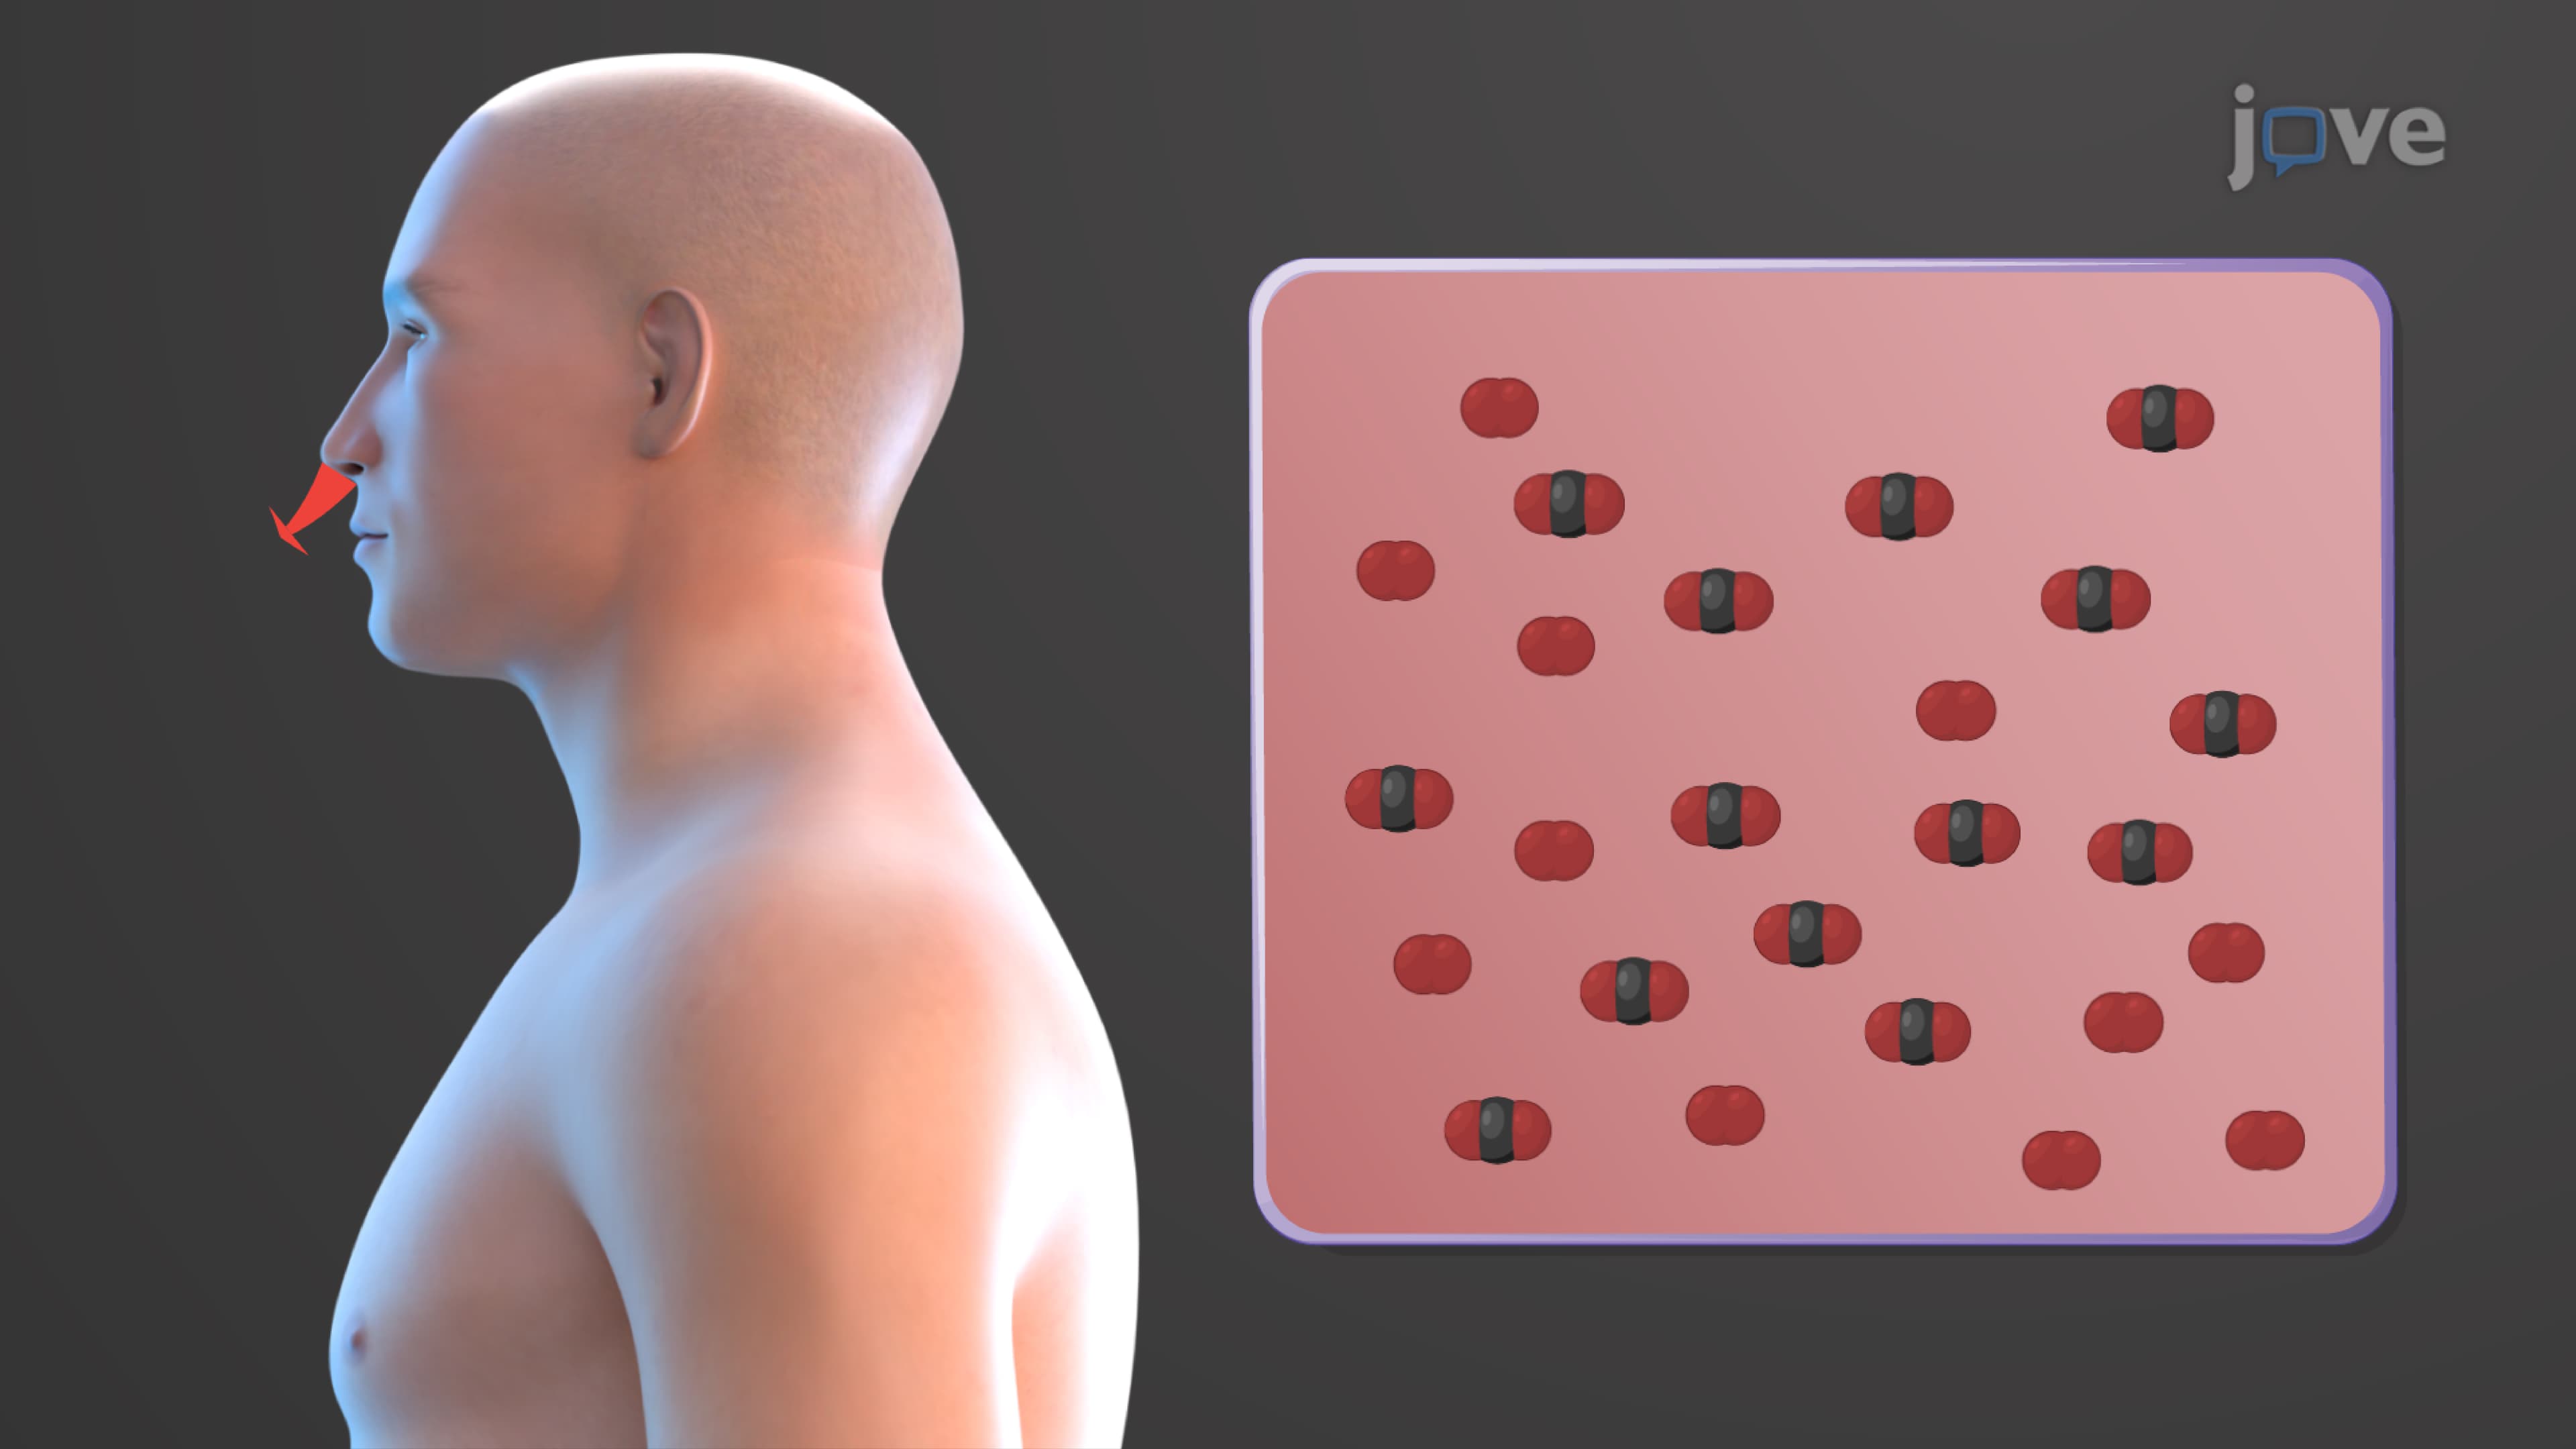 01:31
Chemical Factors Affecting Respiration Centers
CO2 has a potent influence on respiration and is strictly regulated. Under...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: