Related Experiment Video
Updated: May 16, 2026
A Methodological Approach to Non-invasive Assessments of Vascular Function and Morphology
Published on: February 7, 2015
Aneurysmal disease is associated with lower carotid intima-media thickness than occlusive arterial disease
Koen M van de Luijtgaarden1, Erik J Bakker, Ellen V Rouwet
1Department of Vascular Surgery, Erasmus University Medical Center, Rotterdam, The Netherlands.

Insights
Patients with aneurysmal disease have a lower atherosclerotic burden, indicated by common carotid artery intima-media thickness (CIMT), compared to those with occlusive arterial disease. This suggests other factors contribute to aortic aneurysm formation beyond atherosclerosis.
Area of Science:
- Vascular Biology
- Cardiovascular Medicine
- Atherosclerosis Research
Background:
- Cardiovascular risk profiles overlap between patients with aneurysmal and occlusive arterial disease.
- The precise relationship between atherosclerosis and aortic aneurysm formation remains unclear.
- Common carotid artery intima-media thickness (CIMT) serves as a key indicator of early atherosclerosis.
Purpose of the Study:
- To compare the atherosclerotic burden, measured by CIMT, between patients with aneurysmal and occlusive arterial disease.
- To investigate the role of atherosclerosis in the pathogenesis of aortic aneurysms.
Main Methods:
- A cohort of 904 patients undergoing vascular surgery between 2004 and 2011 were analyzed.
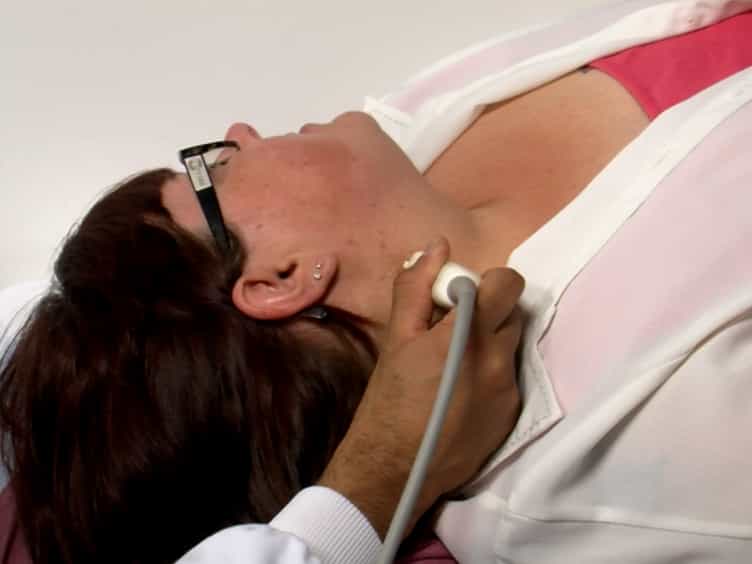
- Common carotid artery intima-media thickness (CIMT) was measured using B-mode ultrasound.
- Univariable and multivariable analyses were performed, adjusting for cardiovascular risk factors, comorbidities, and medication.
Main Results:
- Patients with aneurysmal disease exhibited a significantly lower mean CIMT (0.97 mm) compared to those with occlusive arterial disease (1.07 mm).
- After adjustment for confounding factors, a mean CIMT difference of 0.15 mm was observed between the groups (P < .001).
- The findings indicate a reduced atherosclerotic burden in individuals with aneurysmal disease.
Conclusions:
- Aneurysmal disease is associated with a lower atherosclerotic burden than occlusive arterial disease.
- These results support the hypothesis that additional pathogenic mechanisms, beyond atherosclerosis, are implicated in aortic aneurysm development.
- Further research is warranted to fully elucidate the complex interplay between atherosclerosis and aortic aneurysm formation.
Objective:
Patients with aneurysmal and occlusive arterial disease have overlapping cardiovascular risk profiles. The question remains how atherosclerosis is related to the formation of aortic aneurysms. Common carotid artery intima-media thickness (CIMT) is an easily accessible and objective marker of early atherosclerosis. The aim of the current study was to investigate whether there is a difference in atherosclerotic burden as measured by CIMT between patients with aneurysmal and those with occlusive arterial disease.
Methods:
From 2004 to 2011, the CIMT was measured using B-mode ultrasound scanning in patients undergoing vascular surgery for aortic aneurysmal or occlusive arterial disease at the Erasmus University Medical Center. Cardiovascular risk factors, comorbidities, and medication were recorded. Patients treated for combined aneurysmal and occlusive arterial disease and patients diagnosed with a genetic aneurysm syndrome were excluded. Univariable and multivariable analyses were used to calculate differences in CIMT between aneurysmal and occlusive arterial disease.
Results:
In total, 904 patients were included in the study: 502 patients with aneurysmal disease (85% male; mean age, 72 years) and 402 patients with occlusive arterial disease (65% male; mean age, 64 years). The mean (standard deviation) CIMT in patients with aneurysmal disease was 0.97 (0.29) mm and was 1.07 (0.38) mm in patients with occlusive arterial disease (P < .001). Adjustment for cardiovascular risk factors, comorbidities, and medication showed a mean difference in CIMT of 0.15 mm (95% confidence interval, 0.10-0.20; P < .001).
Conclusions:
The current study shows a lower CIMT in patients with aneurysmal disease than in those with occlusive arterial disease, indicating a lower atherosclerotic burden in patients with aneurysmal disease. These findings endorse the idea that additional pathogenic mechanisms are involved in aortic aneurysm formation. Further studies are needed to clarify the role of atherosclerosis in aortic aneurysm formation.
Related Concept Videos
 01:30
Aneurysm I: Introduction
 01:26
Aneurysm III: Interprofessional Care
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:30
Peripheral Artery Disease I: Introduction
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:30
Atherosclerosis I: Introduction