Related Experiment Video
Updated: May 16, 2026

Tail Vein Transection Bleeding Model in Fully Anesthetized Hemophilia A Mice
Published on: September 30, 2021
Aggressive fatal case of autoimmune hemorrhaphilia resulting from anti-Factor XIII antibodies
Hiroyuki Sugiyama1, Hiroko Uesugi, Satoshi Suzuki
1Department of Hematology, Saiseikai Noe Hospital, 1-3-25 Furuichi, Joto-ku, Osaka, Japan.

Factor XIII (FXIII) is a fibrin-stabilizing factor consisting of catalytic A subunits (FXIII-A) and carrier B subunits (FXIII-B). Congenital FXIII deficiency is a rare bleeding disorder. Acquired FXIII deficiency resulting from FXIII hypo-synthesis and/or hyperconsumption is a relatively common disorder in which patients seldom bleed. On the contrary, 'autoimmune/acquired hemorrhaphilia XIII/13 due to anti-FXIII antibodies (AH13)' is a rare but life-threatening bleeding disorder. Through a nationwide survey of AH13, we diagnosed aggressive AH13 in a 66-year-old woman. She consulted our department because of a spontaneous hematoma in her hand. After 1.5 months, she also developed an intramuscular hematoma but retained approximately half (52%) of the normal FXIII activities. The patient's bleeding symptoms were aggravated to catastrophic massive bleedings in the large abdominal muscles and intrapelvic and intraperitoneal spaces. Two months after the bleeding onset, she died despite undergoing plasma exchange, which was performed because we were deeply suspicious of the presence of an anti-FXIII inhibitor. Seven days after her death, extremely low FXIII activity (6%) and positive data on anti-FXIII inhibitor were reported by a commercial laboratory. Our dot blot assay detected anti-FXIII-A autoantibodies, afterwards. Thus, the diagnosis of aggressive AH13 as early as possible is necessary to save patients' lives.
Factor XIII (FXIII) is a fibrin-stabilizing factor consisting of catalytic A subunits (FXIII-A) and carrier B subunits (FXIII-B). Congenital FXIII deficiency is a rare bleeding disorder. Acquired FXIII deficiency resulting from FXIII hypo-synthesis and/or hyperconsumption is a relatively common disorder in which patients seldom bleed. On the contrary, 'autoimmune/acquired hemorrhaphilia XIII/13 due to anti-FXIII antibodies (AH13)' is a rare but life-threatening bleeding disorder. Through a nationwide survey of AH13, we diagnosed aggressive AH13 in a 66-year-old woman. She consulted our department because of a spontaneous hematoma in her hand. After 1.5 months, she also developed an intramuscular hematoma but retained approximately half (52%) of the normal FXIII activities. The patient's bleeding symptoms were aggravated to catastrophic massive bleedings in the large abdominal muscles and intrapelvic and intraperitoneal spaces. Two months after the bleeding onset, she died despite undergoing plasma exchange, which was performed because we were deeply suspicious of the presence of an anti-FXIII inhibitor. Seven days after her death, extremely low FXIII activity (6%) and positive data on anti-FXIII inhibitor were reported by a commercial laboratory. Our dot blot assay detected anti-FXIII-A autoantibodies, afterwards. Thus, the diagnosis of aggressive AH13 as early as possible is necessary to save patients' lives.

Related Concept Videos
 01:23
Rheumatic Heart Disease I: Introduction
 01:20
Extrinsic and Intrinsic Pathways of Hemostasis
The Extrinsic Pathway
The extrinsic pathway of coagulation is typically initiated by tissue damage that exposes blood to tissue factor (TF), a protein released by the damaged tissue cells outside the blood vessels—this interaction with TF triggers biochemical reactions involving specific clotting factors. The key player here is Factor VII, which forms a...
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:19
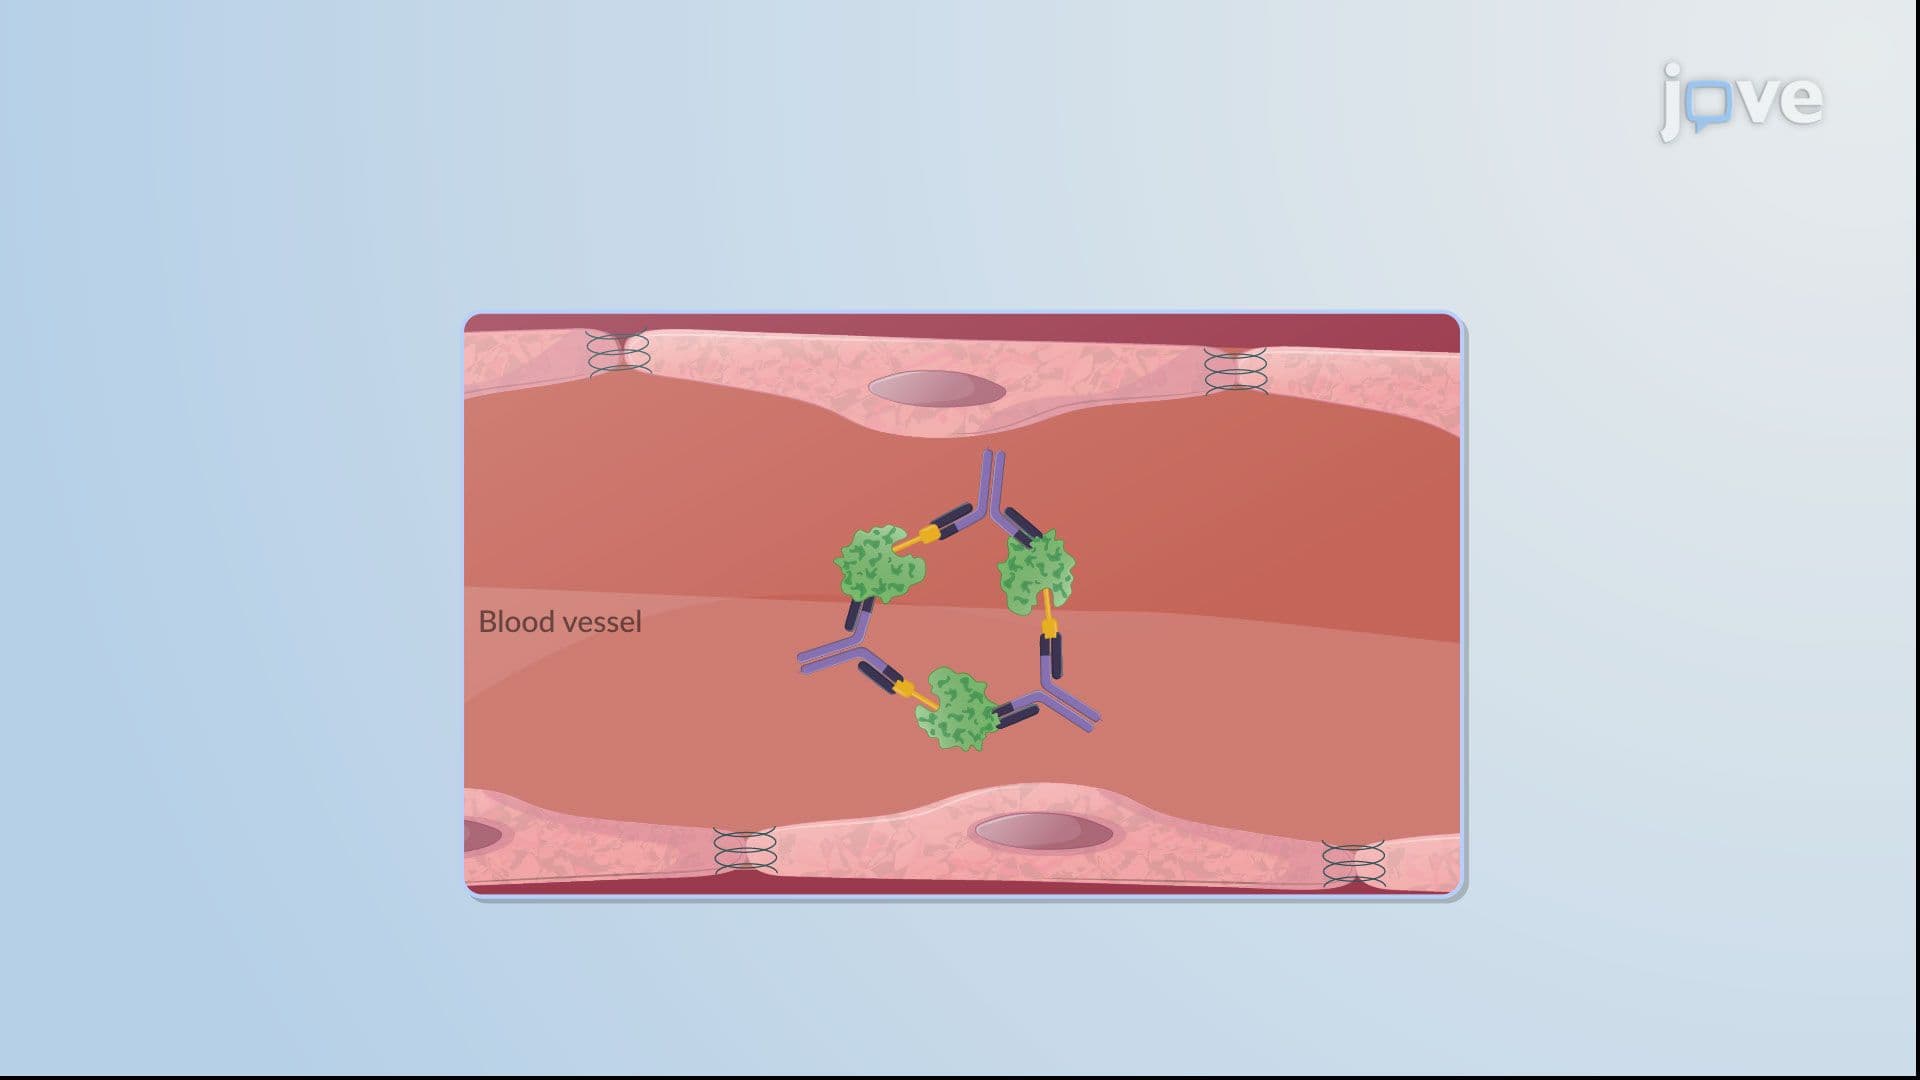
Hypersensitivity Reactions: Immune-Complex Reactions
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:29
Venous Thrombosis III: Interprofessional Care