Surgical outcomes of hepatocellular carcinoma with bile duct tumor thrombus: a Korean multicenter study
Related Experiment Video
Updated: May 16, 2026
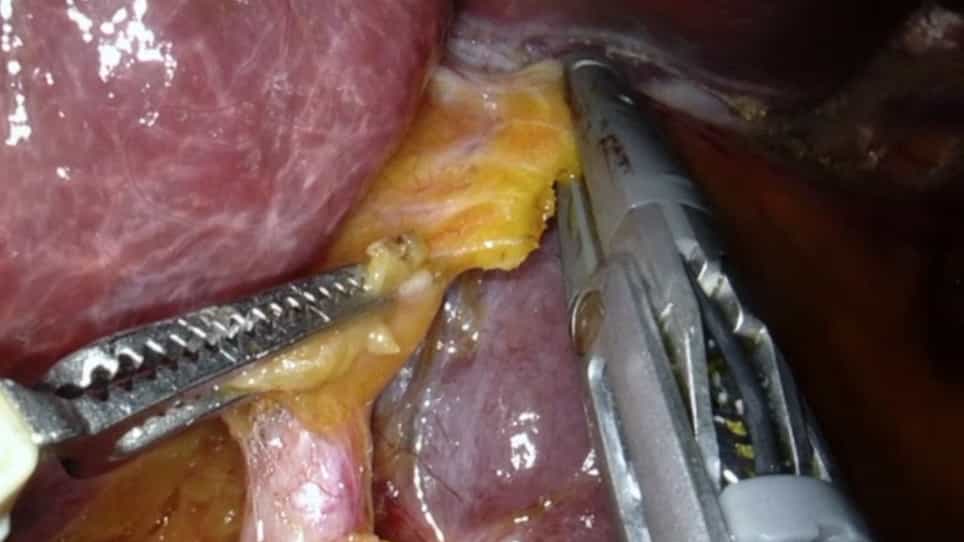
Robotic Left Hepatectomy using Indocyanine Green Fluorescence Imaging for an Intrahepatic Complex Biliary Cyst
Published on: June 24, 2022
Deok-Bog Moon1, Shin Hwang, Hee-Jung Wang
1Department of Surgery, Asan Medical Center, College of Medicine, University of Ulsan, 388-1 Poongnap-Dong, Songpa-Gu, Seoul 138-736, Korea.

Insights
Hepatocellular carcinoma (HCC) patients with bile duct tumor thrombus (BDTT) can achieve favorable long-term outcomes after surgical resection. Extensive surgery is recommended for complete tumor removal to improve patient prognosis.
Area of Science:
- Hepatobiliary Surgery
- Surgical Oncology
- Gastroenterology
Background:
- Long-term outcomes for hepatocellular carcinoma (HCC) with macroscopic bile duct tumor thrombus (BDTT) post-resection remain unclear.
- This study investigates the prognosis of HCC patients with BDTT undergoing curative-intent resection.
Purpose of the Study:
- To determine the long-term prognosis of HCC patients with macroscopic BDTT after surgical resection.
- To evaluate the impact of surgical interventions on survival and recurrence rates.
Main Methods:
- Retrospective analysis of 73 HCC patients with BDTT from four Korean institutions.
- Data collected included patient demographics, tumor characteristics, surgical procedures (hepatectomy, bile duct resection), and outcomes.
- Ueda classification was used for BDTT staging.
Main Results:
- Survival rates at 1, 3, 5, and 10 years were 76.5%, 41.4%, 32.0%, and 17.0%, respectively.
- Recurrence rates at 1, 3, 5, and 10 years were 42.9%, 70.6%, 77.3%, and 81.1%, respectively.
- Maximal tumor size, bile duct resection, and surgical curability were significant risk factors for survival and recurrence in univariate analysis.
Conclusions:
- Hepatocellular carcinoma patients with BDTT can achieve relatively favorable long-term results after resection.
- Extensive surgery, aiming for complete resection, should be recommended for these patients to improve outcomes.
Background:
The long-term outcomes after resection for hepatocellular carcinoma (HCC) with macroscopic bile duct tumor thrombus (BDTT) are unclear. This multicenter study was conducted to determine the prognosis of HCC patients with macroscopic BDTT who underwent resection with curative intent.
Methods:
Of 4,308 patients with HCC from four Korean institutions, this single-arm retrospective study included 73 patients (1.7 %) who underwent resection for HCC with BDTT.
Results:
Jaundice was also present in 34 patients (46.6 %). According to Ueda classification, BDTT was type 2 in 34 cases (46.6 %) and type 3 in 39 cases (53.4 %). Biliary decompression was performed in 33 patients (45.2 %), decreasing the median lowest bilirubin level to 1.4 mg/dL before surgery. Systematic hepatectomy was performed in 69 patients (94.5 %), and concurrent bile duct resection was performed in 31 patients (42.5 %). Surgical curability types were R0 (n = 57; 78.1 %), R1 (n = 11; 15.1 %), and R2 (n = 5; 6.8 %). Patient survival rates were 76.5 % at 1 year, 41.4 % at 3 years, 32.0 % at 5 years, and 17.0 % at 10 years. Recurrence rates were 42.9 % at 1 year, 70.6 % at 3 years, 77.3 % at 5 years, and 81.1 % at 10 years. Results of univariate survival analysis showed that maximal tumor size, bile duct resection, and surgical curability were significant risk factors for survival, and surgical curability was a significant risk factor for recurrence. Multivariate analysis did not reveal any independent risk factors.
Conclusions:
Hepatocellular carcinoma patients with BDTT achieved relatively favorable long-term results after resection; therefore extensive surgery should be recommended when complete resection is anticipated.