Related Experiment Video
Updated: May 16, 2026

Quantitative Structure-Activity Relationship, Activity Prediction, and Molecular Dynamics of Non-nucleotide Reverse Transcriptase Inhibitors
Published on: May 9, 2025
Protein binding of lopinavir and ritonavir during 4 phases of pregnancy: implications for treatment guidelines
Kristine B Patterson1, Julie B Dumond, Heather A Prince
1Department of Medicine, University of North Carolina, Chapel Hill, NC 27599-7215, USA. kristine_patterson@med.unc.edu

Insights
This study found that while total lopinavir/ritonavir (LPV/RTV) exposure decreased during pregnancy, unbound LPV/RTV levels remained stable. This suggests that dose adjustments may not be necessary for all HIV-infected pregnant women.
Area of Science:
- Pharmacokinetics and Drug Metabolism
- Infectious Diseases and Virology
- Maternal-Fetal Medicine
Background:
- Pregnancy significantly alters drug pharmacokinetics (PKs), potentially impacting antiretroviral therapy efficacy in HIV-infected women.
- Lopinavir/ritonavir (LPV/RTV) is a crucial component of antiretroviral regimens, but its PK profile during pregnancy requires careful consideration.
- Understanding changes in both total and unbound drug concentrations is essential for optimizing treatment outcomes.
Purpose of the Study:
- To investigate the intraindividual pharmacokinetics (PKs) of total and unbound lopinavir/ritonavir (LPV/RTV) during pregnancy.
- To assess if the pediatric formulation of LPV/RTV can mitigate pregnancy-associated PK changes.
- To determine if LPV/RTV dose adjustments are necessary for HIV-infected pregnant women.
Main Methods:
- A prospective longitudinal PK study was conducted in HIV-infected pregnant women.
- Participants received standard LPV/RTV (400 mg/100 mg) twice daily, with dose escalation using the pediatric formulation (100 mg/25 mg) at 30 weeks gestation.
- Intensive PK evaluations were performed at multiple time points: 20-24 weeks, 30 weeks, 32 weeks, and 8 weeks postpartum.
Main Results:
- Total LPV exposure (AUC0-12h) was significantly lower during pregnancy compared to postpartum (P = 0.005).
- Unbound LPV AUC0-12h remained unchanged throughout pregnancy, even after a 25% dose increase.
- Unbound LPV predose concentrations (C12h) were not significantly affected by the dose increase and remained well above the minimum efficacy concentration.
Conclusions:
- Total LPV exposure decreases during pregnancy, but unbound LPV exposure remains stable.
- The pediatric formulation did not significantly alter unbound LPV concentrations, suggesting it may not be necessary for all pregnant women.
- Current dosing of LPV/RTV may be adequate for maintaining therapeutic unbound concentrations in most HIV-infected pregnant women.
Objective:
To investigate the intraindividual pharmacokinetics (PKs) of total (protein bound plus unbound) and unbound lopinavir/ritonavir (LPV/RTV) and to assess whether the pediatric formulation (100 mg/25 mg) can overcome any pregnancy-associated changes.
Design:
Prospective longitudinal PK study.
Methods:
HIV-infected pregnant antiretroviral therapy-naive and experienced women receiving LPV/RTV 400 mg/100 mg tablets twice daily. Intensive PK evaluations were performed at 20-24 weeks (PK1), 30 weeks (PK2) followed by empiric dose increase using the pediatric formulation (100 mg/25 mg twice daily), 32 weeks (PK3), and 8 weeks postpartum (PK4).
Results:
Twelve women completed prespecified PK evaluations. Median (range) age was 28 (18-35) years and baseline BMI was 32 (19-41) kg/m. During pregnancy, total area under the time concentration (AUC0-12h) for LPV was significantly lower than postpartum (PK1, PK2, or PK3 vs. PK4, P = 0.005). Protein-unbound LPV AUC0-12h remained unchanged during pregnancy [PK1: 1.6 (1.3-1.9) vs. PK2: 1.6 (1.3-1.9) μg·h/mL, P = 0.4] despite a 25% dose increase [PK2 vs. PK3: 1.8 (1.3-2.1) μg·h/mL, P = 0.5]. Protein-unbound LPV predose concentrations (C12h) did not significantly change despite dose increase [PK2: 0.10 (0.08-0.15) vs. PK3: 0.12 (0.10-0.15) μg/mL, P = 0.09]. Albumin and LPV AUC0-12h fraction unbound were correlated (rs = 0.3, P = 0.03).
Conclusions:
Total LPV exposure was significantly decreased throughout pregnancy despite the increased dose. However, the exposure of unbound LPV did not change significantly regardless of trimester or dose. Predose concentrations of unbound LPV were not affected by the additional dose and were 70-fold greater than the minimum efficacy concentration. These findings suggest dose adjustments may not be necessary in all HIV-infected pregnant women.

Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:29
Factors Affecting Protein-Drug Binding: Patient-Related Factors
Age stands as a key determinant in protein-drug binding. Neonates, characterized by low albumin content, experience heightened concentrations of unbound drugs such as phenytoin and...
 01:26
Pharmacokinetics: Drug–Food and Drug–Viral Interactions
 01:09
Hepatic Drug Clearance: Effect of Protein Binding
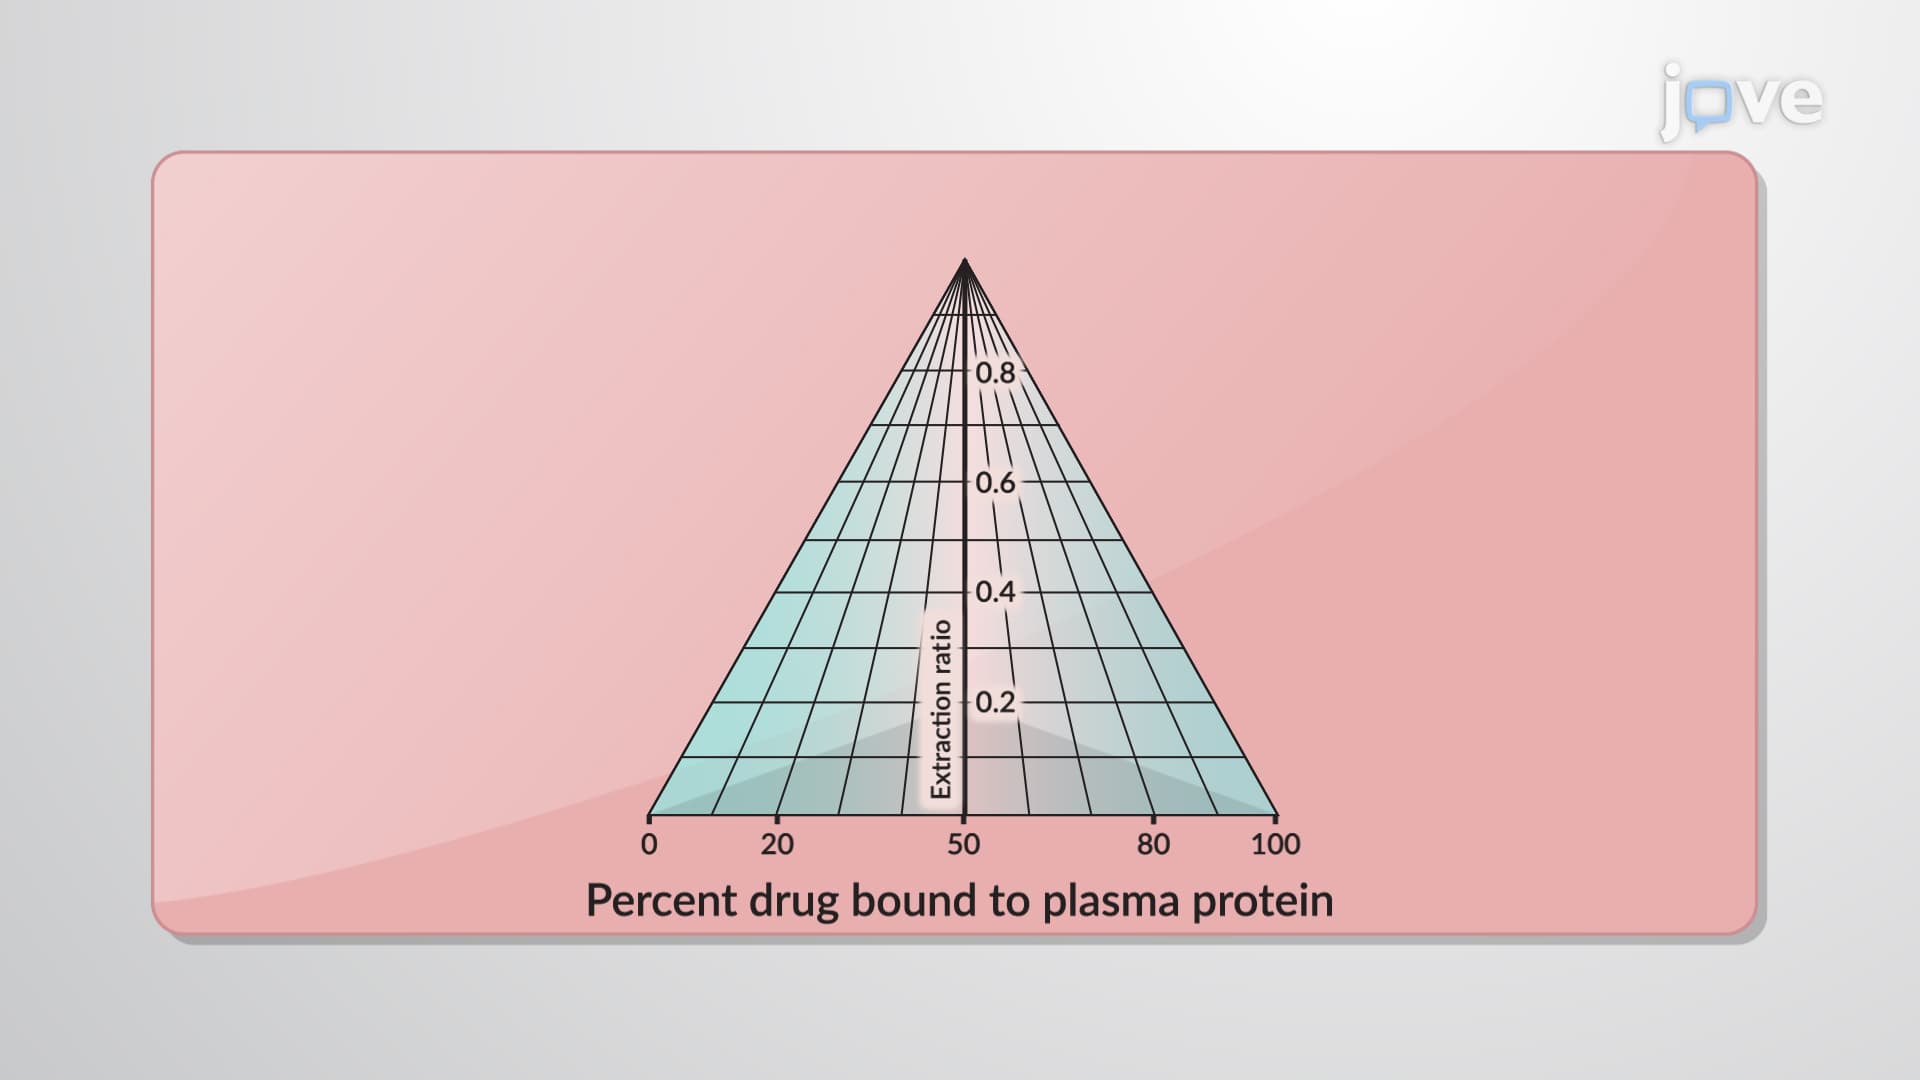
For low-extraction-ratio drugs that are less than 80% protein-bound, minor changes in protein binding...
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution