Related Experiment Video
Updated: May 16, 2026

Intracoronary Acetylcholine Provocation Testing for Assessment of Coronary Vasomotor Disorders
Published on: August 18, 2016
Acute effects of intracoronary nitroglycerin and diltiazem in coronary slow flow phenomenon
Ibrahim Ozdogru1, Cemil Zencir, Ali Dogan
1Department of Cardiology, Erciyes University Medical Faculty, Kayseri, Turkey. iozdogru@hotmail.com

Background:
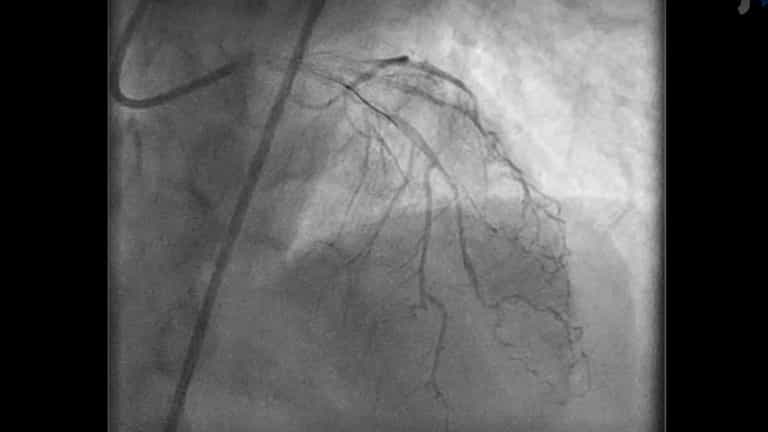
The coronary slow flow phenomenon (CSFP) is a coronary microvascular disorder angiographically defined by delayed opacification of the distal vasculature in the absence of obstructive coronary artery disease. We aimed to investigate and compare the effects of intracoronary nitrate and diltiazem on thrombolysis in myocardial infarction frame count (TFC) in patients with CSFP during coronary angiography.
Methods:
Sixty patients with CSFP were randomly divided into 2 groups. The first group is nitroglycerin group with 30 patients (22 men; mean [SD] age, 50 [12] years), and the second is diltiazem group with 30 patients (27 men; mean age, 54 ± 11 years); intracoronary 5-mg diltiazem or 250-μg nitroglycerin was administered. Heart rate, systolic and diastolic blood pressures, and TFCs in all 3 coronaries were recorded before and after administering these medications.
Results:
After nitroglycerin administration, systolic and diastolic blood pressures decreased, heart rates significantly increased, and TFCs decreased in all coronaries (P < 0.001 for 3 coronaries). After the application of intracoronary 5-mg diltiazem, heart rate, systolic and diastolic blood pressures, and TFCs were found significantly lower than predrug values (P < 0.001 for all values). When the percent TFC reductions, after the application of intracoronary diltiazem or nitroglycerin, in left anterior descending coronary artery, circumflex coronary artery, and right coronary artery were evaluated, diltiazem significantly reduced the TFCs of the left anterior descending coronary artery and circumflex coronary artery compared with nitroglycerin (P < 0.01 for both coronaries).
Conclusion:
Both intracoronary diltiazem and nitroglycerin improve the TFCs in CSFP, and intracoronary diltiazem is superior to nitroglycerin in reducing TFCs in CSFP.
Related Concept Videos
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:27
Angina II: Classification