Related Experiment Video
Updated: May 16, 2026
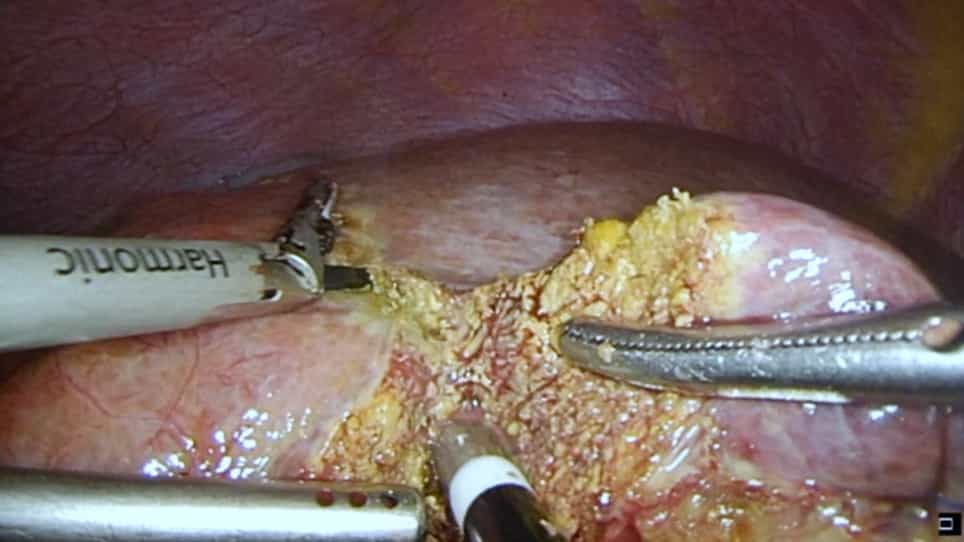

Application of Hemostatic Devices in Laparoscopic Hepatectomy
Published on: April 19, 2022
Hemostatic defects in liver and renal dysfunction
Pier Mannuccio Mannucci1, Armando Tripodi
1Scientific Direction, Istituto di Ricovero e Cura a Carattere Scientifico (IRCCS) Ca' Granda Maggiore Policlinico Hospital Foundation, Milan, Italy. pmmannucci@libero.it

Multiple and complex abnormalities of hemostasis are revealed by laboratory tests in such common diseases as cirrhosis and end-stage renal insufficiency. Because these abnormalities are associated with a bleeding tendency, a causal relationship is plausible. Accordingly, an array of transfusional and nontransfusional medications that improve or correct these abnormalities is used to prevent or stop hemorrhage. However, recent data indicate that the use of hemostatic drugs is scarcely justified mechanistically or clinically. In patients with uremia, the bleeding tendency (mainly expressed by gastrointestinal bleeding and hematoma formation at kidney biopsy) is reduced dramatically by the improvement of anemia obtained with the regular use of erythropoietin. In cirrhosis, the most severe and frequent hemorrhagic symptom (acute bleeding from esophageal varices) is not explained by abnormalities in such coagulation screening tests as the prothrombin and partial thromboplastin times, because formation of thrombin the final coagulation enzyme is rebalanced by low naturally occurring anticoagulant factors in plasma that compensate for the concomitant decrease of procoagulants. Rebalance also occurs for hyperfibrinolysis and platelet abnormalities. These findings are consistent with clinical observations that transfusional and nontransfusional hemostatic medications are of little value as adjuvants to control bleeding in advanced liver disease. Particularly in uremia, but also in cirrhosis, thrombosis is becoming a cogent problem.
Multiple and complex abnormalities of hemostasis are revealed by laboratory tests in such common diseases as cirrhosis and end-stage renal insufficiency. Because these abnormalities are associated with a bleeding tendency, a causal relationship is plausible. Accordingly, an array of transfusional and nontransfusional medications that improve or correct these abnormalities is used to prevent or stop hemorrhage. However, recent data indicate that the use of hemostatic drugs is scarcely justified mechanistically or clinically. In patients with uremia, the bleeding tendency (mainly expressed by gastrointestinal bleeding and hematoma formation at kidney biopsy) is reduced dramatically by the improvement of anemia obtained with the regular use of erythropoietin. In cirrhosis, the most severe and frequent hemorrhagic symptom (acute bleeding from esophageal varices) is not explained by abnormalities in such coagulation screening tests as the prothrombin and partial thromboplastin times, because formation of thrombin the final coagulation enzyme is rebalanced by low naturally occurring anticoagulant factors in plasma that compensate for the concomitant decrease of procoagulants. Rebalance also occurs for hyperfibrinolysis and platelet abnormalities. These findings are consistent with clinical observations that transfusional and nontransfusional hemostatic medications are of little value as adjuvants to control bleeding in advanced liver disease. Particularly in uremia, but also in cirrhosis, thrombosis is becoming a cogent problem.

Related Concept Videos
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:20
Extrinsic and Intrinsic Pathways of Hemostasis
The Extrinsic Pathway
The extrinsic pathway of coagulation is typically initiated by tissue damage that exposes blood to tissue factor (TF), a protein released by the damaged tissue cells outside the blood vessels—this interaction with TF triggers biochemical reactions involving specific clotting factors. The key player here is Factor VII, which forms a...