Related Experiment Video
Updated: May 16, 2026

Epithelial Cell Infection Analyses with Shigella
Published on: February 9, 2024
Risk factors for secondary transmission of Shigella infection within households: implications for current prevention
Lian Boveé1, Jane Whelan, Gerard J B Sonder
1Department of Infectious Diseases, Public Health Service (GGD) Amsterdam, Nieuwe Achtergracht 100, PO Box 2200, Amsterdam, 1000 CE, the Netherlands.

Background:
Internationally, guidelines to prevent secondary transmission of Shigella infection vary widely. Cases, their contacts with diarrhoea, and those in certain occupational groups are frequently excluded from work, school, or daycare. In the Netherlands, all contacts attending pre-school (age 0-3) and junior classes in primary school (age 4-5), irrespective of symptoms, are also excluded pending microbiological clearance. We identified risk factors for secondary Shigella infection (SSI) within households and evaluated infection control policy in this regard.
Methods:
This retrospective cohort study of households where a laboratory confirmed Shigella case was reported in Amsterdam (2002-2009) included all households at high risk for SSI (i.e. any household member under 16 years). Cases were classified as primary, co-primary or SSIs. Using univariable and multivariable binomial regression with clustered robust standard errors to account for household clustering, we examined case and contact factors (Shigella serotype, ethnicity, age, sex, household size, symptoms) associated with SSI in contacts within households.
Results:
SSI occurred in 25/ 337 contacts (7.4%): 20% were asymptomatic, 68% were female, and median age was 14 years (IQR: 4-38). In a multivariable model adjusted for case and household factors, only diarrhoea in contacts was associated with SSI (IRR 8.0, 95% CI:2.7-23.8). In a second model, factors predictive of SSI in contacts were the age of case (0-3 years (IRRcase≥6 years:2.5, 95% CI:1.1-5.5) and 4-5 years (IRRcase≥6 years:2.2, 95% CI:1.1-4.3)) and household size (>6 persons (IRR2-4 persons 3.4, 95% CI:1.2-9.5)).
Conclusions:
To identify symptomatic and asymptomatic SSI, faecal screening should be targeted at all household contacts of preschool cases (0-3 years) and cases attending junior class in primary school (4-5 years) and any household contact with diarrhoea. If screening was limited to these groups, only one asymptomatic adult carrier would have been missed, and potential exclusion of 70 asymptomatic contacts <6 years old from school or daycare, who were contacts of cases of all ages, could have been avoided.


Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:17
Transmission-based Precautions I: Contact, Enteric, and Droplets
Contact Precautions:
Contact precautions are the measures taken to prevent the transmission of infectious agents, especially epidemiologically important microorganisms such as MRSA or influenza, primarily transmitted through direct or indirect contact with an...
 01:20
Infection
The chain begins with pathogens: bacteria, viruses, fungi, prions, or parasites such as protozoa helminths. These can be present on the skin as transient or resident flora, or they can be acquired from the environment. Identifying and treating the type of infection and...
 01:18
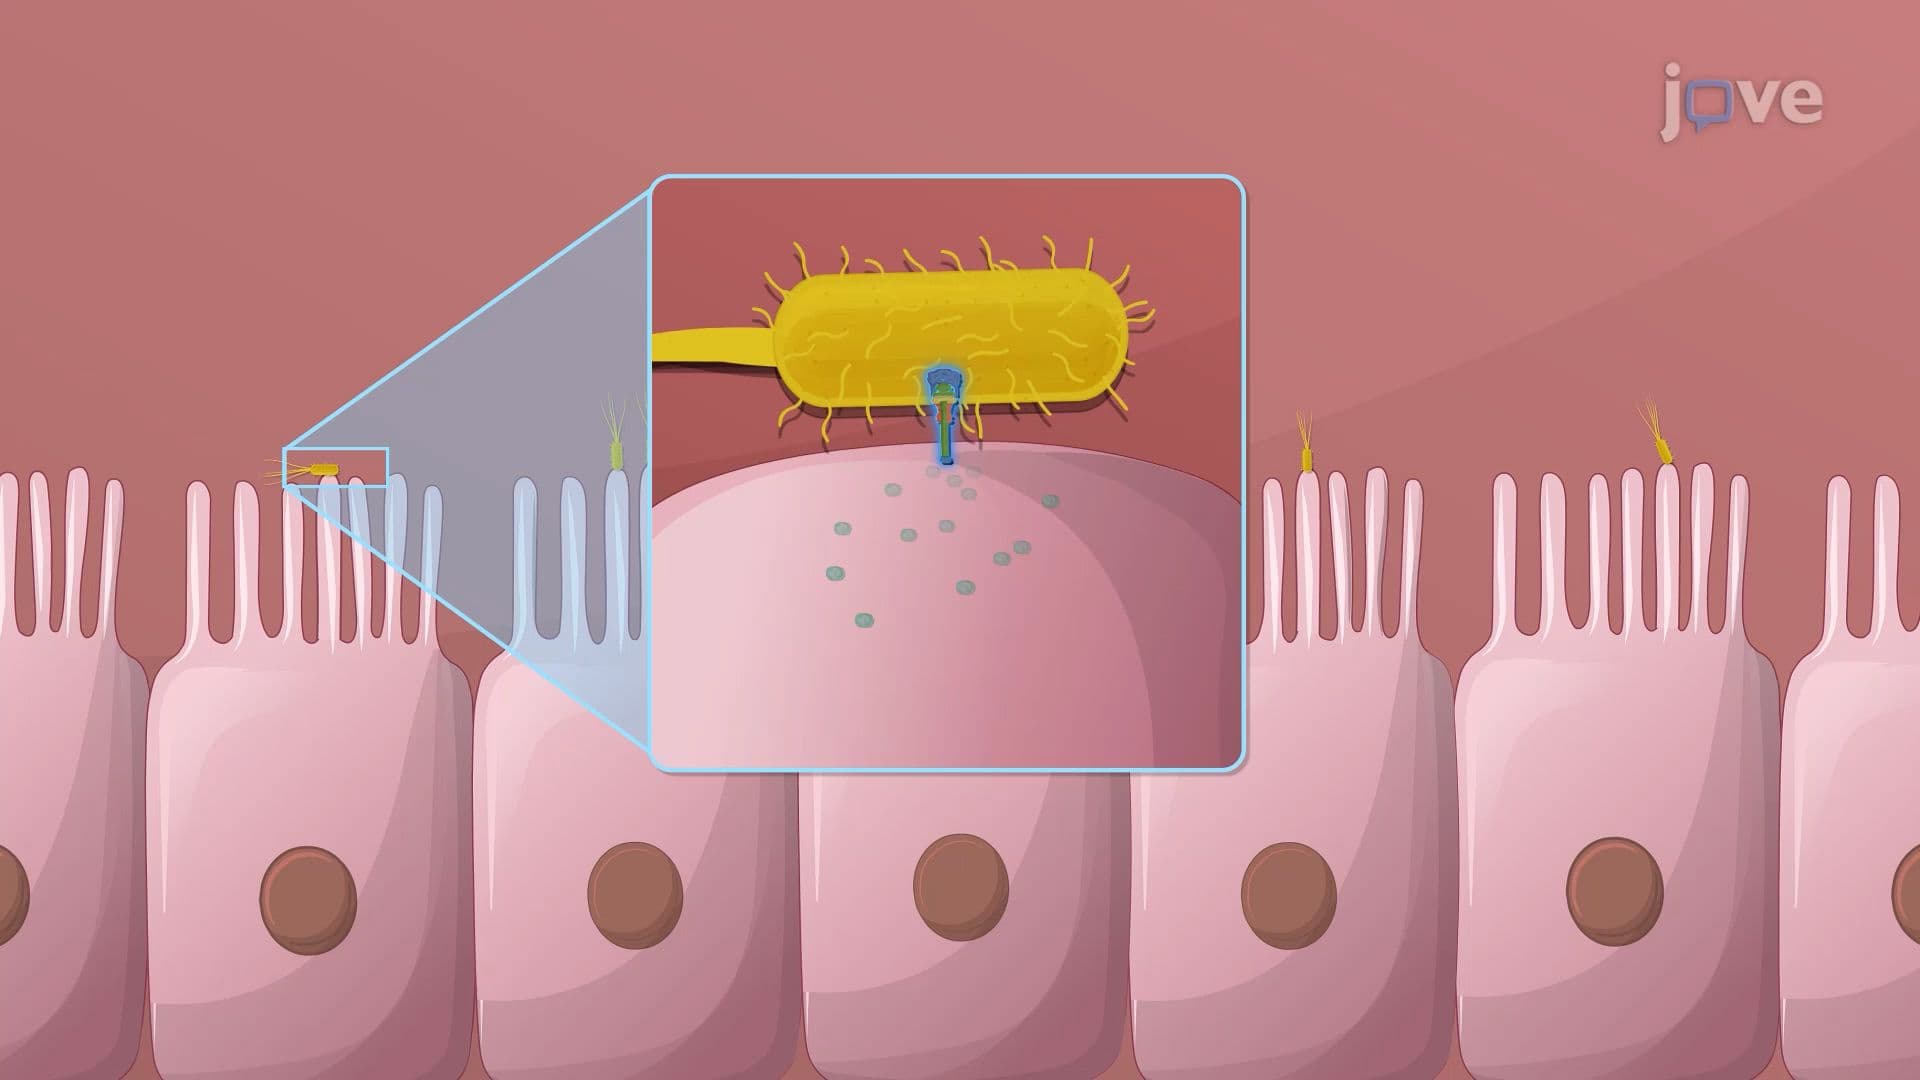
Bacterial Gastroenteritis
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin create...
 01:30
Reservoir of Infection