Related Experiment Video
Updated: May 5, 2026


Reduced Itraconazole Concentration and Durations Are Successful in Treating Batrachochytrium dendrobatidis Infection in Amphibians
Published on: March 15, 2014
Bismuth induced encephalopathy caused by tri potassium dicitrato bismuthate in a patient with chronic renal failure
R J Playford1, C H Matthews, M J Campbell
1Department of Medicine, Royal Postgraduate Medical School, Hammersmith Hospital, London.

Abstract:
A 68 year old man with a creatinine clearance rate of only 15 ml/min took twice the recommended dose of tripotassium dicitrato bismuthate (TDB) as DeNol liquid; 10 ml qds; a total of 864 mg bismuth daily for two months. Whole blood bismuth concentrations rose to 880 micrograms/l and he developed global cerebral dysfunction with hallucinations, ataxia, and an abnormal EEG. Renal clearance of bismuth rose from 0.24 to 2.4 ml/min when the heavy metal chelator 2-3 dimercapto-1 propane sulphonic acid (DMPS) was given by mouth. Bismuth was measured by a novel method involving inductively coupled plasma source mass spectrometry. Fifty days after stopping TDB, whole blood bismuth concentrations fell to 46 micrograms/l and the patient's EEG returned to normal. His mental function also recovered completely. The case serves as a timely reminder that TDB should not be administered to patients with renal disorders, as stated in the data sheet.

Related Concept Videos
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:24
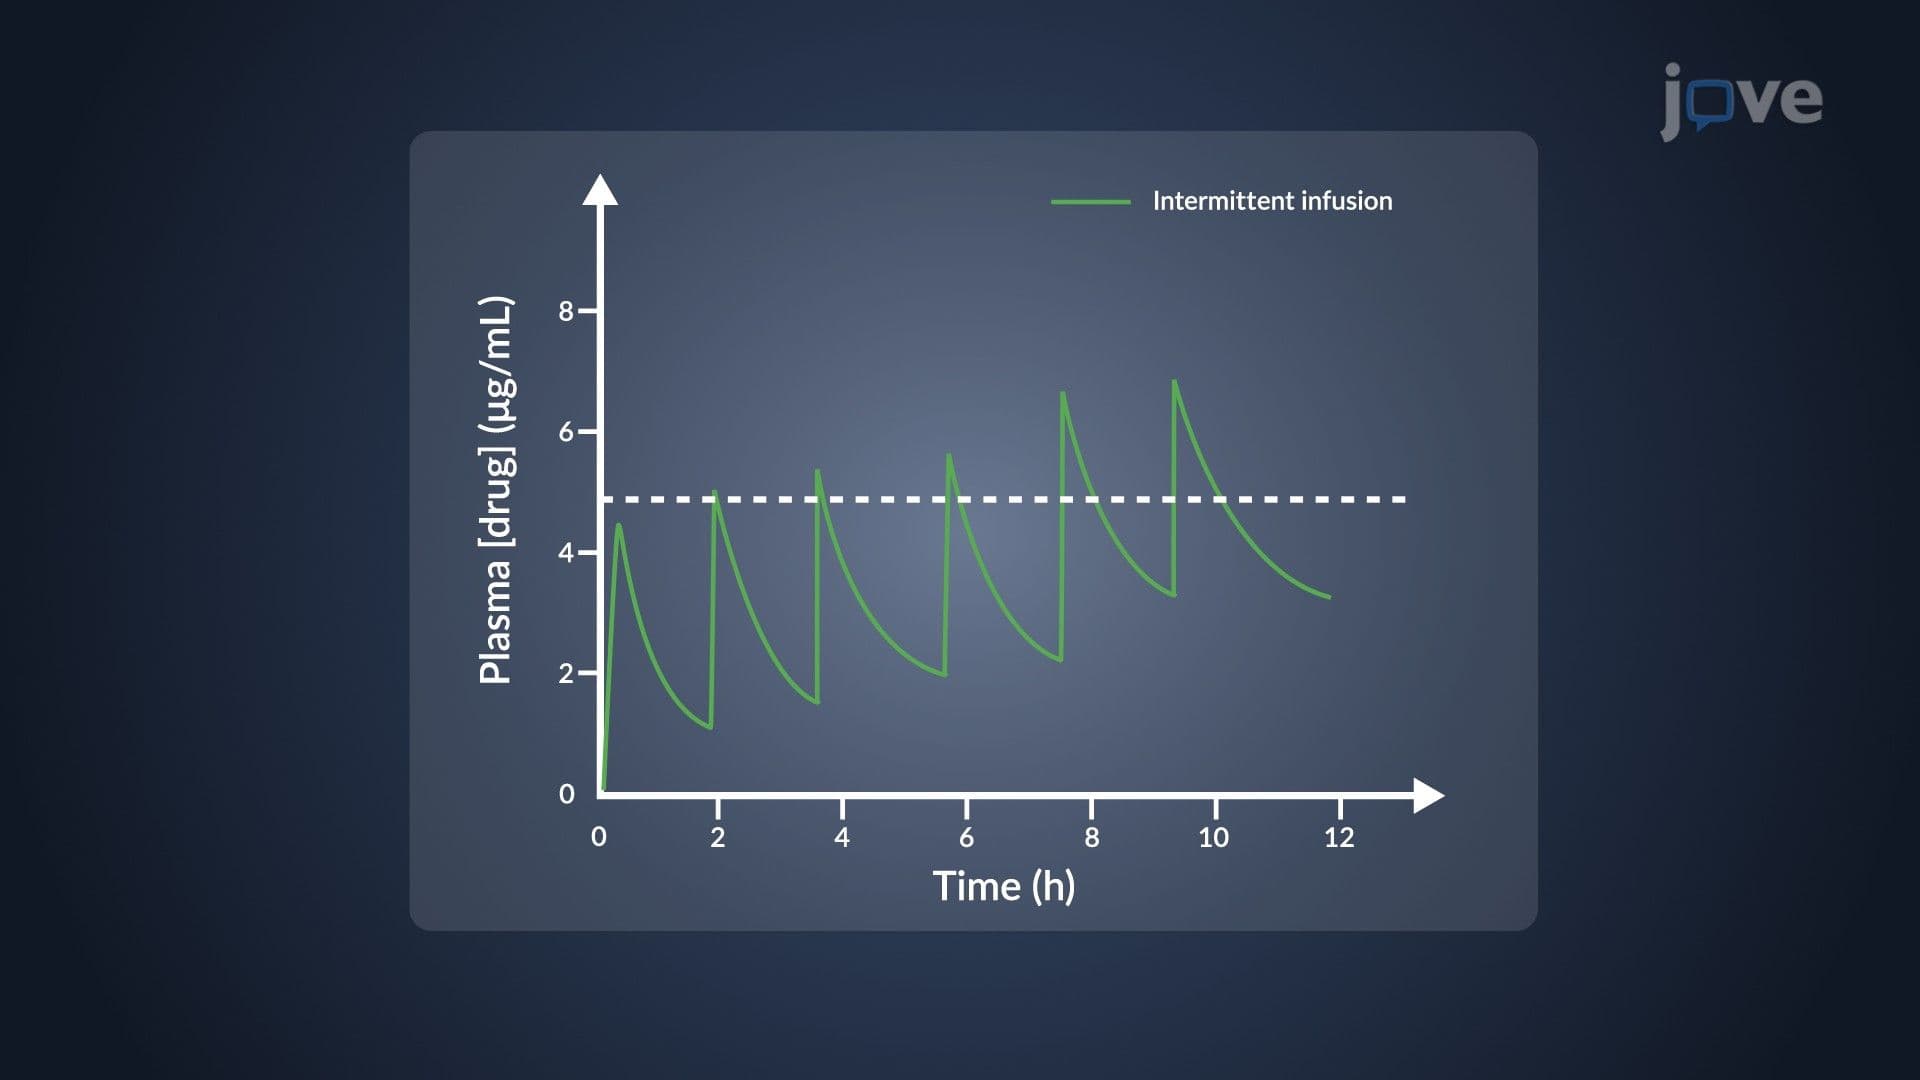
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:29
Hepatic Encephalopathy