Related Experiment Video
Updated: May 16, 2026


A Pacing-Controlled Procedure for the Assessment of Heart Rate-Dependent Diastolic Functions in Murine Heart Failure Models
Published on: July 21, 2023
Relationship between baseline resting diastolic function and exercise capacity in patients with hypertrophic
Wael A Aljaroudi1, Milind Y Desai, M Chadi Alraies
1Robert and Suzanne Tomsich Department of Cardiovascular Medicine, Heart and Vascular Institute, Cleveland Clinic, Cleveland, Ohio, USA.

Insights
Diastolic dysfunction (DD) is common in hypertrophic cardiomyopathy (HCM) patients but does not predict exercise capacity. Other traditional risk factors are more significant predictors of maximal metabolic equivalents (METs) achieved.
Area of Science:
- Cardiology
- Cardiovascular Imaging
- Exercise Physiology
Background:
- Diastolic dysfunction (DD) is frequently observed in patients with hypertrophic cardiomyopathy (HCM).
- The direct impact of baseline diastolic function on exercise capacity in HCM remains incompletely understood.
- Limited data exist on the predictive value of DD for exercise limitations in HCM.
Purpose of the Study:
- To investigate the association between baseline diastolic function and exercise capacity in patients diagnosed with HCM.
- To determine if diastolic dysfunction is an independent predictor of exercise performance in this population.
Main Methods:
- Retrospective analysis of 695 consecutive HCM patients undergoing exercise stress echocardiography.
- Diastolic function was assessed from resting echocardiograms by blinded cardiologists.
- Maximal metabolic equivalents (METs) were recorded, and multivariate regression analysis identified predictors of METs achieved.
Main Results:
- After exclusions, 495 patients were analyzed, with varying stages of diastolic dysfunction (DD).
- Patients with advanced DD demonstrated lower maximal METs compared to those with normal diastolic function (p<0.0001).
- However, baseline DD was not an independent predictor of maximal METs achieved after adjusting for other factors.
Conclusions:
- Baseline diastolic dysfunction is prevalent in HCM patients.
- Diastolic dysfunction does not independently predict exercise capacity (maximal METs) in HCM.
- Traditional risk factors appear to be more influential in determining exercise limitations in HCM patients.
Objective:
Diastolic dysfunction (DD) is often incriminated in the symptomatology of patients with hypertrophic cardiomyopathy (HCM), but with limited supporting data. This study sought to assess the relationship between baseline diastolic function and exercise capacity in patients with HCM.
Design:
Retrospective study.
Setting:
Tertiary referral centre from Cleveland, Ohio, USA.
Participants:
695 consecutive patients with a diagnosis of HCM who underwent exercise stress echocardiography between 1996 and 2011.
Primary And Secondary Outcome Measures:
Diastolic function was reassessed from the resting echocardiograms by two blinded board-certified cardiologists. Maximal metabolic equivalents (MET) were extracted from the records. Multivariate regression analysis was performed to determine independent predictors of METs achieved.
Results:
Of 695 patients, 130 were excluded because of inability to assess diastolic function. There was no significant difference in maximal METs achieved between those excluded and included in the analysis (p=0.80). There were 495 remaining patients with a mean age (SD) of 50 (15) years, and 32% women among whom 102 (21%) had normal diastolic function, 243 (49%) stage 1 DD; 131 (26%) stage 2 DD and 19 (4%) stage 3 DD. Patients with advanced DD had lower maximal METs achieved compared with those with normal diastolic function (OR 3.18(1.96 to 5.14) for stage 1 versus normal, and 3.21(1.89 to 5.43) for stage ≥2 versus normal, p<0.0001 for both). After adjustment for demographics, comorbidities, echocardiographic parameters and haemodynamics, baseline DD was not an independent predictor of maximal METs achieved.
Conclusions:
Although baseline DD is common in patients with HCM, it does not predict maximal METs achieved beyond traditional risk factors.

Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Heart Failure II: Pathophysiology
 01:26
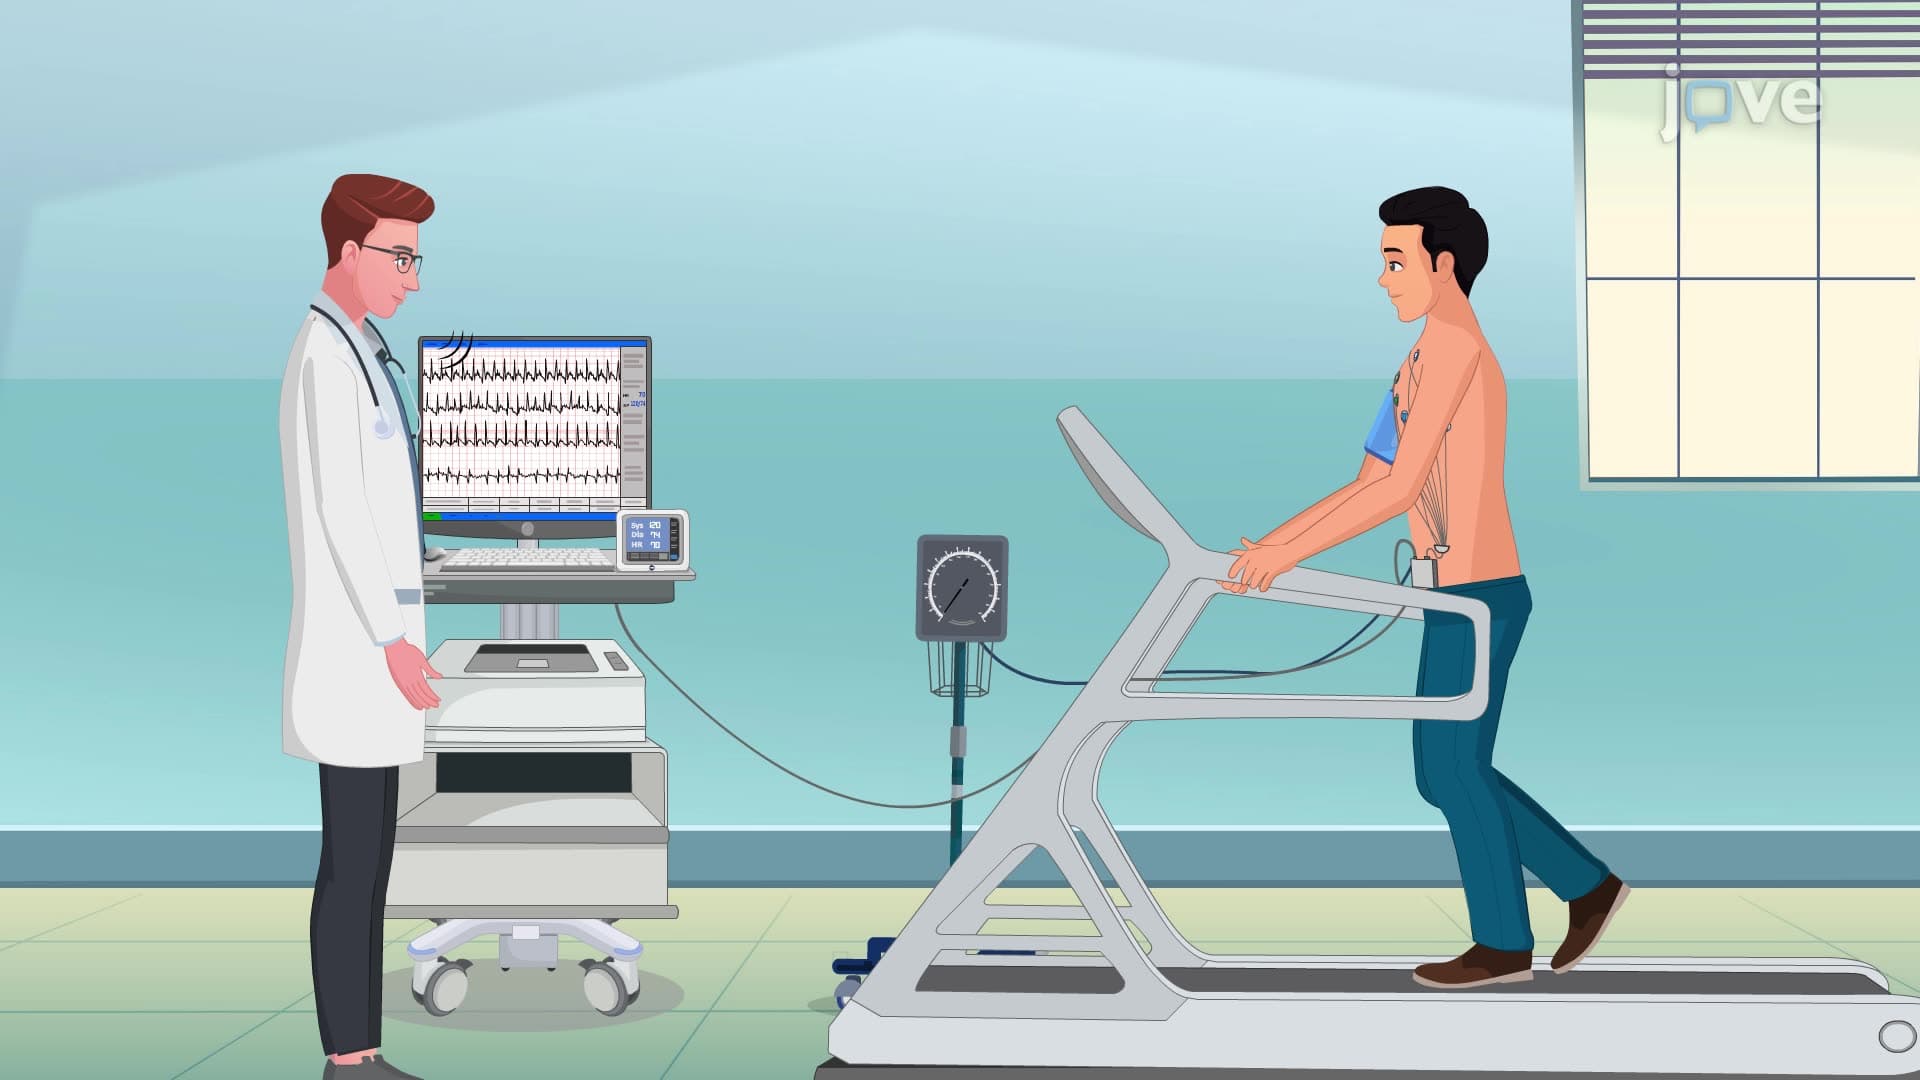
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:29
Cardiomyopathy V: Interprofessional Care
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy