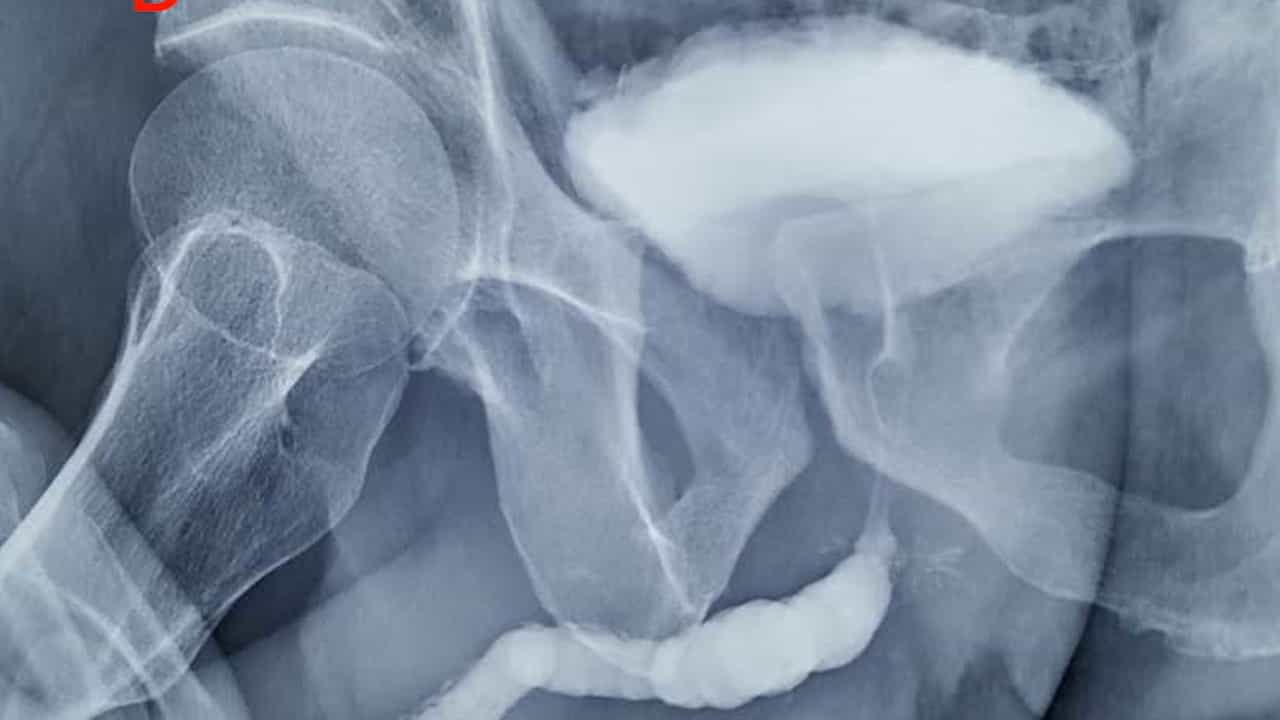

A geographic analysis of male urethral stricture aetiology and location
Daniel M Stein1, D Joseph Thum, Guido Barbagli
1Department of Urology, Feinberg School of Medicine, Northwestern University, Chicago, IL, USA.

Unlabelled:
WHAT'S KNOWN ON THE SUBJECT? AND WHAT DOES THE STUDY ADD?: The incidence of specific aetiologies of urethral stricture disease has been reported from a variety of series throughout the world. Most reported urethral stricture series are from single institutions or from a specific region of the world. We provide a multi-centred series to compare aetiologic incidence between differing regional populations.
Objective:
To better understand distinct regional patterns in urethral stricture aetiology and location among distinct regional populations.
Patients And Methods:
Data on 2589 patients who underwent urethroplasty from 2000 to 2011 were collected retrospectively from three clinical sites, including 1646 patients from Italy, 715 from India and 228 from the USA. Data from all sites were single-surgeon series. As the data from the Italian and US cohorts were similar in aetiology, location and demographics, we combined these data to form group 1, and compared this group with men in the Indian cohort, group 2. Age, stricture site and primary stricture aetiology were identified for each patient. Stricture site and primary aetiology were determined by the treating surgeon. Primary aetiology was defined as iatrogenic, trauma including pelvic-fracture-related urethral injury (PFUI), lichen sclerosus (LS), infectious, congenital, or unknown.
Results:
There were more penile strictures (27 vs 5%) and fewer posterior urethral stenoses (9 vs 34%) in group 1. There were more iatrogenic strictures identified in group 1 (35 vs 16%). When comparing the aetiology of iatrogenic strictures alone, more strictures in group 1 were attributable to failed hypospadias repair (49 vs 16%). More patients presented with LS (22 vs 7%) and external trauma (36 vs 16%) in group 2. Prevalence of strictures of infectious aetiology was low (1%) with similar proportions between the two groups.
Conclusions:
We have shown that significant regional differences in stricture aetiology exist in a large multicentre cohort study. Group 1 had a higher proportion of penile strictures, largely owing to more iatrogenic strictures and, in particular, failed hypospadias repair. Group 2 had a higher proportion of PFUI and LS-associated urethal stricture. Identified infection-related urethral stricture was rare in all cohorts. Significant regional differences in stricture aetiology exist and should be considered when analysing international outcomes after urethroplasty. These data may also help the development of international disease prevention and treatment strategies.

Related Concept Videos
 01:16
Urethra
The anatomy of the urethra differs between males and females. In females, the urethra is short, measuring about 3–4 cm in length, and opens anterior to the vaginal opening. In males, the urethra is longer and passes through the penis, serving dual purposes: expelling urine and ejaculating semen. The male urethra is...
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:28
Microbiota of the Urogenital Tract
 01:20
Disorders of the Male Reproductive System
Prostate disorders are another major concern. These conditions can impair urinary flow due to the prostate's location around the urethra. Symptoms...
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:22
Ureters