Related Experiment Video
Updated: May 15, 2026


Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Interpreting tacrolimus concentrations during pregnancy and postpartum
Mary F Hebert1, Songmao Zheng, Karen Hays
1Department of Pharmacy, University of Washington, Seattle, WA 98195-7630, USA.

Pregnancy after solid organ transplantation, although considered high risk for maternal, fetal, and neonatal complications, has been quite successful. Tacrolimus pharmacokinetic changes during pregnancy make interpretation of whole blood trough concentrations particularly challenging. There are multiple factors that can increase the fraction of unbound tacrolimus, including but not limited to low albumin concentration and low red blood cell count. The clinical titration of dosage to maintain whole blood tacrolimus trough concentrations in the usual therapeutic range can lead to elevated unbound concentrations and possibly toxicity in pregnant women with anemia and hypoalbuminemia. Measurement of plasma or unbound tacrolimus concentrations for pregnant women might better reflect the active form of the drug, although these are technically challenging and often unavailable in usual clinical practice. Tacrolimus crosses the placenta with in utero exposure being approximately 71% of maternal blood concentrations. The lower fetal blood concentrations are likely due to active efflux transport of tacrolimus from the fetus toward the mother by placental P-glycoprotein. To date, tacrolimus has not been linked to congenital malformations but can cause reversible nephrotoxicity and hyperkalemia in the newborn. In contrast, very small amounts of tacrolimus are excreted in the breast milk and are unlikely to elicit adverse effects in the nursing infant.
Pregnancy after solid organ transplantation, although considered high risk for maternal, fetal, and neonatal complications, has been quite successful. Tacrolimus pharmacokinetic changes during pregnancy make interpretation of whole blood trough concentrations particularly challenging. There are multiple factors that can increase the fraction of unbound tacrolimus, including but not limited to low albumin concentration and low red blood cell count. The clinical titration of dosage to maintain whole blood tacrolimus trough concentrations in the usual therapeutic range can lead to elevated unbound concentrations and possibly toxicity in pregnant women with anemia and hypoalbuminemia. Measurement of plasma or unbound tacrolimus concentrations for pregnant women might better reflect the active form of the drug, although these are technically challenging and often unavailable in usual clinical practice. Tacrolimus crosses the placenta with in utero exposure being approximately 71% of maternal blood concentrations. The lower fetal blood concentrations are likely due to active efflux transport of tacrolimus from the fetus toward the mother by placental P-glycoprotein. To date, tacrolimus has not been linked to congenital malformations but can cause reversible nephrotoxicity and hyperkalemia in the newborn. In contrast, very small amounts of tacrolimus are excreted in the breast milk and are unlikely to elicit adverse effects in the nursing infant.
More Related Videos

Related Concept Videos
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:15
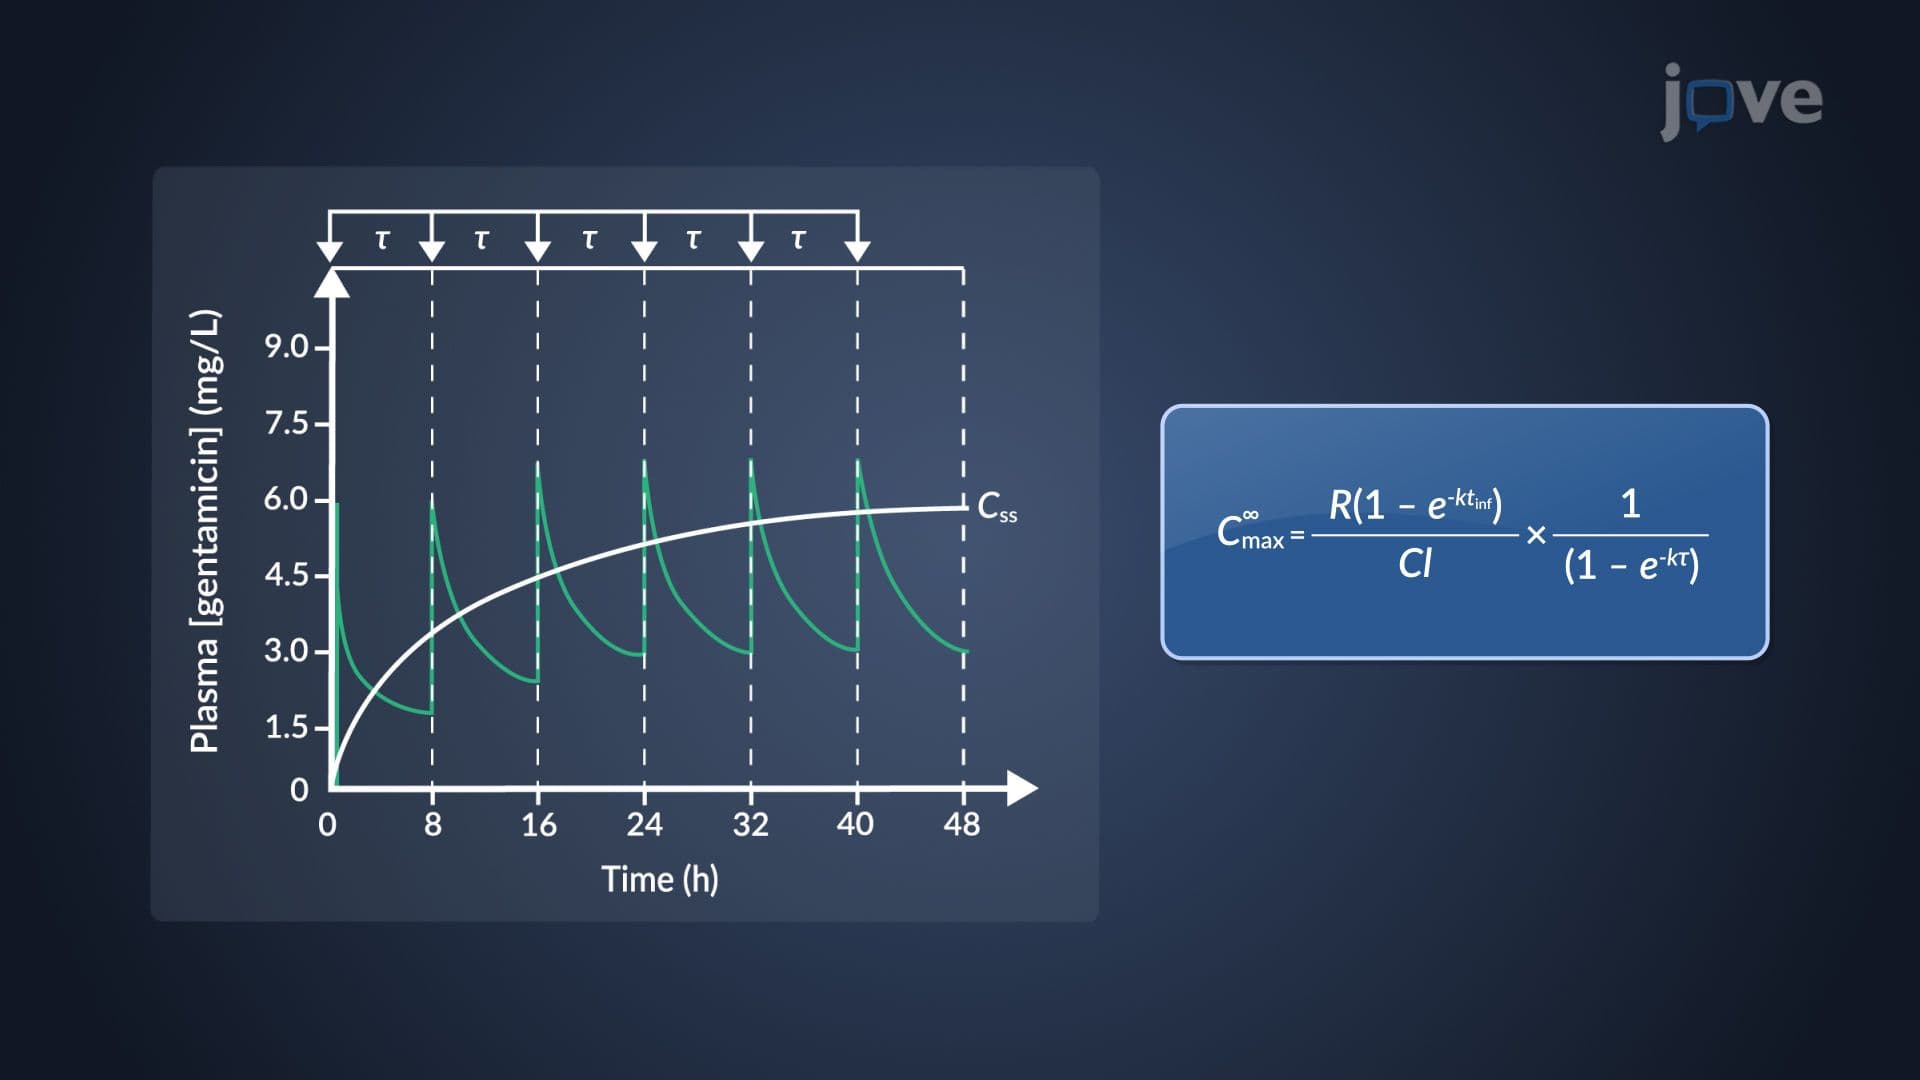
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:15
Drug Concentration Versus Time Correlation
Two pivotal parameters are the minimum effective concentration (MEC) and the minimum toxic concentration (MTC). The MEC is the lowest drug...
 01:26
Therapeutic Drug Monitoring: Drug Analysis Methods
 01:24
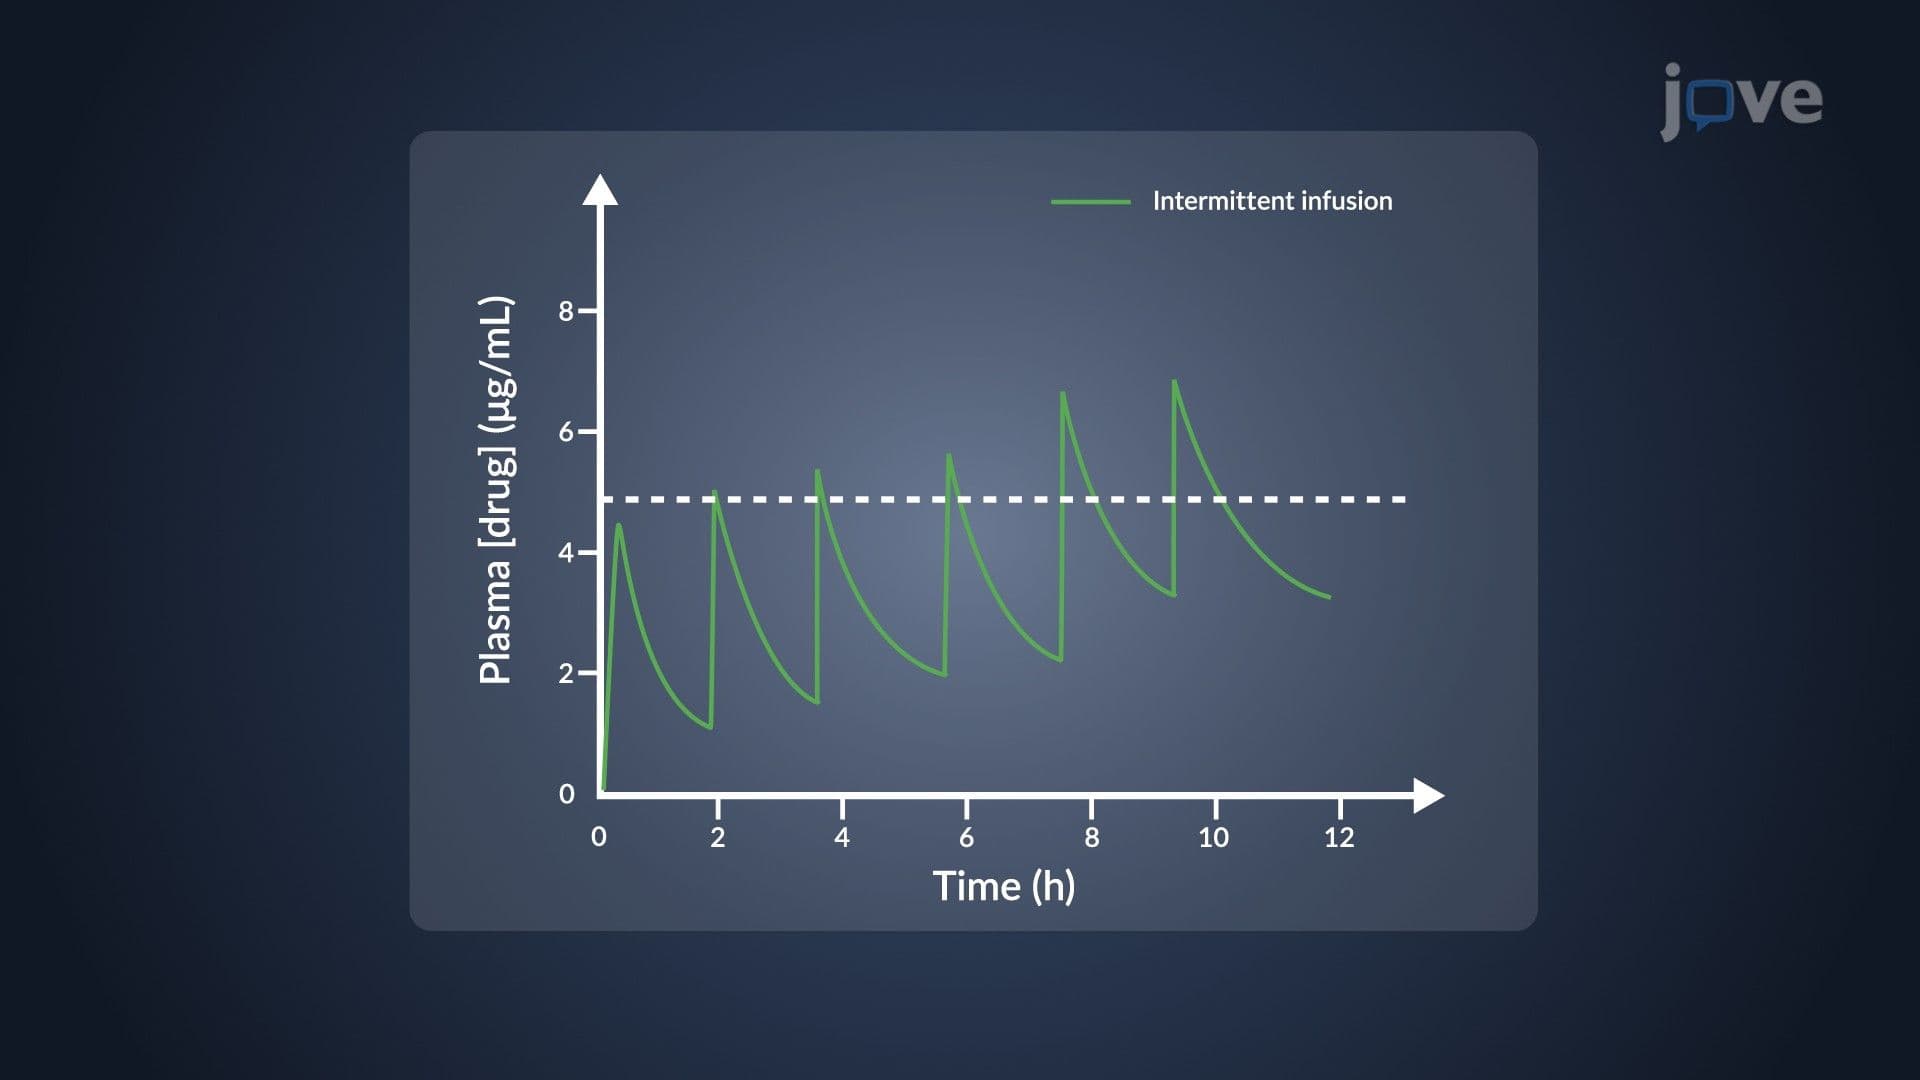
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions