Related Experiment Video
Updated: May 15, 2026


Development of Human Renal Tubular Epithelial Cell Primary Cultures in Monolayers and Three-Dimensional Conditions
Published on: June 13, 2025
Long-term outcomes of Shiga toxin hemolytic uremic syndrome
Joann M Spinale1, Rebecca L Ruebner, Lawrence Copelovitch
1Division of Pediatric Nephrology, Department of Pediatrics, The Children's Hospital of Philadelphia, Philadelphia, PA, USA.

Insights
Shiga toxin-producing E. coli (STEC) hemolytic uremic syndrome (HUS) can cause acute kidney injury (AKI). Long-term kidney damage, including chronic kidney disease and end-stage kidney disease, affects a significant portion of survivors.
Area of Science:
- Nephrology
- Pediatric Nephrology
- Infectious Diseases
Background:
- Shiga toxin-producing Escherichia coli (STEC) hemolytic uremic syndrome (HUS) is a leading cause of acute kidney injury (AKI) in children.
- While acute mortality has decreased, a substantial number of patients experience long-term kidney damage and other sequelae.
Purpose of the Study:
- To review long-term outcomes of STEC-HUS.
- To identify risk factors for poor renal outcomes.
- To establish follow-up guidelines for affected patients.
Main Methods:
- Review of retrospective studies on STEC-HUS patients.
- Analysis of long-term renal and extra-renal sequelae.
- Identification of risk factors for adverse outcomes.
Main Results:
- Renal sequelae include proteinuria (15-30%), hypertension (5-15%), chronic kidney disease (CKD; 9-18%), and end-stage kidney disease (ESKD; 3%).
- Extra-renal sequelae can involve the colon, gallbladder, pancreas, and brain.
- Anuria lasting over 10 days and prolonged dialysis are key predictors of poor renal outcome.
Conclusions:
- Long-term renal sequelae are common after STEC-HUS.
- Extended follow-up is crucial, especially for patients with persistent proteinuria, hypertension, or reduced GFR.
- Risk stratification and indefinite follow-up are recommended for severely affected individuals.
Abstract:
Shiga toxin-producing Escherichia coli (STEC) hemolytic uremic syndrome (HUS) is an important cause of acute kidney injury (AKI). The outcomes of STEC HUS have improved, and the acute mortality rate in children is 1-4%. About 70% of patients recover completely from the acute episode and the remainder have varying degrees of sequelae. Only a few retrospective studies have reviewed these patients over long periods. Methodological flaws include a lack of strict definitions, changing modes of treatment, ascertainment bias and loss of subjects to follow-up. The kidneys bear the brunt of the long-term damage: proteinuria (15-30% of cases); hypertension (5-15%); chronic kidney disease (CKD; 9-18%); and end-stage kidney disease (ESKD; 3%). A smaller number have extra-renal sequelae: colonic strictures, cholelithiasis, diabetes mellitus or brain injury. Most renal sequelae are minor abnormalities, such as treatable hypertension and/or variable proteinuria. Most of the patients who progress to ESKD do not recover normal renal function after the acute episode. Length of anuria (more than 10 days) and prolonged dialysis are the most important risk factors for a poor acute and long-term renal outcome. After the acute episode all patients must be followed for at least 5 years, and severely affected patients should be followed indefinitely if there is proteinuria, hypertension or a reduced glomerular filtration rate (GFR).


Related Concept Videos
 01:18
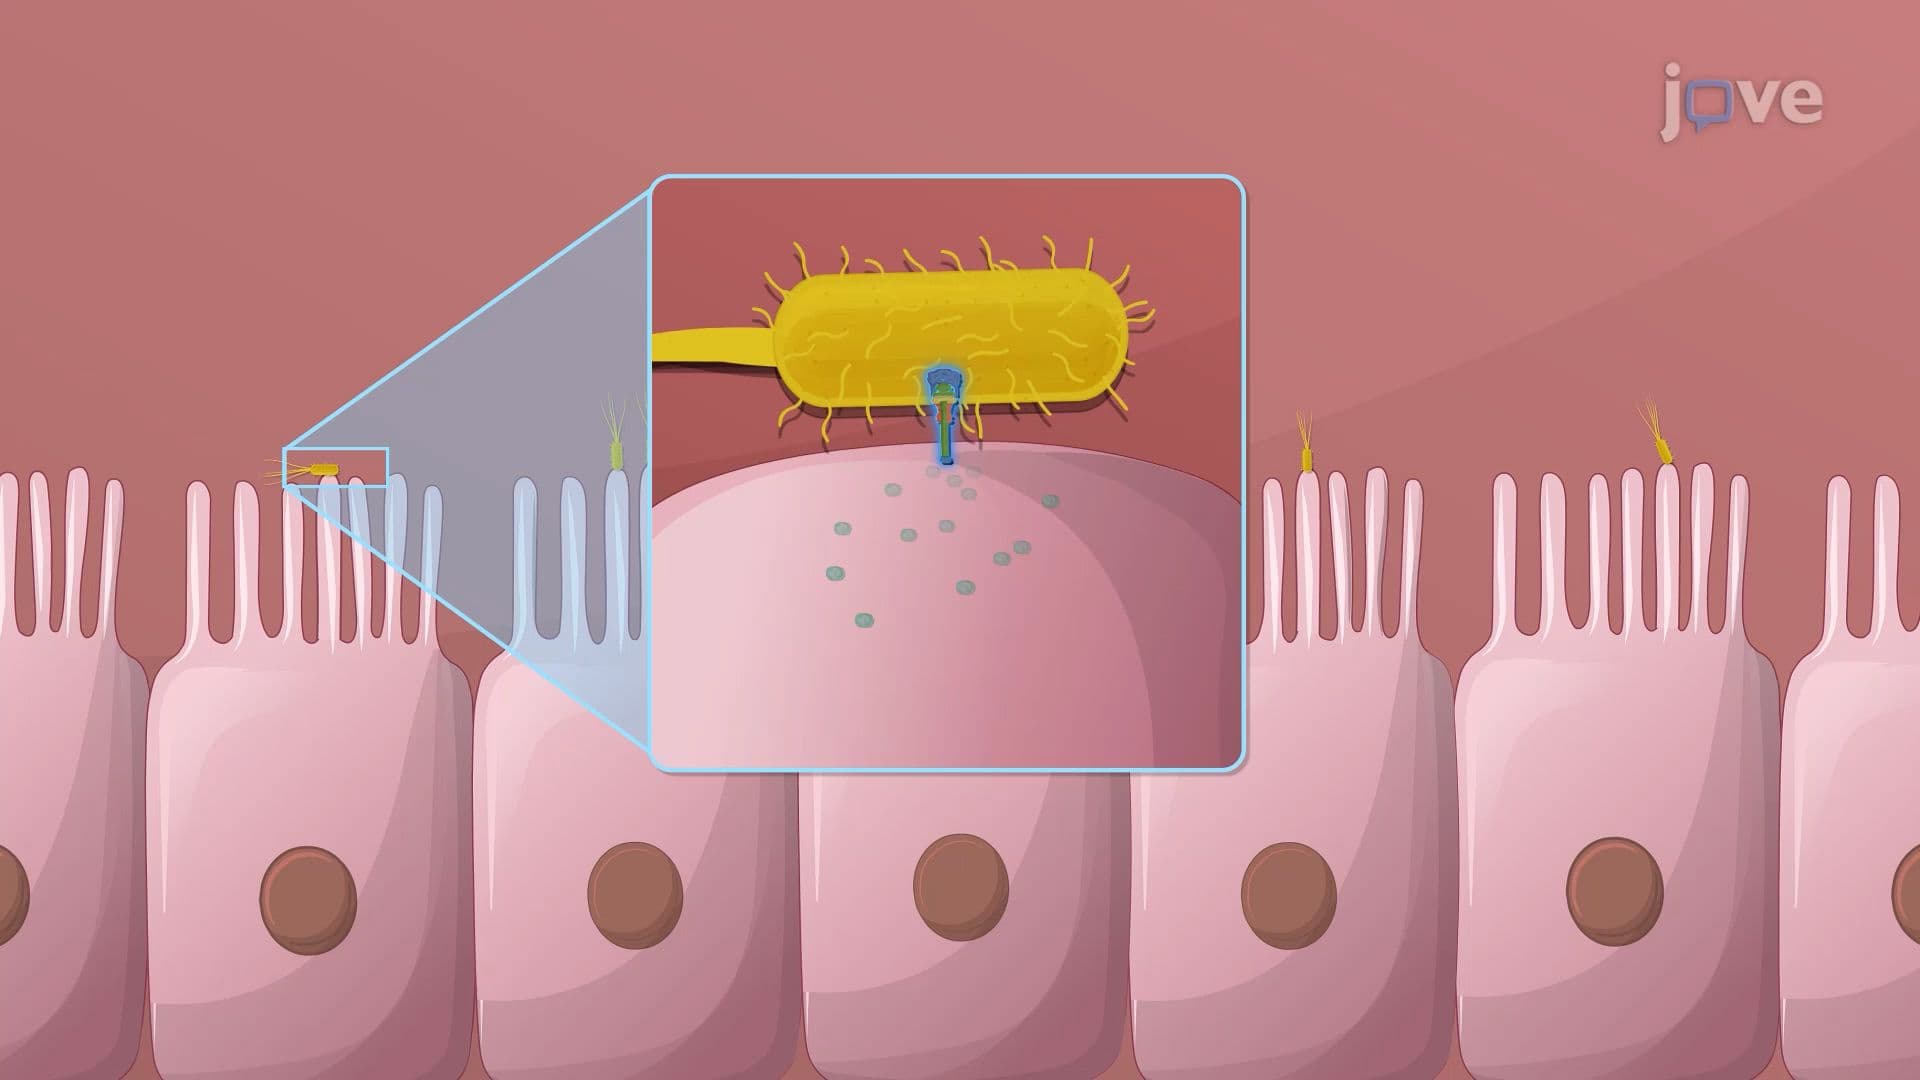
Bacterial Gastroenteritis
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:22
Acute Kidney Injury I: Introduction
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:29
Hepatic Encephalopathy