Bronchodilator responsiveness using spirometry in healthy and asthmatic preschool children
Related Experiment Video
Updated: May 15, 2026
Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
Luis Miguel Borrego1, Janet Stocks, Isabel Almeida
1Departamento de Imunologia, Faculdade de Ciências Médicas, Universidade Nova de Lisboa, Campo dos Mártires da Pátria 123, Lisboa 1150-227, Portugal. borregolm@gmail.com

Insights
Spirometry is repeatable and reproducible in preschool children with asthma. Bronchodilator responsiveness (BDR) can be reliably assessed using FEV(0.75) in wheezy preschoolers.
Area of Science:
- Pediatric Pulmonology
- Respiratory Physiology
- Clinical Trials
Background:
- Spirometry is crucial for diagnosing and monitoring respiratory conditions in children.
- Assessing lung function and bronchodilator responsiveness (BDR) in preschool children presents unique challenges due to variability.
- Reliable spirometry measurements are essential for accurate asthma diagnosis and management in young children.
Purpose of the Study:
- To evaluate the repeatability and reproducibility of spirometry measurements in healthy and asthmatic preschool children aged 3-6 years.
- To determine the reliability of assessing bronchodilator responsiveness (BDR) in this age group.
- To establish reference values for spirometry and BDR in preschool children.
Main Methods:
- Spirometry was conducted before and after administering placebo or salbutamol.
- Measurements were repeated on two separate occasions, 3-23 days apart, to assess reproducibility.
- Forced expired volume in 0.75 s (FEV(0.75)) and forced mid-expiratory flows (FEF(25-75)) were the primary outcome measures.
Main Results:
- Successful spirometry was achieved in 86% of participants.
- Asthmatic children showed significantly lower baseline FEV(0.75) compared to healthy controls.
- Bronchodilator responsiveness (FEV(0.75) increase) was significantly greater in asthmatic children post-salbutamol.
- Between-occasion variability was higher in asthmatic children than in controls.
Conclusions:
- Spirometry measurements, including bronchodilator responsiveness (BDR), can be reliably assessed in preschool children with asthma using FEV(0.75).
- Consideration of within-subject variability and normal responsiveness in healthy children is important for accurate BDR assessment.
- FEV(0.75) is a suitable parameter for evaluating BDR in wheezy preschoolers.
Objective:
To assess repeatability and reproducibility of spirometry measurements, and bronchodilator responsiveness (BDR), in healthy 3-6-year-old preschool children and those with asthma.
Design:
Spirometry was performed before and 20 minutes after administering either inhaled placebo (for repeatability) or 400 μg salbutamol (for BDR) on two separate occasions (reproducibility) 3-23 days apart in asthmatic preschoolers and healthy controls.
Settings:
Lung Function Laboratory, Hospital de Dona Estefania, Lisbon.
Participants:
Healthy preschool children and those with physician-diagnosed asthma, recruited from local Health Clinics and Outpatient Clinic.
Main Outcome Measures:
Paired measurements of forced expired volume in 0.75 s (FEV(0.75)) and forced mid-expiratory flows (FEF(25-75)).
Results:
Technically successful baseline results were obtained in 86% of children assessed. Paired data were obtained in 43 asthmatic and 22 controls (median (range) age: 5.1 (3.4-6.8) years). Baseline FEV(0.75) was significantly lower in asthmatic children (mean (SD): 90 (15)% predicted) than in controls (102 (13) % predicted; p<0.001). Within-occasion coefficient of repeatability following placebo was similar in both groups, being 10.4% in asthma and 13.2% in controls for FEV(0.75). Following bronchodilator, FEV(0.75) increased significantly more in asthmatic preschoolers (mean (SD): 15.0 (12) %) than in controls (4.5 (5) %; p<0.001), with no significant difference between groups post-bronchodilator. Between-occasion variability was similar to within-day repeatability in controls, but almost twice as high in asthmatic children.
Conclusions:
BDR can be assessed reliably using FEV(0.75) in wheezy preschoolers, provided within-subject variability and responsiveness in health are taken into consideration.
Related Concept Videos
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:23
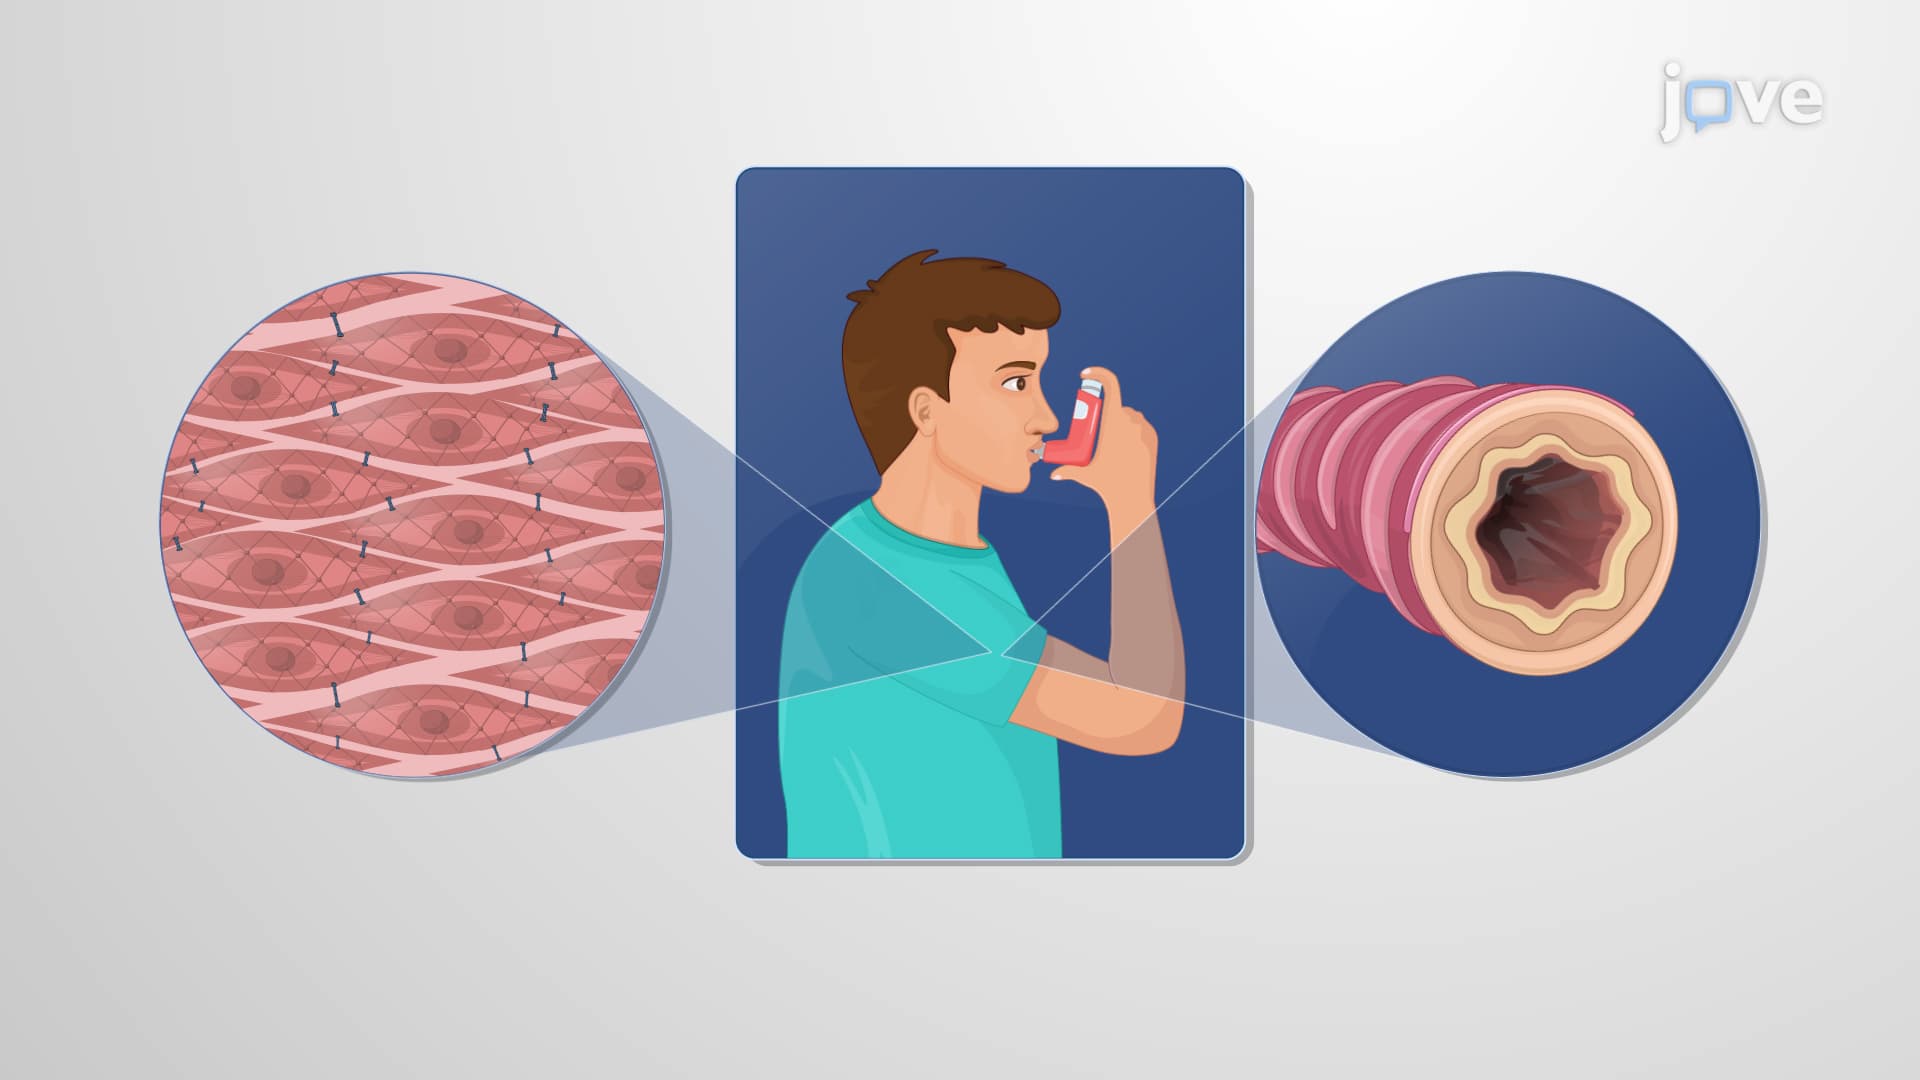
Inhaled Medications
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce relaxation in these...
 01:28
Asthma I: Introduction