Related Experiment Video
Updated: May 15, 2026


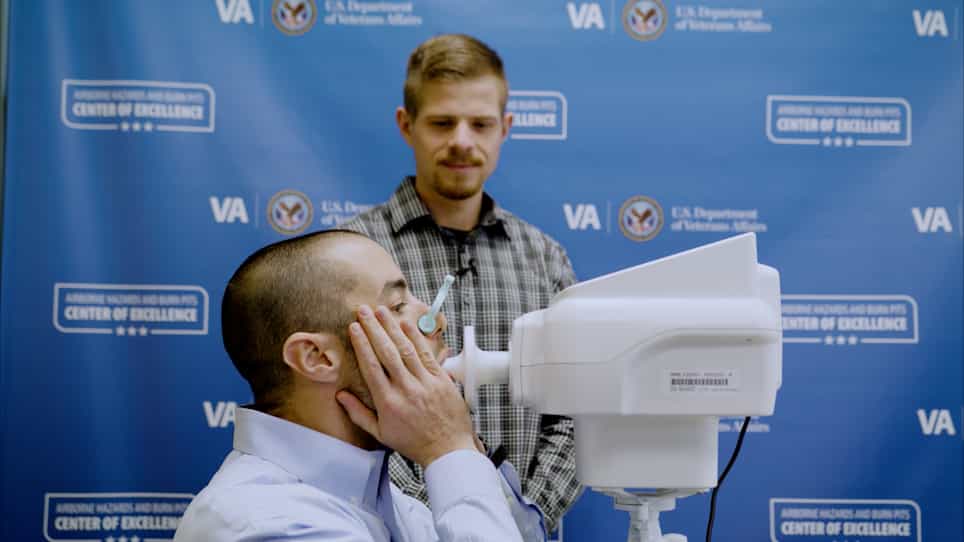
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Use of impulse oscillometry system in assessment of asthma severity for preschool children
Youn Ho Shin1, Jung Won Yoon, Sun Hee Choi
1Department of Pediatrics, CHA University School of Medicine, Seongnam, Republic of Korea.

Insights
Impulse oscillometry system (IOS) measures can help differentiate asthma severity in preschool children, aligning with medication-based classifications. Further research is needed to confirm these findings in larger pediatric asthma studies.
Area of Science:
- Pediatric Pulmonology
- Respiratory Medicine
- Diagnostic Tools
Background:
- Asthma severity classification in preschool children is crucial for effective treatment.
- Current guidelines (NAEPP/EPR-3) categorize asthma based on impairment, risks, and medication.
- Impulse oscillometry system (IOS) is a non-invasive method to assess lung function.
Purpose of the Study:
- To evaluate the consistency of impulse oscillometry system (IOS) measures with asthma severity as defined by the NAEPP/EPR-3 Guidelines in preschool children.
- To determine if IOS can reliably differentiate between intermittent and persistent asthma in young children.
Main Methods:
- 162 preschool children (aged 2-5 years) with asthma were classified by impairment/risks and medication usage.
- Pediatricians determined medication needs, and parents reported symptoms via questionnaires.
- All participants underwent impulse oscillometry system (IOS) testing.
Main Results:
- Asthma severity classifications based on impairment/risks and medication usage showed poor agreement.
- IOS measures (Xrs(5) z-scores) distinguished between intermittent and persistent asthma when severity was defined by medication usage or a combined classification.
- IOS did not significantly differentiate severity based solely on impairment and risks.
Conclusions:
- Impulse oscillometry system (IOS) can differentiate intermittent from persistent asthma in preschool children, particularly when using medication-based severity assessments.
- Larger studies are recommended to validate these findings and explore the underlying mechanisms of IOS in pediatric asthma.
Objective:
The National Asthma Education and Prevention Program/Expert Panel Report (NAEPP/EPR)-3 Guidelines for asthma treatment categorize asthma severity based on impairment and risks and on medications administered. The objective of this study was to determine whether impulse oscillometry system (IOS) measures in preschool children are consistent with asthma severity as defined by NAEPP/EPR-3 Guidelines.
Methods:
Asthma severity of the 162 subjects (aged 2-5 years) was classified by impairment and risks for exacerbations requiring oral systemic corticosteroids, by medication usage, and by combination classification (higher severity of impairment and risks or medication usage). An experienced pediatrician determined the appropriate medications for each child and parents completed structured questionnaires regarding day and night symptoms and interference with normal activity over the preceding 4 weeks. All children were tested by IOS.
Results:
The mean age was 3.7 ± 0.9 years and 91 (56%) of the total patients were males. When asthma severity was based on (1) impairment and risks and (2) medication usage, asthma was "intermittent" in 17.9% and 11.1% of the total patients, "mild persistent" in 42.0% and 50.6% of total patients, and "moderate-severe persistent" in 40.1% and 38.3% of total patients, respectively. The agreement between severity based on impairment and risks and medication usage was not significant. Xrs(5) z-scores differed between intermittent asthma and mild/moderate-severe persistent asthma, as determined by medication usage and combination classification, but not by impairment and risks. As asthma severity (assessed by medication usage) increased, the duration of asthma increased.
Conclusions:
Xrs(5) can be used to discriminate intermittent and persistent asthma in preschool children. Further studies with larger sample sizes are warranted to confirm this finding and to determine the underlying mechanism.
Related Concept Videos
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:13
Asthma III: Clinical Manifestations
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: