Related Experiment Video
Updated: May 15, 2026

Sustained Administration of β-cell Mitogens to Intact Mouse Islets Ex Vivo Using Biodegradable Poly(lactic-co-glycolic acid) Microspheres
Published on: November 5, 2016
Oral delivery of glucagon-like peptide-1 and analogs: alternatives for diabetes control?
Francisca Araújo1, Pedro Fonte, Hélder A Santos
1Department of Pharmaceutical Sciences, Centro de Investigação em Ciências da Saúde, Health Sciences Research Center,Instituto Superior de Ciências da Saúde, CESPU, Gandra, Portugal.

Abstract:
Type 2 diabetes mellitus (T2DM) is one of the most prevalent diseases worldwide. Current treatments are often associated with off-target effects and do not significantly impact disease progression. New therapies are therefore urgently needed to overcome this social burden. Glucagon-like peptide-1 (GLP-1), an incretin hormone, has been used to control T2DM symptomatology. However, the administration of peptide or proteins drugs is still a huge challenge in the pharmaceutical field, requiring administration by parenteral routes. This article reviews the main hurdles in oral administration of GLP-1 and focuses on the strategies utilized to overcome them.
Insights
New therapies for type 2 diabetes mellitus (T2DM) are needed. This review explores challenges and strategies for oral administration of glucagon-like peptide-1 (GLP-1) to improve T2DM treatment.
Area of Science:
- Pharmacology and Endocrinology
- Drug Delivery Systems
Background:
- Type 2 diabetes mellitus (T2DM) is a global health challenge with current treatments having limitations.
- Glucagon-like peptide-1 (GLP-1) shows therapeutic potential for T2DM but faces administration challenges.
Purpose of the Study:
- To review the obstacles hindering oral administration of GLP-1.
- To highlight innovative strategies for overcoming these barriers in GLP-1 drug delivery.
Main Methods:
- Literature review of existing research on GLP-1 and oral drug delivery technologies.
- Analysis of challenges including peptide degradation and low bioavailability.
- Examination of formulation and delivery strategies to enhance oral absorption.
Main Results:
- Oral administration of GLP-1 is impeded by gastrointestinal degradation and poor membrane permeability.
- Various strategies, including chemical modification, nano-encapsulation, and absorption enhancers, are being explored.
- These approaches aim to protect GLP-1 and facilitate its uptake for improved T2DM management.
Conclusions:
- Overcoming the hurdles of oral GLP-1 administration is crucial for developing more convenient T2DM therapies.
- Successful oral delivery systems could significantly improve patient compliance and therapeutic outcomes.
- Continued research into advanced drug delivery is essential for realizing the full potential of GLP-1 for type 2 diabetes.
Related Concept Videos
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:06
Oral Hypoglycemic Agents: Glinides
 01:15
Hypoglycemia and Glucagon
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into rapid-acting...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:25
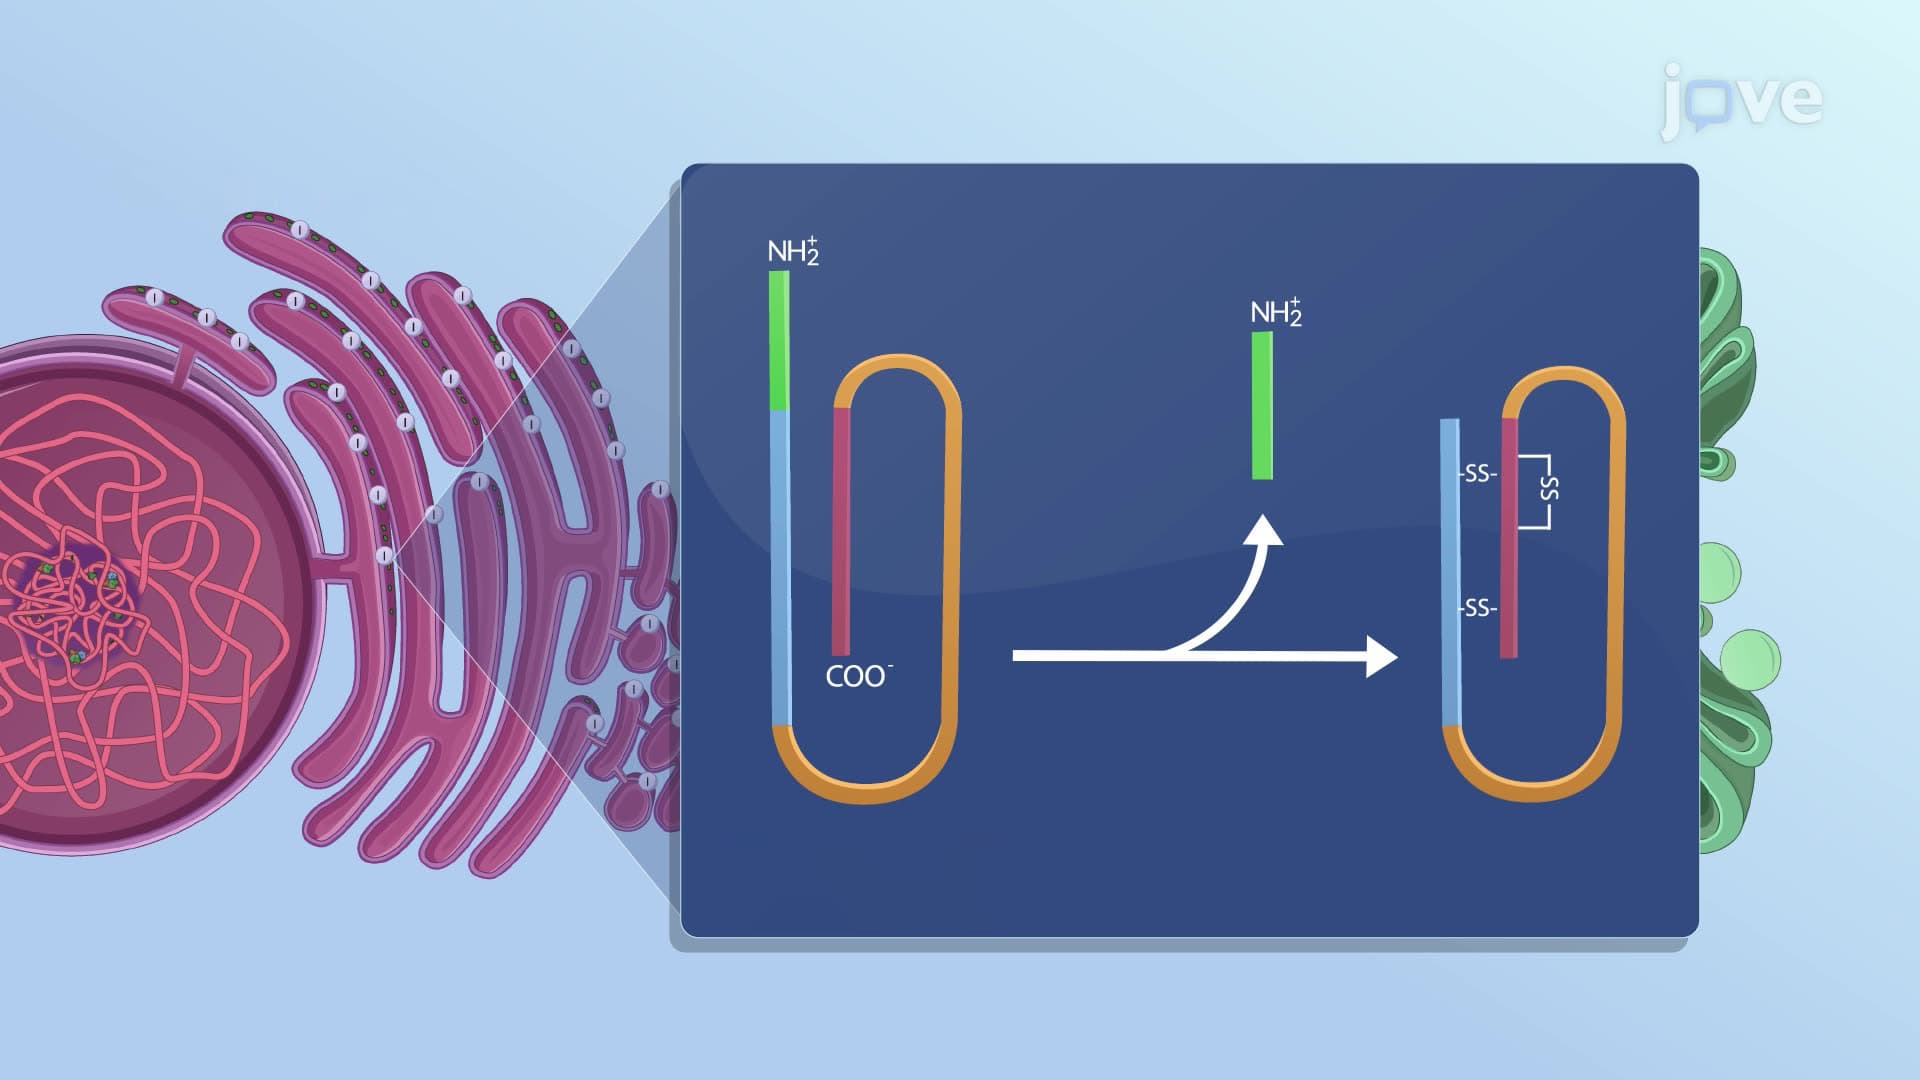
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...