Related Experiment Video
Updated: Jul 29, 2026
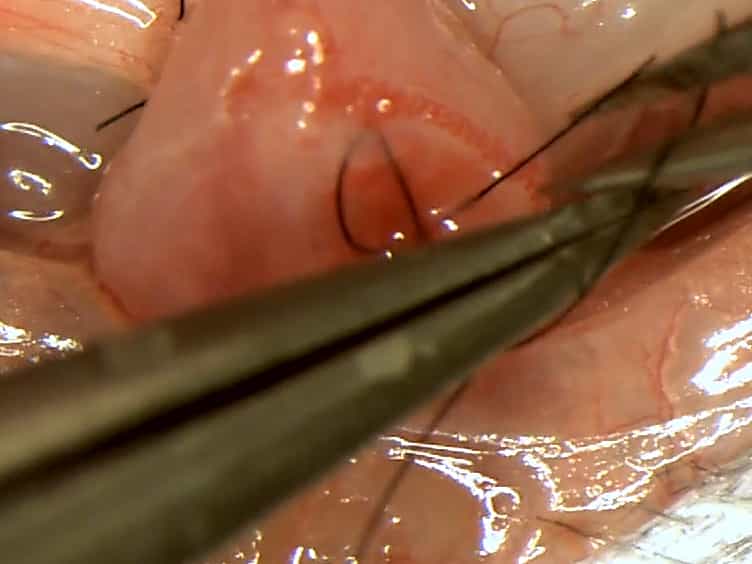
Murine Kidney Transplant Technique
Published on: October 20, 2015
Ten years of training community urologists and general surgeons to do cadaver kidney retrievals
J M Barry1, T R Hefty, K A Nelson
1Division of Urology and Renal Transplantation, Oregon Health Sciences University, Portland 97201.

Abstract:
We trained 82 community hospital cadaver kidney retrieval teams during a 10-year period ending June 30, 1987. During the last 5 years of that period the concept of multiple organ retrieval was introduced into the training sessions and 429 cadaver kidney grafts were retrieved. Of those kidneys 292 were transplanted at our hospital, and the function of 220 cadaver kidney grafts retrieved by the community hospital teams was compared to that of 72 retrieved by the transplant center retrieval team. Of the cadaver kidney transplants 114 were from multiple organ donors. There was no significant difference in 1-month serum creatinine nadir of surviving grafts (2.1 +/- 1.8 versus 1.9 +/- 1.7 mg. per dl.), 6-month serum creatinine level (1.7 +/- 0.8 versus 1.6 +/- 0.6 mg. per dl.), 12-month serum creatinine level (1.8 +/- 0.9 versus 1.6 +/- 0.6 mg. per dl.) and 5-year actuarial graft survival (44.8 +/- 4.1 versus 52.4 +/- 7.5%), with the community hospital data presented first. The delayed graft function rate was significantly higher in the recipients of cadaver kidney grafts retrieved by community hospital teams (54 versus 35%), which was reduced by the in situ flush technique. There was no significant difference in delayed graft function rate (48 versus 40%) for the 114 cadaver kidney transplants retrieved from multiple organ donors by either community hospital or transplant center teams. With continuing education and quality control, community hospital retrieval teams can provide kidneys satisfactory for transplantation, even when working with multiple organ retrieval teams.
Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure