Related Experiment Video
Updated: May 15, 2026


Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
Larger interventricular conduction time enhances mechanical response to resynchronization therapy
Luigi Padeletti1, Paolo Pieragnoli, Giuseppe Ricciardi
1Institute of Internal Medicine and Cardiology, University of Florence, Florence, Italy. lpadeletti@interfree.it

Insights
Optimizing cardiac resynchronization therapy (CRT) involves finding the best left ventricular (LV) pacing site. Measuring right ventricular (RV)-to-LV conduction time helps identify optimal LV lead placement for improved systolic function.
Area of Science:
- Cardiology
- Electrophysiology
- Medical Devices
Background:
- Left ventricular (LV) pacing site significantly impacts hemodynamic response in cardiac resynchronization therapy (CRT).
- Current lead positioning in lateral or posterolateral cardiac veins may not be universally optimal.
- Individualized LV lead placement is crucial for effective CRT.
Purpose of the Study:
- To evaluate the relationship between right ventricular (RV)-to-LV conduction time and systolic function during CRT.
- To assess if RV-to-LV conduction time can predict optimal LV pacing site.
- To analyze changes in LV pressure-volume loops based on pacing site and AV delay.
Main Methods:
- Utilized conductance catheter to measure LV pressure and volume in 10 patients during CRT implantation.
- Systematically assessed four endocardial LV sites across four atrioventricular delays.
- Measured RV-to-LV conduction time as the interval between spontaneous peak R waves from RV lead and LV catheter.
Main Results:
- Optimal pacing site varied among patients.
- Pacing at the site with maximum RV-to-LV conduction time yielded stroke volume improvement comparable to individually optimized sites (41 ± 17 mL vs 44 ± 18 mL, P = 0.266).
- RV-to-LV conduction time positively correlated with increases in stroke volume (r = 0.537), stroke work (r = 0.642), and pressure-derivative maximum (r = 0.646).
Conclusions:
- Optimal acute CRT response can be achieved by placing the LV lead at the site with maximum RV-to-LV conduction time.
- A significant correlation exists between RV-to-LV conduction time and CRT-induced systolic function improvement.
- RV-to-LV conduction time serves as a valuable predictor for LV lead positioning in CRT.
Background:
Previous studies have reported that the left ventricular (LV) pacing site is a major determinant of the hemodynamic response to cardiac resynchronization therapy (CRT). However, lead positioning in a lateral or posterolateral cardiac vein may not be optimal for every patient. The objective of this study was to assess the relationship between the right ventricular (RV)-to-LV conduction time and the systolic function during CRT on the basis of changes to LV pressure-volume loops.
Methods:
Left ventricular pressure and volume data were determined using a conductance catheter during CRT device implantation in 10 patients. Four endocardial LV sites were systematically assessed at four atrioventricular delays. The RV-to-LV conduction time was measured as the time interval between spontaneous peak R waves, recorded through the RV lead and the LV catheter.
Results:
The optimal pacing site varied among patients. However, the pacing site associated with the maximum RV-to-LV conduction time resulted in a stroke volume improvement comparable to the pacing site identified through individual hemodynamic optimization (41 ± 17 mL vs 44 ± 18 mL, P = 0.266). Moreover, the RV-to-LV conduction time recorded at each endocardial pacing site correlated positively with the increase in stroke volume (r = 0.537; P < 0.001), stroke work (r = 0.642; P < 0.001), and the pressure-derivative maximum (r = 0.646; P < 0.001) obtained with CRT.
Conclusions:
An optimal acute response to CRT can be obtained by positioning the LV lead at the site associated with the maximum RV-to-LV conduction time. A significant correlation appears to exist between RV-to-LV conduction time and the improvement in systolic function with CRT.


Related Concept Videos
 01:19
Conduction System of the Heart
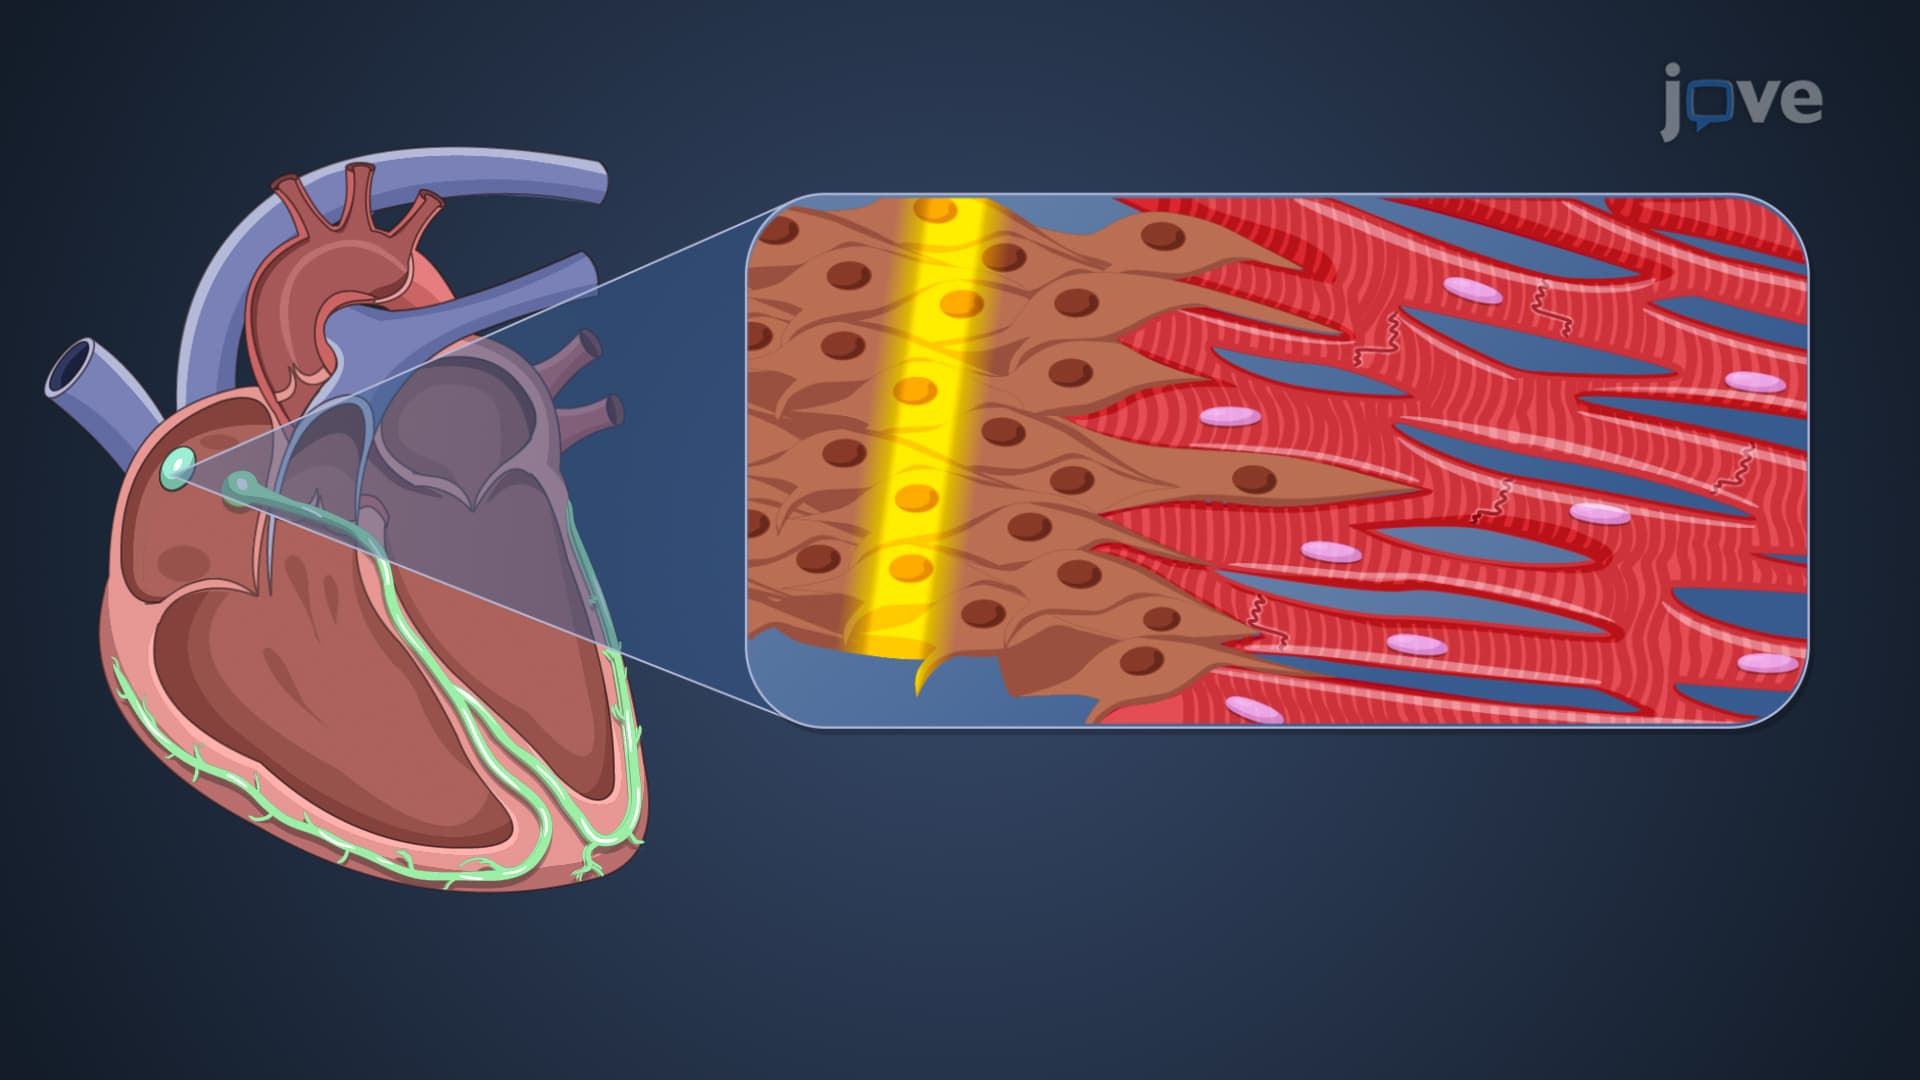
The pacemaker cells are located in two primary nodes: the sinoatrial (SA) node and the atrioventricular (AV) node. The SA node pacemaker cells can autonomously depolarize, triggering an action potential that leads to the...
 01:20
Conduction System of the Heart
This system relies on the unique properties of nodal and Purkinje cells:...
 01:27
Specialized Characteristics of Cardiac Muscles
Cardiac muscle cells are smaller than skeletal muscles, averaging 10–20 mm in diameter and 50–100 mm in length. However, they have large energy demands for continuous contraction and relaxation. This energy is almost exclusively derived from aerobic metabolism of energy reserves in...
 01:19
Electrophysiology of Normal Cardiac Rhythm
 01:25
Dysrhythmias VI: Management of Dysrhythmias
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy