Related Experiment Video
Updated: May 15, 2026
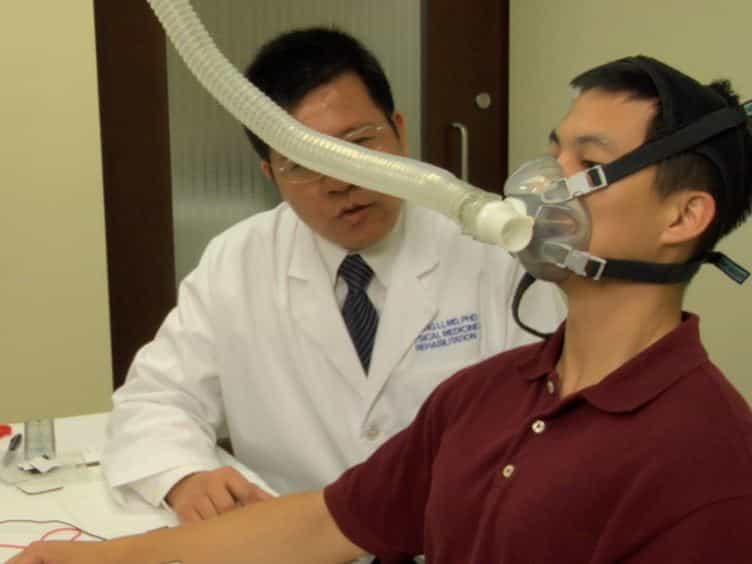

Breathing-controlled Electrical Stimulation (BreEStim) for Management of Neuropathic Pain and Spasticity
Published on: January 10, 2013
Respiratory muscle tension as symptom generator in individuals with high anxiety sensitivity
Thomas Ritz1, Alicia E Meuret, Lavanya Bhaskara
1Department of Psychology, Southern Methodist University, PO Box 750442, Dallas, TX 75275-0442, USA. tritz@smu.edu

Objective:
Anxiety and panic are associated with the experience of a range of bodily symptoms, in particular unpleasant breathing sensations (dyspnea). Respiratory theories of panic disorder have focused on disturbances in blood gas regulation, but respiratory muscle tension as a source of dyspnea has not been considered. We therefore examined the potential of intercostal muscle tension to elicit dyspnea in individuals with high anxiety sensitivity, a risk factor for developing panic disorder.
Methods:
Individuals high and low in anxiety sensitivity (total N=62) completed four tasks: electromyogram biofeedback for tensing intercostal muscle, electromyogram biofeedback for tensing leg muscles, paced breathing at three different speeds, and a fine motor task. Global dyspnea, individual respiratory sensations, nonrespiratory sensations, and discomfort were assessed after each task, whereas respiratory pattern (respiratory inductance plethysmography) and end-tidal carbon dioxide (capnography) were measured continuously.
Results:
In individuals with high compared to low anxiety sensitivity, intercostal muscle tension elicited a particularly strong report of obstruction (M=5.1, SD=3.6 versus M=2.5, SD=3.0), air hunger (M=1.9, SD=2.1 versus M=0.4, SD=0.8), hyperventilation symptoms (M=0.6, SD=0.6 versus M=0.1, SD=0.1), and discomfort (M=5.1, SD=3.2 versus M=2.2, SD=2.1) (all p values<.05). This effect was not explained by site-unspecific muscle tension, voluntary manipulation of respiration, or sustained task-related attention. Nonrespiratory control sensations were not significantly affected by tasks (F<1), and respiratory variables did not reflect any specific responding of high-Anxiety Sensitivity Index participants to intercostal muscle tension.
Conclusions:
Respiratory muscle tension may contribute to the respiratory sensations experienced by panic-prone individuals. Theories and treatments for panic disorder should consider this potential source of symptoms.
Related Concept Videos
 01:13
Asthma III: Clinical Manifestations
 01:25
Hyperpnea and Hyperventilation
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes include...
 01:28
Asthma I: Introduction
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:29
Asthma-I: Introduction