Related Experiment Video
Updated: May 15, 2026
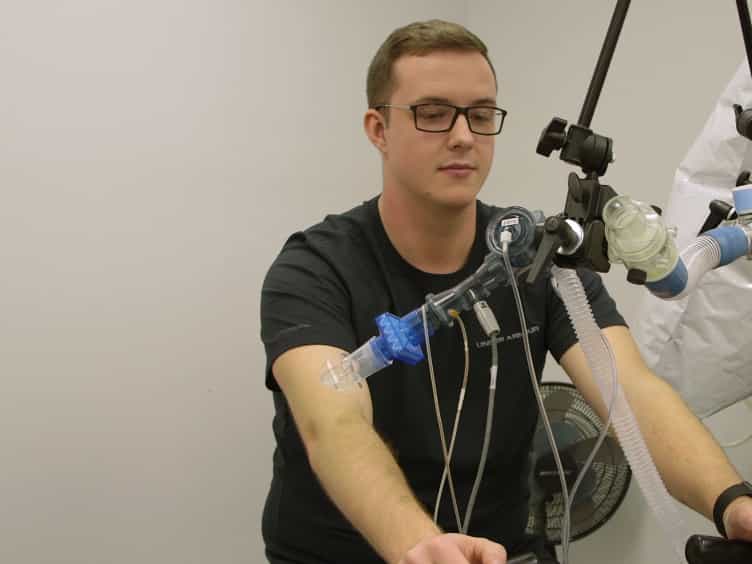
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Loss of alveolar membrane diffusing capacity and pulmonary capillary blood volume in pulmonary arterial hypertension
Samar Farha1, Daniel Laskowski, Deepa George
1Respiratory Institute, Cleveland Clinic, Cleveland, OH 44195, USA. farhas@ccf.org

Background:
Reduced gas transfer in patients with pulmonary arterial hypertension (PAH) is traditionally attributed to remodeling and progressive loss of pulmonary arterial vasculature that results in decreased capillary blood volume available for gas exchange.
Methods:
We tested this hypothesis by determination of lung diffusing capacity (DL) and its components, the alveolar capillary membrane diffusing capacity (D(m)) and lung capillary blood volume (V(c)) in 28 individuals with PAH in comparison to 41 healthy individuals, and in 19 PAH patients over time. Using single breath simultaneous measure of diffusion of carbon monoxide (DL(CO)) and nitric oxide (DL(NO)), DL and D(m) were respectively determined, and V(c) calculated. D(m) and V(c) were evaluated over time in relation to standard clinical indicators of disease severity, including brain natriuretic peptide (BNP), 6-minute walk distance (6MWD) and right ventricular systolic pressure (RVSP) by echocardiography.
Results:
Both DL(CO) and DL(NO) were reduced in PAH as compared to controls and the lower DL in PAH was due to loss of both D(m) and V(c) (all p < 0.01). While DL(CO) of PAH patients did not change over time, DL(NO) decreased by 24 ml/min/mmHg/year (p = 0.01). Consequently, D(m) decreased and V(c) tended to increase over time, which led to deterioration of the D(m)/V(c) ratio, a measure of alveolar-capillary membrane functional efficiency without changes in clinical markers.
Conclusions:
The findings indicate that lower than normal gas transfer in PAH is due to loss of both D(m) and V(c), but that deterioration of D(m)/V(c) over time is related to worsening membrane diffusion.


Related Concept Videos
 01:10
Atelectasis II: Pathophysiology
 01:18
Pulmonary Edema II: Pathophysiology
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue, improving...