Related Experiment Video
Updated: May 14, 2026


Establishment of an Experimental Mouse Model of Endometrioma to Study its Related Infertility
Published on: April 5, 2024
Persistent ovarian masses and pregnancy outcomes
William A Goh1, Monica Rincon, Justin Bohrer
1Department of Obstetrics, Gynecology & Women's Health, John A. Burns School of Medicine, University of Hawaii, Honolulu, HI 96826, USA. wgoh@hawaii.edu

Objective:
To determine if persistent ovarian masses in pregnancy are associated with increased adverse outcomes.
Methods:
This is a retrospective cohort of 126 pregnant women with a persistent ovarian mass measuring 5 cm or greater who delivered at two university hospitals between 2001 and 2009. Maternal outcomes included gestational age (GA) at diagnosis, delivery and surgery as well as miscarriage, preterm birth (PTB), ovarian torsion and hospital admission for pain. Neonatal outcomes included birth weight, respiratory distress syndrome (RDS), intra-ventricular hemorrhage (IVH), death and sepsis.
Results:
A total of 1225 ovarian masses were identified (4.9%) in 24,868 patients. A persistent ovarian mass was found in 0.7%. Average GA at diagnosis was 17.8 weeks. Miscarriage rate was 3.3%. Average GA at delivery was 37.9 weeks. Of the patients, 8.5% had ovarian torsion, 10.3% had admission for pain and 9.3% had PTBs. The mean cesarean delivery rate was 46.3%. The average neonatal weight was 3273 g. There was one neonatal death in this cohort. The rate of RDS was 2.8%, IVH 0.9% and neonatal sepsis 1.9%. The most common surgical pathologic diagnosis was dermoids (37.6%). No overt malignancies were seen.
Conclusion:
A persistent ovarian mass in pregnancy does not confer an increased risk of adverse pregnancy outcomes.

Related Concept Videos
 02:07
Oogenesis
 01:27
Ovarian Cycle
 01:24
Disorders of the Female Reproductive System
 01:28
Infertility in Females
Endometriosis, a condition characterized by abnormal growth of endometrial...
 01:26
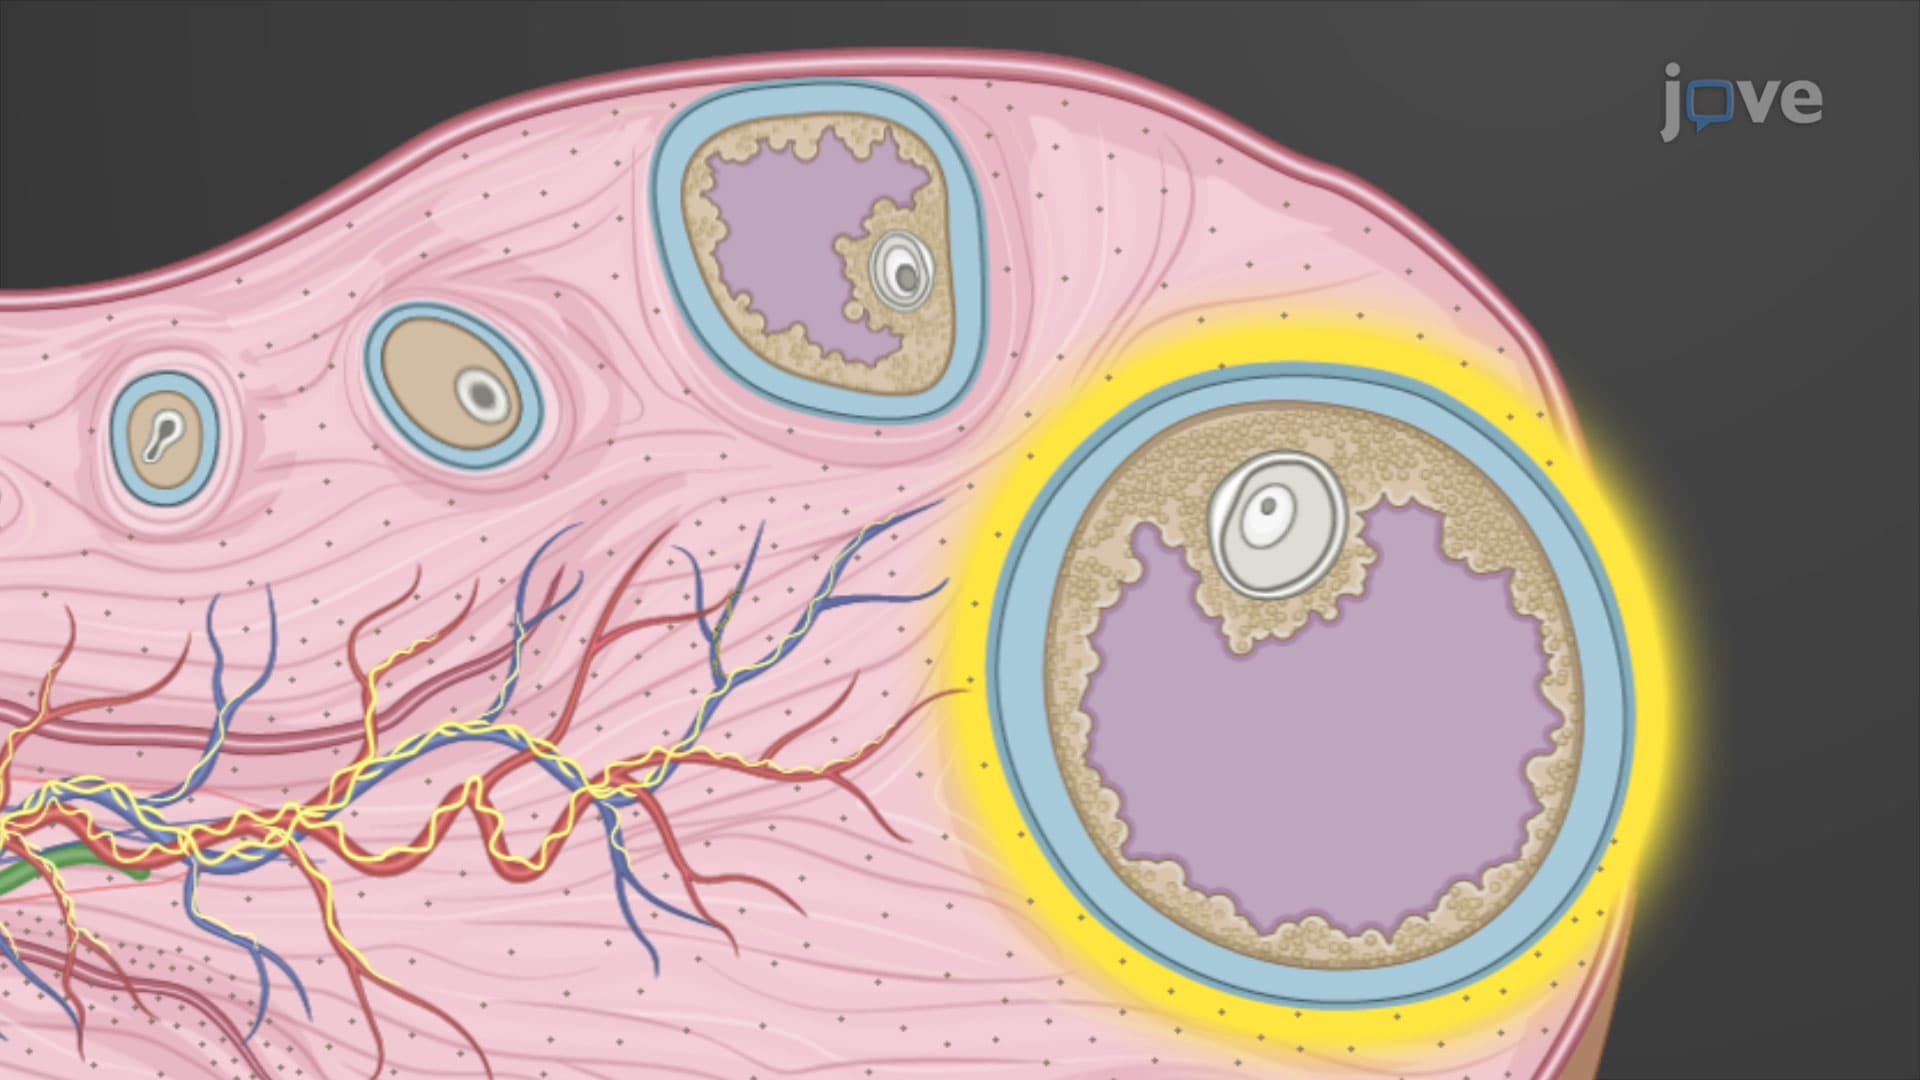
Ovaries
On the ovarian surface, a layer of cuboidal...
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...