Related Experiment Video
Updated: May 14, 2026
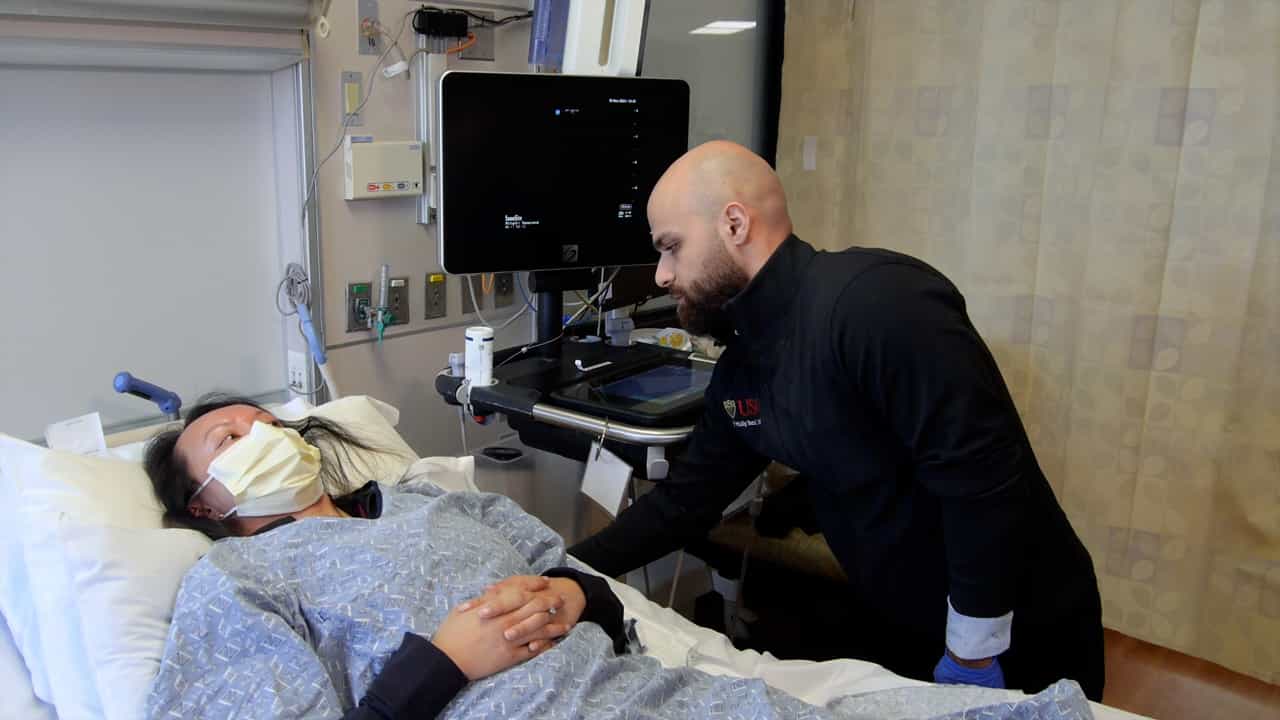
Point of Care Transcranial Color-Coded Duplex Ultrasound of the Middle Cerebral Artery
Published on: August 9, 2024
Physiological impact of CTO recanalization assessed by coronary pressure measurement: a case report
Hitoshi Matsuo1, Yoshiaki Kawase
1The Department of Cardiovascular Medicine, Gifu Heart Center, Gifu, Japan.

Insights
Opening chronic total occlusions (CTOs) improves blood flow not only to the affected artery but also to the donor artery via collateral channels. This enhances myocardial perfusion significantly.
Area of Science:
- Cardiology
- Interventional Cardiology
- Physiology
Background:
- Chronic total occlusions (CTOs) present complex challenges in coronary artery disease management.
- Assessing myocardial perfusion and collateral circulation is crucial for treatment decisions.
Observation:
- A case report details physiological changes in myocardial perfusion using intracoronary pressure measurement.
- Intra-coronary pressure assessment was performed before and after revascularization of a right coronary artery (RCA) CTO.
- Collateral flow from the left anterior descending artery (LAD) to the RCA was observed in a patient with silent myocardial ischemia.
Findings:
- Revascularization of the RCA CTO increased the fractional flow reserve (FFRmyo) of the RCA from 0.67 to 0.90, indicating a 23% increase in maximum flow.
- Interestingly, FFRmyo of the donor LAD also improved from 0.81 to 0.93 (12% increase in maximum flow).
- Coronary steal phenomenon was confirmed in the LAD during RCA balloon occlusion, suggesting immediate collateral recruitment.
Implications:
- CTO revascularization improves myocardial perfusion in the territory of the occluded vessel.
- Perfusion improvement extends to the territory supplied by the collateral donor artery, challenging previous assumptions.
- This highlights the significant hemodynamic impact of CTO revascularization on the entire coronary system.
Abstract:
In this case report, physiological changes of myocardial perfusion in the collateral recipient right coronary artery (RCA) and the collateral donor left anterior descending artery (LAD) with an intermediate lesion were assessed using intracoronary pressure measurement, before and after revascularization of chronic total occlusion (CTO). A 44-year-old male was referred for a catheter examination due to silent myocardial ischemia. An invasive coronary angiogram revealed diffuse narrowing of the RCA with focal occlusive segments in addition to intermediate stenosis in the LAD. A well developed collateral channel from the LAD to the RCA was also confirmed. Fractional flow reserve (FFRmyo) of the LAD before opening the RCA was 0.81. After successful revascularization of the RCA, FFRmyo of the LAD and the RCA were measured with and without an RCA balloon occlusion. Because collateral fractional flow reserve (FFRcoll) of the RCA could be regarded as FFRmyo before revascularization, FFRmyo of the RCA increased from 0.67 to 0.90, meaning a 23% increase of maximum flow by intervention. Interestingly, improvement of FFRmyo of the LAD from 0.81 to 0.93 was also observed, which means a 12% increase of maximum flow. Coronary steal in the LAD was reconfirmed by dramatic worsening of FFRmyo from 0.93 to 0.77 by an RCA balloon occlusion. This phenomenon may be explained by an immediate recruitment of collateral channels. This case clearly demonstrated that CTO opening improves perfusion in not only myocardium supplied by the CTO vessel, but also in that which is supplied by a contralateral collateral donor artery.
