Related Experiment Videos
Population pharmacokinetics of tranexamic acid in paediatric patients undergoing craniosynostosis surgery
Susan M Goobie1, Petra M Meier, Navil F Sethna
1Department of Anesthesia, Perioperative and Pain Medicine, Boston Children's Hospital, Harvard Medical School, 300 Longwood Avenue, Boston, MA 02115, USA. Susan.Goobie@childrens.harvard.edu

Insights
This study developed a new dosing regimen for tranexamic acid (TXA) in children undergoing craniofacial surgery. The optimized regimen uses lower initial doses to reduce peak concentrations while maintaining effective therapeutic levels.
Area of Science:
- Pharmacology
- Pediatric Surgery
- Pharmacokinetics
Background:
- Tranexamic acid (TXA) is crucial for reducing blood loss in craniofacial surgery.
- Paediatric pharmacokinetic data for TXA is limited, leading to varied dosing practices.
- Population pharmacokinetic analysis is needed to optimize TXA dosing in children.
Purpose of the Study:
- To perform a population pharmacokinetic analysis of TXA in paediatric patients.
- To develop a predictive model for effective TXA dosing during cranial remodelling procedures.
- To optimize TXA regimens for children with craniosynostosis.
Main Methods:
- Utilized data from a placebo-controlled efficacy trial's treatment arm.
- Analyzed TXA plasma concentrations from 23 paediatric patients.
- Employed a non-linear mixed-effects modeling strategy (Monolix, NONMEM).
Main Results:
- A two-compartment model described TXA pharmacokinetics, influenced by bodyweight and age.
- Systemic clearance (CL) and central volume of distribution (V1) depended on bodyweight and age.
- Simulations indicated lower loading doses maintain therapeutic levels with reduced peak concentrations.
Conclusions:
- A two-compartment model incorporating bodyweight and age effectively characterized TXA disposition.
- A simulated regimen of 10 mg/kg loading dose followed by 5 mg/kg/h maintenance infusion maintains TXA levels above 16 μg/mL.
- This optimized TXA dosing reduces high initial peaks compared to previous regimens.
Background:
Tranexamic acid (TXA) effectively reduces blood loss and transfusion requirements during craniofacial surgery. The pharmacokinetics of TXA have not been fully characterized in paediatric patients and dosing regimens remain diverse in practice. A mixed-effects population analysis would characterize patient variability and guide dosing practices.
Objective:
The objective of this study was to conduct a population pharmacokinetic analysis and develop a model to predict an effective TXA dosing regimen for children with craniosynostosis undergoing cranial remodelling procedures.
Methods:
The treatment arm of a previously reported placebo-controlled efficacy trial was analysed. Twenty-three patients with a mean age 23 ± 19 months received a TXA loading dose of 50 mg/kg over 15 min at a constant rate, followed by a 5 mg/kg/h maintenance infusion during surgery. TXA plasma concentrations were measured and modelled with a non-linear mixed-effects strategy using Monolix 4.1 and NONMEM(®) 7.2.
Results:
TXA pharmacokinetics were adequately described by a two-compartment open model with systemic clearance (CL) depending on bodyweight (WT) and age. The apparent volume of distribution of the central compartment (V1) was also dependent on bodyweight. Both the inter-compartmental clearance (Q) and the apparent volume of distribution of the peripheral compartment (V2) were independent of any covariate. The final model may be summarized as: CL (L/h) = [2.3 × (WT/12)(1.59) × AGE(-0.0934)] × e(η1), V1 (L) = [2.34 × (WT/12)(1.4)] × e(η2), Q (L/h) = 2.77 × e(η3) and V2 (L) = 1.53 × e(η4), where each η corresponds to the inter-patient variability for each parameter. No significant correlation was found between blood volume loss and steady-state TXA concentrations. Based on this model and simulations, lower loading doses than used in the clinical study should produce significantly lower peak concentrations while maintaining similar steady-state concentrations.
Conclusions:
A two-compartment model with covariates bodyweight and age adequately characterized the disposition of TXA. A loading dose of 10 mg/kg over 15 min followed by a 5 mg/kg/h maintenance infusion was simulated to produce steady-state TXA plasma concentrations above the 16 μg/mL threshold. This dosing scheme reduces the initial high peaks observed with the larger dose of 50 mg/kg over 15 min used in our previous clinical study.
Related Concept Videos
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:29
Drug Dosing: Infants and Children
 01:15
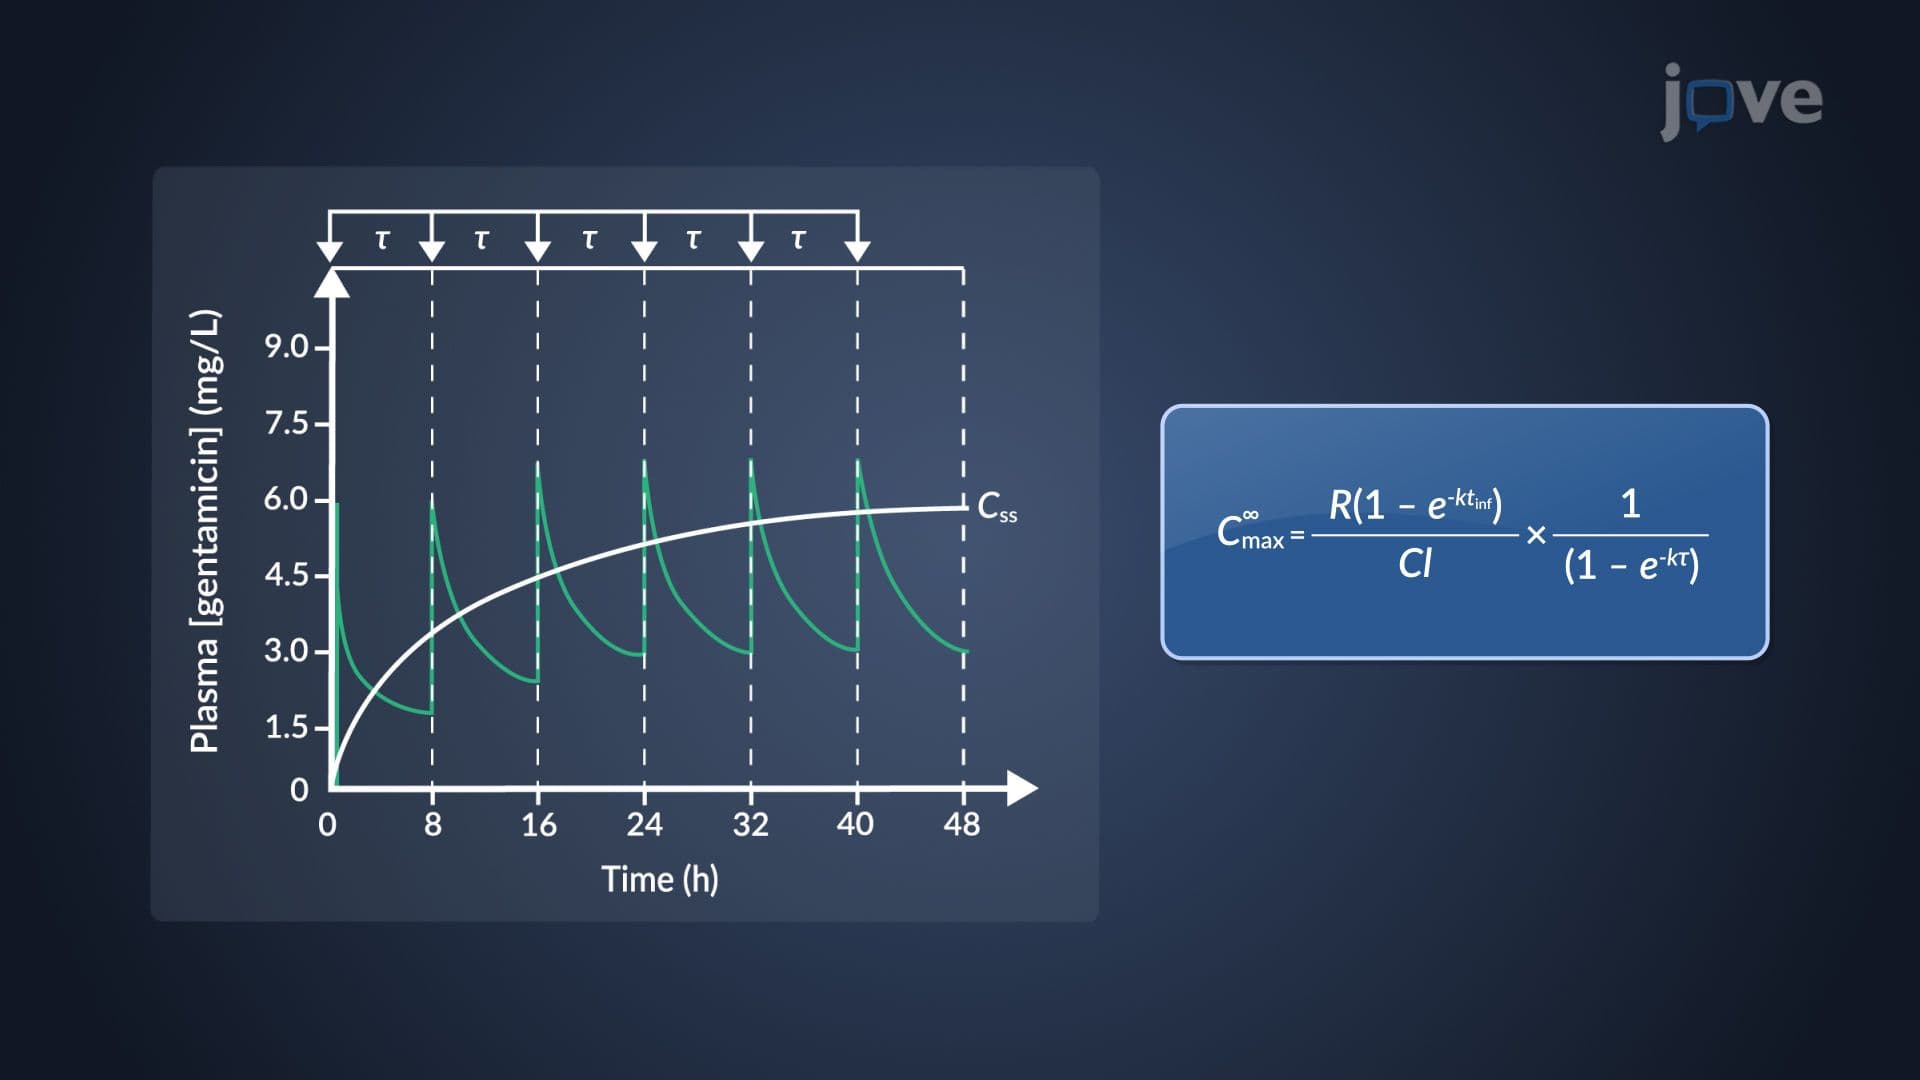
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations