Related Experiment Video
Updated: May 14, 2026
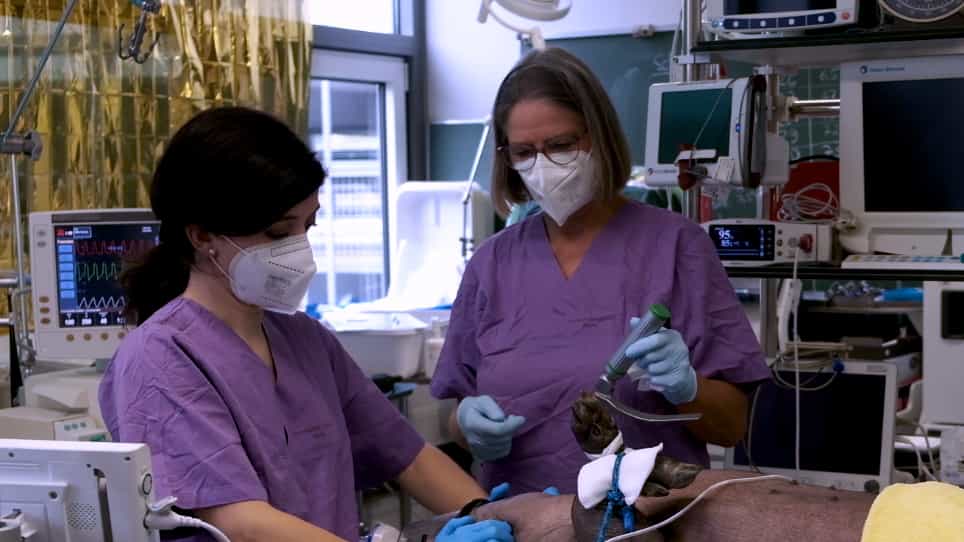

Endotracheal Intubation Using a Flexible Intubation Endoscope as a Standardized Model for Safe Airway Management in Swine
Published on: August 25, 2022
Association between length of intubation and subglottic stenosis in children
Denise Manica1, Cláudia Schweiger, Paulo José Cauduro Maróstica
1Otolaryngology Department, Hospital de Clínicas de Porto Alegre, Rio Grande do Sul, Brazil. denisemanica@gmail.com.

Insights
Longer intubation and increased sedation in children undergoing mechanical ventilation are linked to a higher risk of developing subglottic stenosis (SGS). This study highlights key factors contributing to airway injury in pediatric intensive care.
Area of Science:
- Pediatric critical care medicine
- Otolaryngology
- Respiratory medicine
Background:
- Endotracheal intubation is a common procedure in pediatric intensive care units (PICUs).
- Laryngeal lesions, including subglottic stenosis (SGS), are potential complications of endotracheal intubation in children.
- Understanding risk factors is crucial for preventing airway morbidity.
Purpose of the Study:
- To investigate the association between endotracheal intubation duration and other risk factors with laryngeal lesions in children.
- To determine the incidence of subglottic stenosis (SGS) in this pediatric population.
- To identify modifiable factors that may reduce the risk of SGS.
Main Methods:
- Prospective study involving children aged 0 to <5 years requiring endotracheal intubation for over 24 hours.
- Flexible fiber-optic laryngoscopy (FFL) performed post-extubation, with repeat FFL or laryngoscopy under general anesthesia if lesions persisted or symptoms developed.
- Multivariate analysis to assess the impact of intubation length and sedation doses on SGS development.
Main Results:
- 142 children were analyzed; 40.8% presented moderate to severe laryngeal lesions on initial FFL.
- The incidence of subglottic stenosis (SGS) was 11.3% (95% CI, 7.1-17.5).
- Each additional 5 days of intubation increased SGS risk by 50.3%; each additional sedation dose per day increased risk by 12%.
Conclusions:
- This study reports a higher incidence of SGS in children compared to previous research.
- The duration of endotracheal intubation and the number of sedation doses are significant risk factors for SGS development.
- Findings emphasize the importance of minimizing intubation time and sedation in pediatric patients to prevent airway complications.
Objectives/Hypothesis:
To investigate the role of the length of intubation and other risk factors in the development of laryngeal lesions in children undergoing endotracheal intubation in an intensive care unit and to determine the incidence of subglottic stenosis (SGS).
Study Design:
Prospective study.
Methods:
Children aged from birth to <5 years admitted to the Pediatric Intensive Care Unit of Hospital de Clinicas de Porto Alegre who required endotracheal intubation for more than 24 hours were eligible. Children underwent flexible fiber-optic laryngoscopy (FFL) after extubation. Those who presented moderate to severe abnormalities in this first examination underwent another FFL between 7 and 10 days. If lesions persisted or symptoms developed, regardless of initial findings, laryngoscopy under general anesthesia was performed.
Results:
We followed 142 children. In the first FFL, 58 children (40.8%) had moderate to severe laryngeal lesions. During follow-up, 16 children developed SGS, representing an incidence of 11.3% (95% confidence interval, 7.1-17.5). Multivariate analysis showed that for every 5 additional days of intubation, there was a 50.3% increase in the risk of developing SGS, and for each additional sedation doses/day, there was a 12% increase in the same outcome.
Conclusions:
In this first prospective research protocol in children, we found a higher incidence of SGS than in most previous studies. The length of intubation and the need for additional sedation doses appear to be key factors for the development of SGS during endotracheal intubation.

Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques