Related Experiment Video
Updated: May 7, 2026
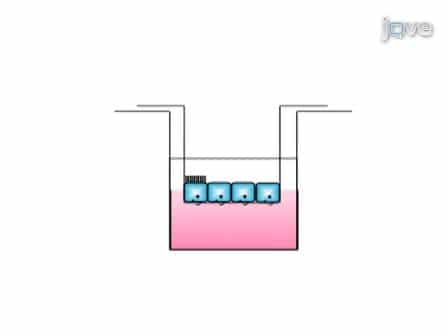
Isolation of Mouse Respiratory Epithelial Cells and Exposure to Experimental Cigarette Smoke at Air Liquid Interface
Published on: February 22, 2011
Effect of montelukast for treatment of asthma in cigarette smokers
David Price1, Todor A Popov, Leif Bjermer
1Centre of Academic Primary Care, University of Aberdeen, Aberdeen, United Kingdom. david@respiratoryresearch.org

Objective:
Many asthmatic patients are unable to quit cigarettes; therefore information is needed on treatment options for smokers. This study evaluates 10 mg/d montelukast and 250 μg of fluticasone propionate twice daily, each compared with placebo, in patients with self-reported active smoking (unable to quit) and asthma.
Methods:
Patients (ages 18-55 years, with asthma [≥1 year], FEV1 of 60% to 90% of predicted value, airway reversibility [≥12%], and self-reported active smoking [≥0.5 to ≤2 packs per day]) were randomized (after a 3-week, single-blind, placebo, run-in period) to 1 of 3 parallel, 6-month, double-blind treatment arms. The primary efficacy end point was the percentage of days with asthma control during treatment. Adverse experiences (AEs) were also evaluated.
Results:
There were 347, 336, and 336 patients randomized to montelukast, fluticasone, and placebo, respectively. The mean percentage of days with asthma control over 6 months of treatment was 45% (montelukast, P < .05 vs placebo), 49% (fluticasone, P < .001 vs placebo), and 39% (placebo); the difference between montelukast and fluticasone was not significant (P = .14). Patients with a smoking history of ≤11 pack years (the median value) tended to show more benefit with fluticasone, whereas those with a smoking history of >11 pack years tended to show more benefit with montelukast. AEs occurred in similar proportions among treatment groups.
Conclusions:
In a population of asthmatic patients actively smoking cigarettes, both 10 mg/d montelukast and 250 μg of fluticasone propionate twice daily significantly increased the mean percentage of days with asthma control compared with placebo.
Related Concept Videos
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:24
Antiasthma Drugs: Methylxanthines
Theophylline is thought to inhibit phosphodiesterase enzymes, increasing intracellular levels of cyclic adenosine monophosphate (cAMP) and cyclic guanosine monophosphate (cGMP). This rise in cAMP and cGMP concentrations stimulates cardiac function,...
 01:19
Antiasthma Drugs: Leukotriene Modifiers
Leukotriene modifiers work through two distinct mechanisms:
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:13
Asthma III: Clinical Manifestations