Related Experiment Video
Updated: May 14, 2026
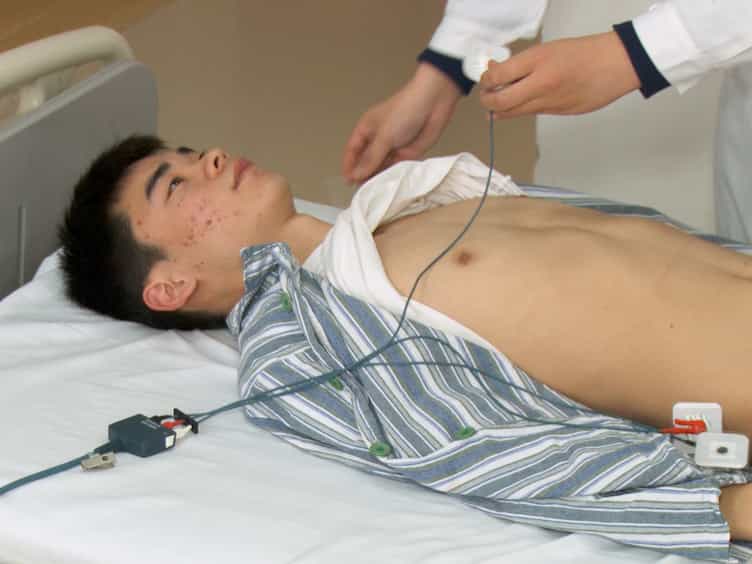

Measuring the Carotid to Femoral Pulse Wave Velocity (Cf-PWV) to Evaluate Arterial Stiffness
Published on: May 3, 2018
Subclinical arterial stiffness in young children after Kawasaki disease
Masato Oguri1, Tsuneyuki Nakamura1, Keita Tamanuki1
11 Department of Pediatrics, Kanazawa Medical University, Ishikawa, Japan.

Insights
Children with Kawasaki disease show early arterial stiffness. Ultrasound speckle tracking reveals measurable changes in arterial wall function shortly after illness onset, indicating potential long-term cardiovascular risk.
Area of Science:
- Cardiovascular Research
- Pediatric Cardiology
- Medical Imaging
Background:
- Kawasaki disease (KD) is linked to accelerated atherosclerosis in young adults.
- The timing of measurable arterial changes post-KD remains unclear.
- Subclinical arterial stiffness in young KD patients requires investigation.
Purpose of the Study:
- To evaluate subclinical arterial stiffness in young children with a history of Kawasaki disease.
- To identify early arterial changes using two-dimensional ultrasound speckle tracking.
- To compare arterial stiffness parameters between KD patients and healthy controls.
Main Methods:
- Seventy-five children with KD (mean age 8.2 years) and 50 controls (mean age 8.3 years) were studied.
- Two-dimensional ultrasound speckle tracking assessed carotid arterial walls.
- Measured parameters included peak systolic strain, strain rate, and conventional stiffness indices.
Main Results:
- Patients with KD exhibited significantly lower peak systolic strain (6.69% vs 8.60%) and late systolic strain rate (-0.28/s vs -0.51/s) compared to controls.
- No significant differences were found in time to peak systolic strain, early systolic strain rate, or conventional stiffness measures.
- These findings suggest altered arterial mechanics in KD patients.
Conclusions:
- Arterial walls in children with a history of Kawasaki disease show mild sclerotic changes.
- These changes are detectable shortly after the onset of the disease.
- Early detection of arterial stiffness may aid in risk stratification and management.
Background:
Recent studies have revealed that atherosclerosis progresses faster than expected in young adults with a history of Kawasaki disease. However, it is unclear as to when these arterial changes become measurable. In this study, we evaluated subclinical arterial stiffness in young children with a history of Kawasaki disease using two-dimensional ultrasound speckle tracking.
Methods:
A total of 75 children with a history of Kawasaki disease (mean age, 8.2 ± 2.8 years) and 50 healthy controls (mean age 8.3 ± 3.5 years) were included. The two regions of interest for speckle tracking were manually positioned at the anterior and posterior carotid arterial wall using a Philips iE33 (Philips Medical Systems, Bothell, WA, USA). The peak systolic strain, time to peak systolic strain, early systolic strain rate, and late systolic strain rate were continuously monitored between the two regions of interest. Furthermore, the intimal-medial thickness, stiffness β, and pressure-elastic modulus, as conventional measures of arterial stiffness, were concurrently obtained.
Results:
The peak systolic strain and late systolic strain rate differed significantly between the patients with Kawasaki disease and controls (6.69% versus 8.60%, p < 0.01, and -0.28/second versus -0.51/second, p < 0.0001, respectively). There was no difference in the time to peak systolic strain, early systolic strain rate, and conventional measures.
Conclusions:
The arteries of patients with Kawasaki disease appear to develop mild sclerotic changes shortly after the onset of the disease.

Related Concept Videos
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:23
Rheumatic Heart Disease I: Introduction
 01:27
Atherosclerosis II: Clinical Manifestations and Diagnostic Tests
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:21
Rheumatic Heart Disease III: Medical Management