Related Experiment Video
Updated: May 14, 2026

Subcutaneous Infection of Methicillin Resistant Staphylococcus Aureus (MRSA)
Published on: February 9, 2011
Methicillin-resistant Staphylococcus aureus colonization is not associated with higher rate of admission to pediatric
Mohammed Naeem1, Esam Al Banyan, Sardar Tanvir Sindhu
1Deparment of Peds, Division PICU, King Abdulaziz Medical City, Riyadh, Saudi Arabia. naeemm.mdpicu@yahoo.com

Purposes:
Methicillin-resistant Staphylococcus aureus (MRSA) colonization is consistently rising. The question whether the MRSA colonization places the patients at higher risk, requiring higher levels of care when being admitted, has never been studied. We conducted this study to determine the impact of MRSA colonization status on the required level of care upon admission to hospital.
Basic Procedures:
We conducted a retrospective chart review in 1000 plus-bed tertiary care academic institute. Our study population composed of all the patients who were admitted from January 2011 to March 2011. We found 7413 pediatric admissions that were identified as the study subjects. We assessed and divided study subjects into 2 groups, MRSA colonized and MRSA noncolonized. Methicillin-resistant Staphylococcus aureus-colonized patients were further grouped into those admitted to either pediatric intensive care unit (PICU) or ward, and these 2 groups were analyzed using P value, Fisher exact test, relative risks, and odds ratios.
Main Findings:
We found a total of 7413 admissions, 753 were admitted in PICU (average pediatric risk of mortality score 18), and 6660 were admitted in pediatric wards (average pediatric risk of mortality score, 5). We found that MRSA colonization was 20 (2.66%) of 753 in PICU admissions and 155 (2.33%) of 6660 in ward admissions. We found that rate of admissions difference between MRSA colonized and MRSA noncolonized groups was clinically insignificant (P > .05).
Principal Conclusions:
We conclude that MRSA colonization does not increase the need of care in PICU upon admission to hospital from emergency department. However, these preliminary results need to be confirmed through larger, multicenter, and multicountry data analysis.
Insights
Methicillin-resistant Staphylococcus aureus (MRSA) colonization does not significantly impact the level of care needed upon hospital admission. This study found no significant difference in intensive care unit admissions between colonized and non-colonized patients.
Area of Science:
- Infectious Diseases
- Clinical Medicine
- Epidemiology
Background:
- Rising rates of Methicillin-resistant Staphylococcus aureus (MRSA) colonization present a growing public health concern.
- The clinical significance of MRSA colonization on patient care requirements upon hospital admission remains understudied.
- Understanding this relationship is crucial for optimizing resource allocation and patient management strategies.
Purpose of the Study:
- To investigate the impact of Methicillin-resistant Staphylococcus aureus (MRSA) colonization status on the level of care required upon hospital admission.
- To determine if MRSA colonization necessitates higher levels of care, such as admission to a pediatric intensive care unit (PICU).
Main Methods:
- A retrospective chart review was conducted at a large tertiary care academic institute.
- 7413 pediatric admissions from January to March 2011 were analyzed, divided into MRSA-colonized and non-colonized groups.
- Statistical analyses included P values, Fisher exact test, relative risks, and odds ratios to compare admission locations (PICU vs. ward).
Main Results:
- MRSA colonization rates were 2.66% in PICU admissions (20/753) and 2.33% in ward admissions (155/6660).
- The difference in admission rates between MRSA-colonized and non-colonized groups was not statistically significant (P > .05).
- The average Pediatric Risk of Mortality (PRISM) scores were 18 for PICU admissions and 5 for ward admissions.
Conclusions:
- MRSA colonization does not appear to increase the need for intensive care upon hospital admission from the emergency department.
- These findings suggest that current admission protocols may not need adjustment based solely on MRSA colonization status.
- Further validation through larger, multicenter, and international studies is recommended to confirm these preliminary results.

Related Concept Videos
 01:25
Clinical Significance of Antibiotic Resistance
 01:29
Staphylococcal Skin Infections
 01:25
Mechanism of Antibiotic Resistance in MRSA
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:29
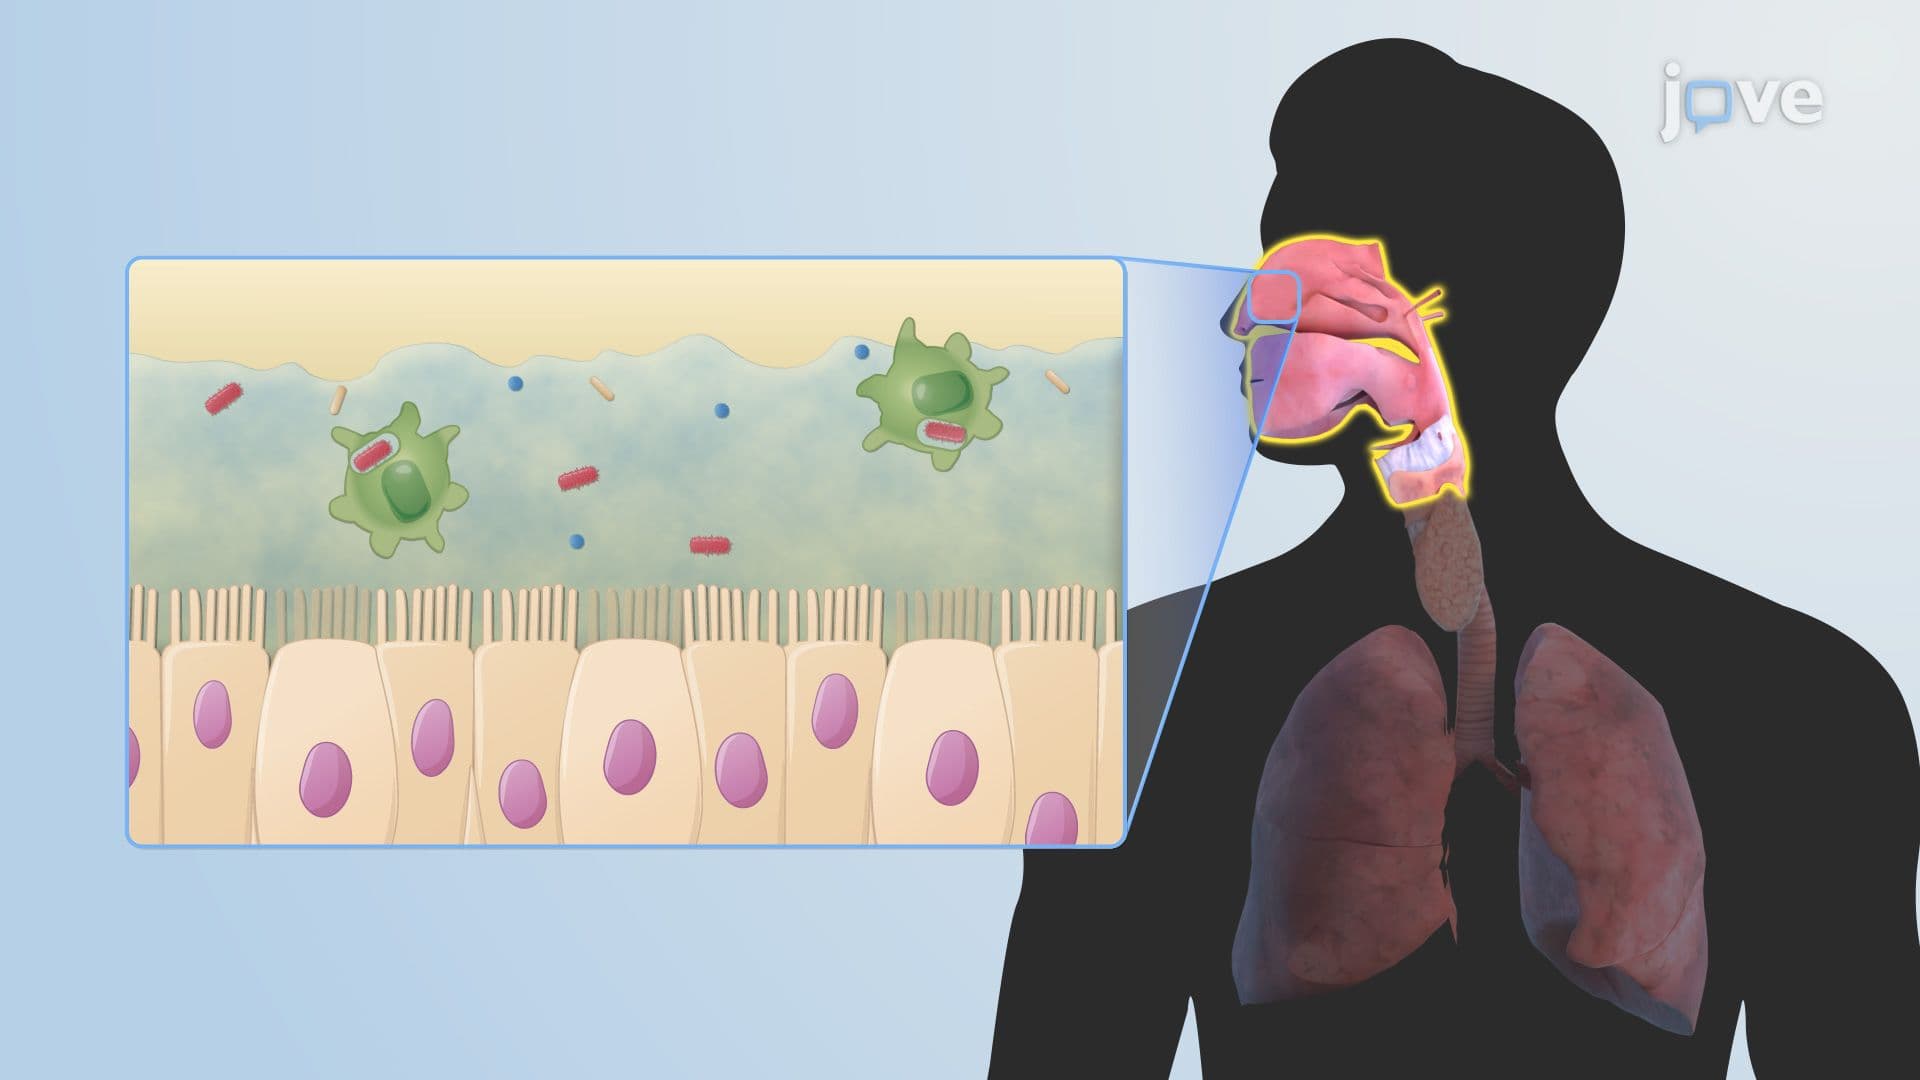
Microbiota of the Respiratory Tract
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies. Common...