Related Experiment Video
Updated: May 14, 2026
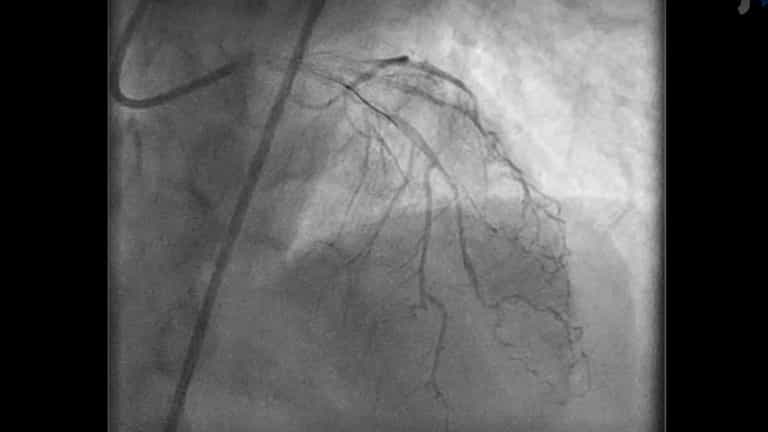

Acetylcholine Re-Challenge After Intracoronary Nitroglycerine Administration
Published on: April 4, 2022
Calcium antagonists in the treatment of coronary artery disease
Rhonda M Cooper-DeHoff1, Shin-Wen Chang, Carl J Pepine
1Department of Pharmacotherapy and Translational Research, College of Pharmacy, University of Florida, PO Box 100486, 1600 SW Archer Road, Gainesville, FL 32610-0486, USA.

Insights
Long-acting calcium antagonists (CAs) are safe and effective for treating coronary artery disease (CAD). These drugs offer cardiovascular benefits or equivalence, making them a potential first-line option for managing CAD.
Area of Science:
- Cardiology
- Pharmacology
Background:
- Calcium antagonists (CAs) use in coronary artery disease (CAD) was historically limited by adverse events from short-acting formulations.
- Recent evidence challenges these limitations, prompting a re-evaluation of CA efficacy and safety.
Purpose of the Study:
- To evaluate the current role and safety of calcium antagonists in managing coronary artery disease.
- To assess the cardiovascular outcomes associated with long-acting CA formulations.
Main Methods:
- Review of large-scale randomized clinical trials and meta-analyses on calcium antagonist use in CAD.
- Analysis of cardiovascular outcomes comparing long-acting CAs with other therapeutic agents.
Main Results:
- Long-acting CAs demonstrate safety and efficacy in patients with or at risk for CAD.
- These agents show benefit or equivalence in cardiovascular outcomes compared to other treatments.
- CAs are metabolically neutral and well-tolerated, with pleiotropic effects beneficial for risk management.
Conclusions:
- Long-acting calcium antagonists are a safe and effective treatment option for coronary artery disease.
- Their favorable profile supports consideration as a first-line therapy for CAD management.
- CAs can be used alone or in combination with other agents for comprehensive cardiovascular risk reduction.
Abstract:
The role of calcium antagonists (CA) in coronary artery disease (CAD) treatment was previously limited due to increased adverse cardiovascular events associated with rapid release, short-acting CAs. However, many large scale randomized clinical trials as well as meta-analyses have confirmed safety of long-acting CAs and documented either benefit or equivalence regarding cardiovascular outcomes versus the comparator agents in patients with or at risk for CAD. Furthermore, CAs are metabolically neutral, well tolerated, and poses pleiotropic effects that could work alone or in combination with other risk factor modifying agents for beneficial overall risk management. Therefore, CAs may be ideal for managing CAD and may be considered as a first-line treatment option, depending on individual patient characteristics.
Related Concept Videos
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...
 01:18
Antihypertensive Drugs: Action of Calcium Channel Blockers
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:20
Antiarrhythmic Drugs: Class IV Agents as Calcium Channel Blockers
Verapamil, a calcium channel blocker, inhibits calcium movement across myocardial cell membranes and vascular smooth muscle. This results in the dilation of coronary and...
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow. Administered...