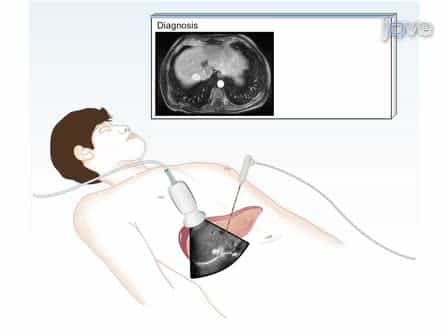
Related Experiment Video
Updated: May 14, 2026

Application of Laparoscopic Hepatectomy Combined with Intraoperative Microwave Ablation in Colorectal Cancer Liver Metastasis
Published on: March 3, 2023
Operative microwave ablation for hepatocellular carcinoma: complications, recurrence, and long-term outcomes
Ryan Z Swan1, David Sindram, John B Martinie
1Hepato-Pancreato-Biliary Surgery, Department of General Surgery, Carolinas Medical Center, 1025 Morehead Medical Drive, Suite 300, Charlotte, NC 28204, USA.

Background:
Treatment of hepatocellular carcinoma (HCC) in the setting of cirrhosis is limited by tumor size/location and underlying liver disease. Radiofrequency ablation is utilized in selected patients; however, local recurrence remains a concern. Microwave ablation (MWA) delivers energy to tissue in a unique fashion, reducing local recurrence. A minimally invasive operative approach allows for mobilization/protection of adjacent structures, intra-operative ultrasound, and assessment of ablation progress.
Study Design:
Retrospective review of operative MWA performed for HCC in patients with cirrhosis over a 4-year period at a single center. Complications were stratified by Clavien-Dindo classification. Incomplete ablation and local, regional, and metastatic recurrence was assessed on follow-up imaging. Survival was assessed in months.
Results:
Fifty-four patients with 73 tumors underwent MWA. Median tumor size was 2.6 cm (range 0.5-8.5 cm). Cirrhosis was present in 92.6 % of patients, with a Child-Pugh score of B/C in 27.8 % and hepatitis C present in 59.3 %. A minimally invasive approach was used in 94.5 % of patients. There were no deaths within 30 days. Thirty-day morbidity was 28.9 %, with grade III complications present in 11.5 %. Delayed complications occurred in 7.8 % of patients, with a 5.6 % 90-day mortality. Incomplete ablation was identified in 5.9 % of tumors with local recurrence of 2.9 % at 9 months median follow-up. Regional and metastatic recurrence occurred in 27.5 and 11.8 % at 9 months median follow-up. Median survival was not reached at 11 months median follow-up. One- and 2-year survival was 72.3 and 58.8 %.
Conclusion:
Operative, preferably minimally invasive, MWA can be performed in cirrhotic patients with HCC with acceptable morbidity and low recurrence rates. High regional and metastatic recurrence rates in these patients underscore the need for minimally invasive, low morbidity approaches to liver-directed therapy.