Related Experiment Video
Updated: May 14, 2026
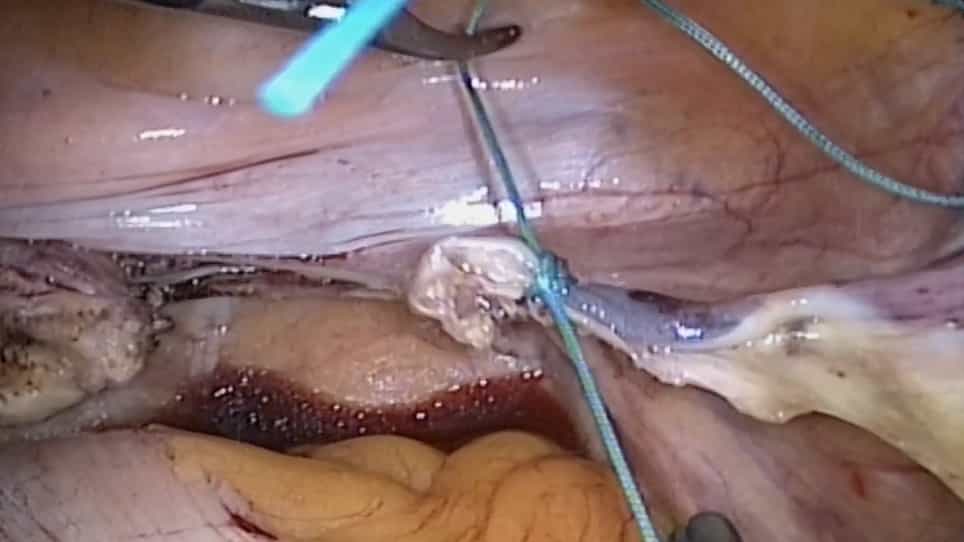

Laparoscopic Non-Mesh Cerclage Pectopexy for Pelvic Organ Prolapse
Published on: September 13, 2022
Laparoscopic ventral rectopexy for rectal prolapse and symptomatic rectocele: an analysis of 245 consecutive patients
H A Formijne Jonkers1, N Poierrié, W A Draaisma
1Department of Surgery, Meander Medical Centre, Amersfoort, the Netherlands.

Aim:
This retrospective study aimed to determine functional results of laparoscopic ventral rectopexy (LVR) for rectal prolapse (RP) and symptomatic rectoceles in a large cohort of patients.
Method:
All patients treated between 2004 and 2011 were identified. Relevant patient characteristics were gathered. A questionnaire concerning disease-related symptoms as well as the Cleveland Clinic Incontinence Score (CCIS) and Cleveland Clinic Constipation Score (CCCS) was sent to all patients.
Results:
A total of 245 patients underwent operation. Twelve patients (5%) died during follow-up and were excluded. The remaining patients (224 women, nine men) were sent a questionnaire. Indications for LVR were external RP (n = 36), internal RP or symptomatic rectocele (n = 157) or a combination of symptomatic rectocele and enterocele (n = 40). Mean age and follow-up were 62 years (range 22-89) and 30 months (range 5-83), respectively. Response rate was 64% (150 patients). The complication rate was 4.6% (11 complications). A significant reduction in symptoms of constipation or obstructed defaecation syndrome was reported (53% of patients before vs 19% after surgery, P < 0.001). Mean CCCS during follow-up was 8.1 points (range 0-23, SD ± 4.3). Incontinence was reported in 138 (59%) of the patients before surgery and in 32 (14%) of the patients after surgery, indicating a significant reduction (P < 0.001). Mean CCIS was 6.7 (range 0-19, SD ± 5.2) after surgery.
Conclusion:
A significant reduction of incontinence and constipation or obstructed defaecation syndrome after LVR was observed in this large retrospective study. LVR therefore appears a suitable treatment for RP and rectocele with and without associated enterocele.

