Related Experiment Video
Updated: May 14, 2026


Rodent Model of Masseter Volumetric Muscle Loss for Studying Bioengineering Materials
Published on: May 31, 2024
Comparison of three techniques of reduction malarplasty in zygomaticus and massateric biomechanical changes and
Yuguang Zhang1, Mengyao Tang, Rong Jin
1From the Department of Plastic and Reconstructive Surgery, Shanghai Ninth People's Hospital affiliated to Medical School of Shanghai Jiao Tong University, Shanghai, People's Republic of China.

Background:
For Asians, prominent zygomatic region is a sign of masculinity; therefore, reduction malarplasty is becoming more and more popular in Asian women.
Objective:
The purpose of this study is to analyze the biomechanical changes of zygomaticus and masseter, and to explore the underlying causes of relevant complications using the 3 popular techniques of reduction malarplasty.
Methods:
From May 2000 to August 2009, 259 female patients underwent traditional osteotomy through coronary incision, malomaxillary suture with L-shaped osteotomy through intraoral approach, and the modified X.M.'s technique. The mechanical and anatomical causes of the relevant complications such as facial asymmetry caused by detachment of zygomaticus and masseter, facial sagging, and downward movement of malar point in 3 surgical procedures were analyzed and compared postoperatively among the 3 procedures.
Results:
In the traditional osteotomy through coronary incision, the inside cheek fat pad moved interoinferiorly because the greater and lesser zygomatic muscles were stripped from the attachment points, whereas masseter was relatively less stripped from its attachment point, which affects mechanical direction and contraction strength less, which possibly leads to the downward movement of the fractured extremity of zygomatic bone. In the L-shaped osteotomy, the zygomatic arch slided interoinferiorly because of the operative design, and masseter's strong extroinferior traction often caused fixation loosening between the former and latter bone margin. As a result, the fractured zygomatic bone moved downward along with zygomaticus, masseter, and fat pad. In the modified X.M.'s technique, complications were relatively fewer, which may be related to less injury to the fixation system of zygomatic bone and less biomechanical changes in masseter and zygomatic muscles.
Conclusions:
Surgeons should base their choice of reduction malarplasty not only on thoroughness of the operation but also on biomechanical changes in the zygomatic region and patients' individual conditions.
More Related Videos
 06:26
Quantitative Assessment Protocol for Facial Soft Tissue Volumetric Changes with Stereophotogrammetry
Published on: December 9, 2025
 05:54
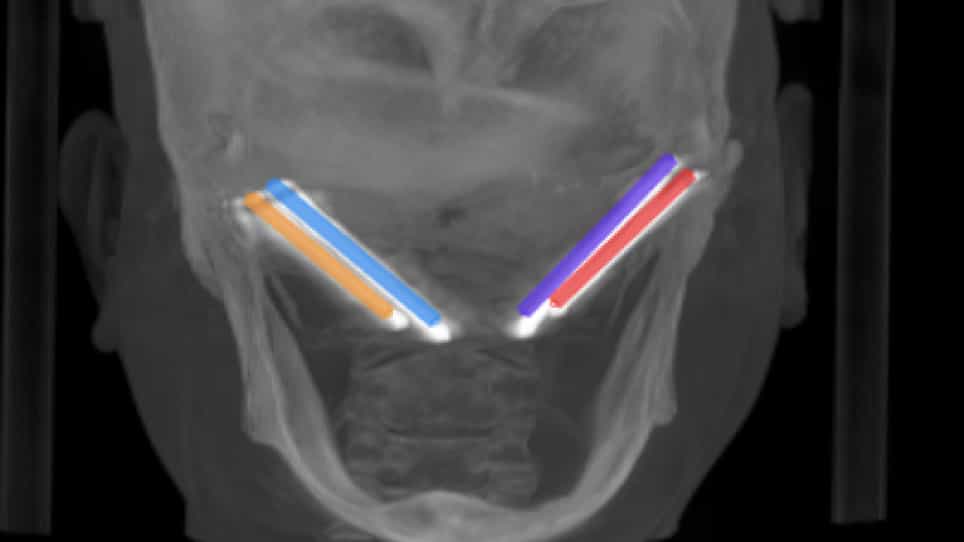
Real-Time Dynamic Navigation System for the Precise Quad-Zygomatic Implant Placement in a Patient with a Severely Atrophic Maxilla
Published on: October 18, 2021