Is it worth assessing progress as early as week 2 to adapt antidepressive treatment strategy? Results from a study on agomelatine and a global meta-analysis
Related Experiment Video
Updated: May 14, 2026
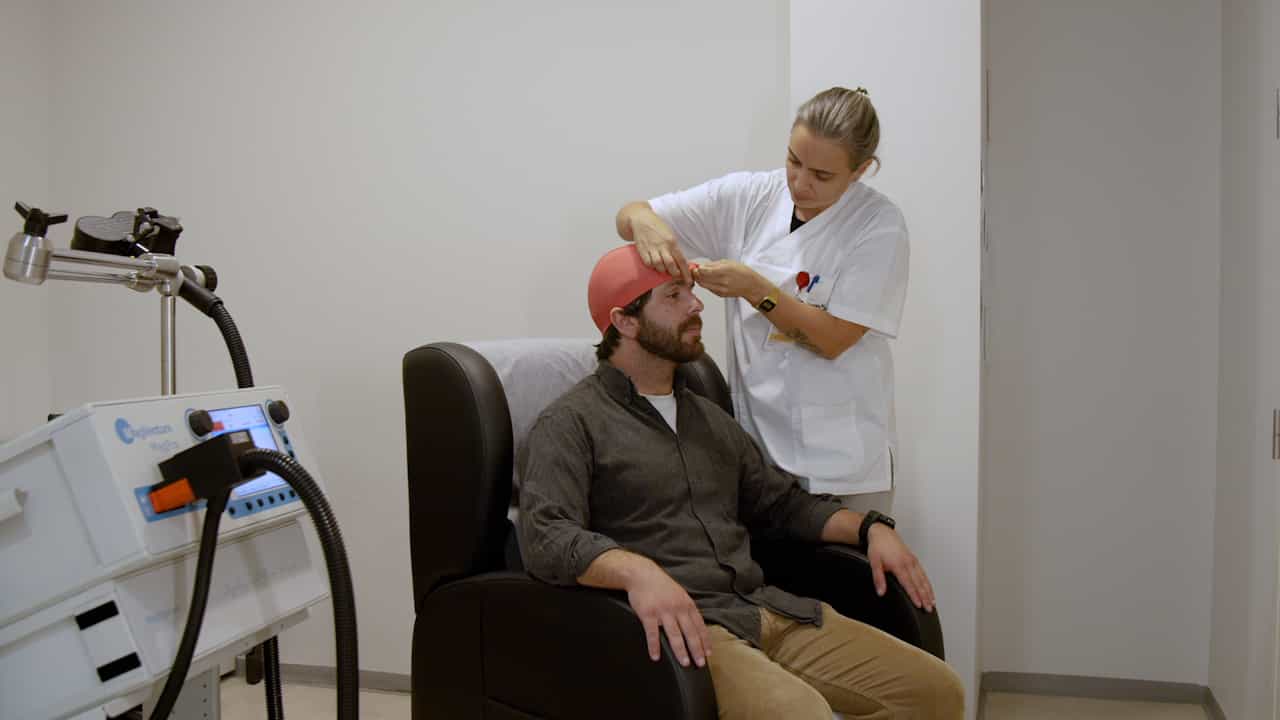
Conventional Repetitive Transcranial Magnetic Stimulation for Depression: A Step-by-Step Protocol
Published on: November 21, 2025
1Centre Hospitalier Sainte-Anne (CMME), 100, rue de la Santé, 75014 Paris, France. p.gorwood@ch-sainte-anne.fr

Context:
A delay of 4-8weeks before modifying the prescribed antidepressant treatment is usually proposed when incomplete treatment response is observed. A number of studies nevertheless proposed that the lack of early improvement (usually 20% decrease of severity at week 2) is predictive of the absence of subsequent treatment response, potentially saving weeks of inadequate treatment, but with no information for non-interventional studies devoted to outpatients.
Method:
Two thousand nine hundred and thirty-eight outpatients with major depressive disorder were included in a multicentre, non-interventional study, assessing at inclusion, week 2 and week 6, mood (QIDS-C, CGI, PGI and VAS) sleep (LSEQ) and functionality (SDS). All metrics at week 2 were tested for their capacity to predict response (and then remission) at week 6, all patients being treated by agomelatine. A meta-analysis of all studies (n=12) assessing the predictive role of improvement at week 2 was also performed, assessing specific effect size of published studies and the weight of the different parameters they used.
Results:
The QIDS-C and the CGI-I were the only instruments with an area under the curve over 0.7, with different cut-offs for treatment response and remission. A decrease of more than five points at the QIDS-C had the highest positive predictive value for treatment response, and a CGI-I over three had the highest negative predictive value, which would favour relying on the clinicians for warning (too high CGI-I), and on instruments for confidence (favourable decrease of the QIDS-C). The meta-analysis of all studies also detected a large effect size of early improvement, stressing how rating week 2 severity could be beneficial in clinical practice.
Conclusions:
Previous reports stressing the interest of an assessment at week 2 were reinforced by the present results, which also defined more accurately what could be the most appropriate cut-offs, and how combining these early results could be more effective.
Insights
Early assessment of antidepressant response in outpatients can predict treatment success. A two-week evaluation using the QIDS-C scale helps identify effective treatments sooner, avoiding prolonged inadequate therapy.
Area of Science:
- Psychiatry and Mental Health
- Clinical Pharmacology
- Treatment Efficacy Studies
Background:
- Standard practice suggests delaying antidepressant treatment changes for 4-8 weeks after incomplete response.
- Early improvement (e.g., 20% symptom decrease by week 2) may predict subsequent treatment success.
- Limited data exists on early response prediction in non-interventional outpatient studies.
Purpose of the Study:
- To evaluate the predictive value of early symptom improvement at week 2 for treatment response and remission at week 6 in major depressive disorder outpatients.
- To identify reliable clinical and self-assessment instruments for predicting antidepressant treatment outcomes.
- To synthesize evidence from existing studies through meta-analysis regarding early treatment response indicators.
Main Methods:
- A multicentre, non-interventional study involving 2938 outpatients with major depressive disorder treated with agomelatine.
- Assessment of mood (QIDS-C, CGI, PGI, VAS), sleep (LSEQ), and functionality (SDS) at baseline, week 2, and week 6.
- Statistical analysis of week 2 metrics to predict week 6 response/remission, alongside a meta-analysis of 12 prior studies.
Main Results:
- The QIDS-C (Quick Inventory of Depressive Symptomatology - Self Report) and CGI-I (Clinical Global Impression - Improvement) showed predictive accuracy (Area Under Curve > 0.7).
- A QIDS-C decrease >5 points strongly predicted treatment response; a CGI-I score >3 indicated a high likelihood of non-response.
- Meta-analysis confirmed a significant effect size for early improvement as a predictor of treatment outcome.
Conclusions:
- Findings support the utility of week 2 assessments for predicting antidepressant treatment outcomes in major depressive disorder.
- Specific cut-offs for QIDS-C and CGI-I at week 2 can enhance prediction accuracy.
- Combining early assessment data may optimize clinical decision-making regarding treatment adjustments.
Related Concept Videos
 01:23
Antidepressant Drugs: MAOIs and Other Agents
 01:25
Antidepressant Drugs: Overview
 01:26
Psychosis: Goals of Pharmacotherapy