Related Experiment Video
Updated: May 14, 2026
Auricular Acupressure as an Adjuvant Treatment for Wheezing in Stable Chronic Obstructive Pulmonary Disease
Published on: May 10, 2024
Reduced infant lung function, active smoking, and wheeze in 18-year-old individuals
David Mullane1, Steve W Turner, Des W Cox
1Department of Paediatrics and Child Health, University College Cork, Cork, Ireland.

Insights
Reduced infant lung function is linked to persistent wheeze in 18-year-olds. Other factors include infant atopy, maternal asthma, and smoking, offering insights into obstructive airways disease.
Area of Science:
- Pediatric respiratory health
- Pulmonary function development
- Epidemiology of wheeze and asthma
Background:
- Wheeze in childhood can persist into adulthood, impacting long-term respiratory health.
- Early life factors influencing the development of persistent wheeze require further investigation.
- Understanding the origins of obstructive airways disease in young adults is crucial for early intervention.
Purpose of the Study:
- To determine if reduced lung function in infancy predicts persistent wheeze at age 18.
- To identify other early-life factors associated with persistent wheeze in young adults.
Main Methods:
- A birth cohort study followed 150 individuals from 1 month to 18 years of age in Perth, Western Australia.
- Maximal flow at functional residual capacity (V'maxFRC) was measured in infants.
- Wheeze status was categorized based on reported symptoms, and smoking status was recorded at age 18.
Main Results:
- Reduced percentage of predicted V'maxFRC in infancy was independently associated with persistent wheeze at age 18 (43% mean reduction).
- Persistent wheeze was also linked to infant atopy (OR=7.1), maternal asthma (OR=6.8), and active smoking (OR=4.8).
- Reduced infant lung function was associated with wheeze at age 18 only among current smokers.
Conclusions:
- Persistent wheeze from childhood to young adulthood is associated with reduced infant lung function, atopy, maternal asthma, and smoking.
- Active smoking interacts with reduced infant lung function to increase the risk of wheeze at age 18.
- These findings provide critical insights into the developmental origins of obstructive airways disease.
Unlabelled:
IMPORTANCE This is the first study to link reduced lung function in early life, before the development of symptoms, to wheeze in 18-year-olds. Additionally, the study gives insight into factors other than reduced lung function that are also associated with persistent wheeze in young adults.
Objective:
To test the hypothesis that reduced lung function in early life is associated with increased risk for persistent wheeze at age 18 years.
Design:
Birth cohort study.
Setting:
Perth, Western Australia.
Participants:
Individuals followed up from age 1 month to 18 years.
Main Outcome Measures:
Maximal flow at functional residual capacity (V'maxFRC) was measured in 1-month-old infants who were followed up at ages 6, 12, and 18 years. Based on reported symptoms, individuals were categorized as having remittent wheeze, later-onset wheeze, persistent wheeze, and no wheeze. Smoking status was noted at age 18 years.
Results:
Of the 253 individuals originally recruited, 150 were followed up at age 18 years; 37 of the 150 had recent wheeze. Compared with the no-wheeze group (n = 96), persistent wheeze (n = 13) was independently associated with reduced percentage of predicted V'maxFRC (mean reduction, 43%; 95% CI, 13-74). Compared with the no-wheeze group, persistent wheeze was also associated with atopy in infancy (odds ratio = 7.1; 95% CI, 1.5-34.5), maternal asthma (odds ratio = 6.8; 95% CI, 1.4-32.3), and active smoking (odds ratio = 4.8; 95% CI, 1.0-21.3). When only wheeze at age 18 years was considered, reduced percentage of predicted V'maxFRC was associated with wheeze at age 18 years only among current smokers (P = .04).
Conclusions And Relevance:
Wheeze persisting from ages 6 to 18 years is associated with multiple factors, including reduced infant lung function, infant-onset atopy, maternal asthma, and active smoking. Wheeze at age 18 years (regardless of previous wheeze status) is associated with active smoking, but only among those with reduced lung function in infancy. These findings give unique insight into the cause of obstructive airways disease in 18-year-olds, and follow-up of this cohort might be expected to further extend our understanding.
Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:29
Asthma-I: Introduction
 01:23
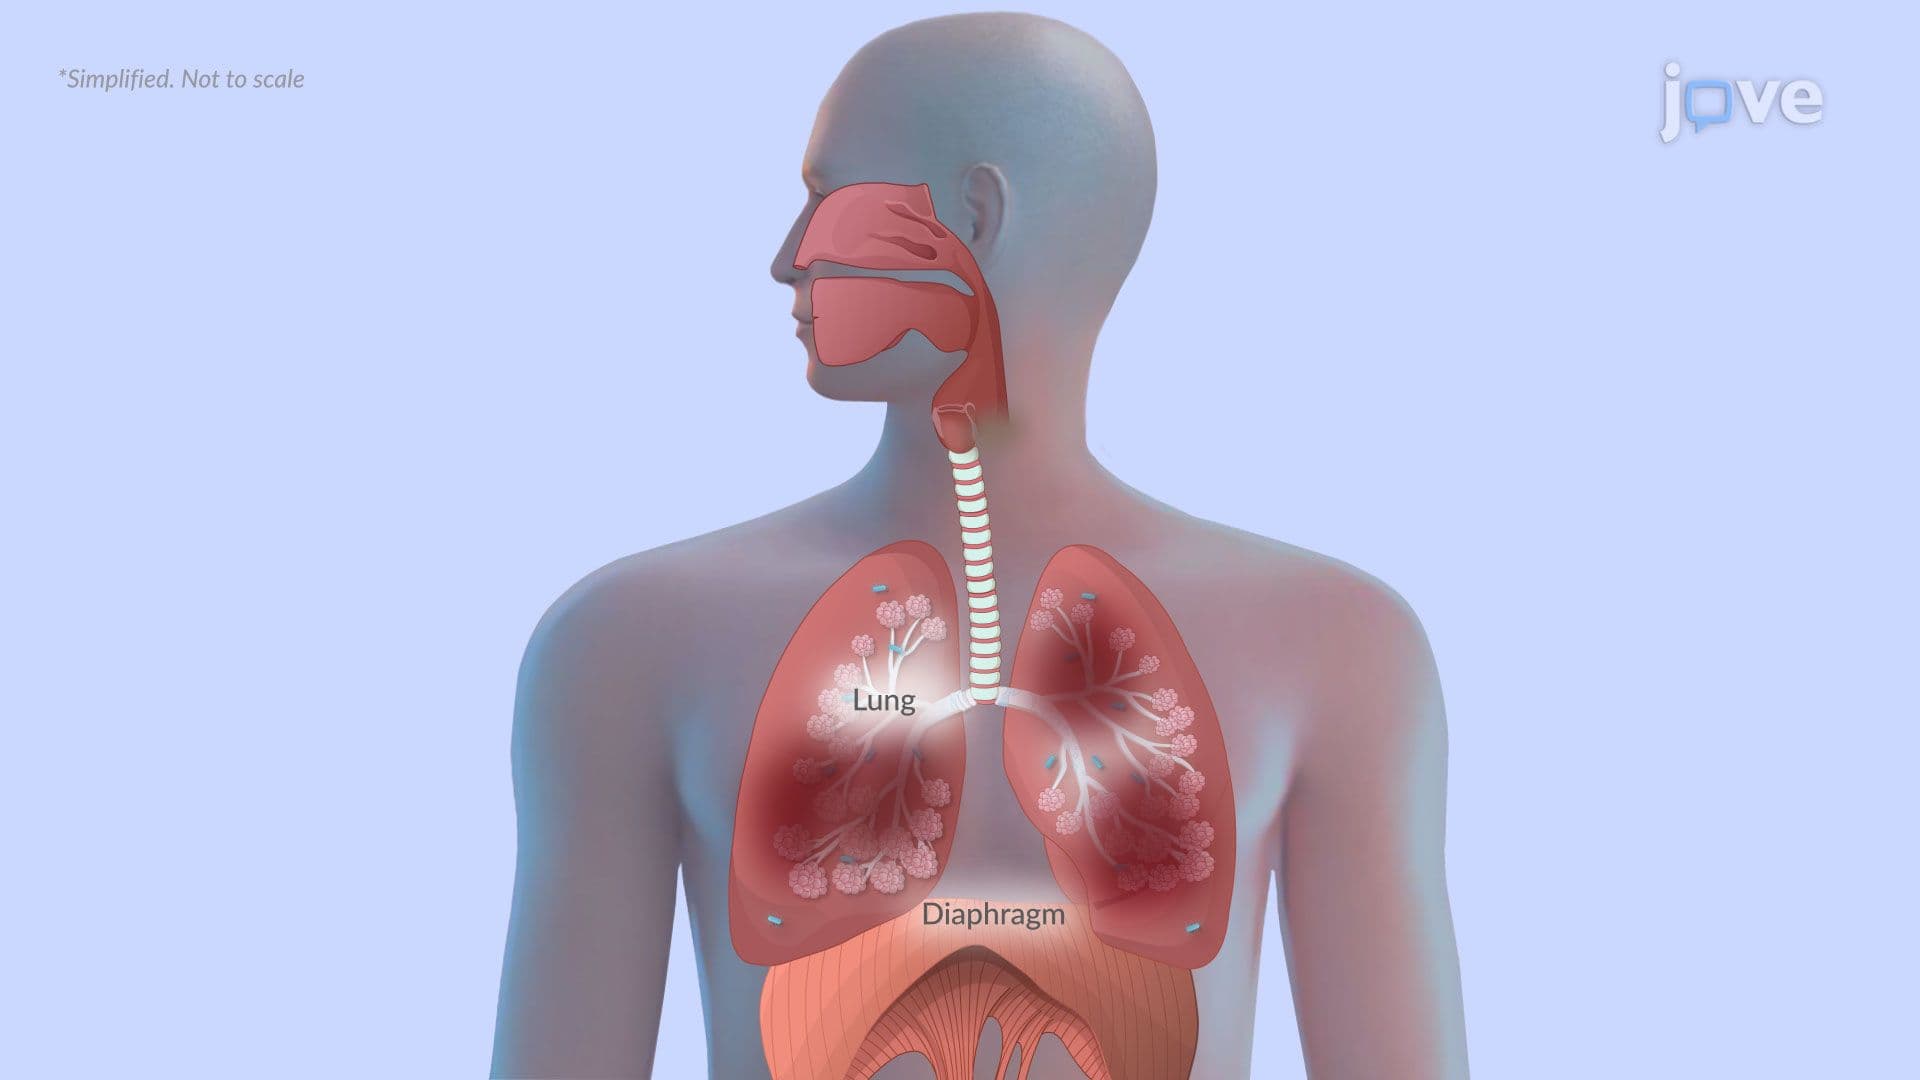
Chronic Obstructive Pulmonary Disease I: Introduction
 01:17
Pulmonary Cycle: Exhalation
 01:28
Asthma I: Introduction
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema