Pulmonary disability after severe blunt chest trauma
Related Experiment Video
Updated: Oct 5, 2026
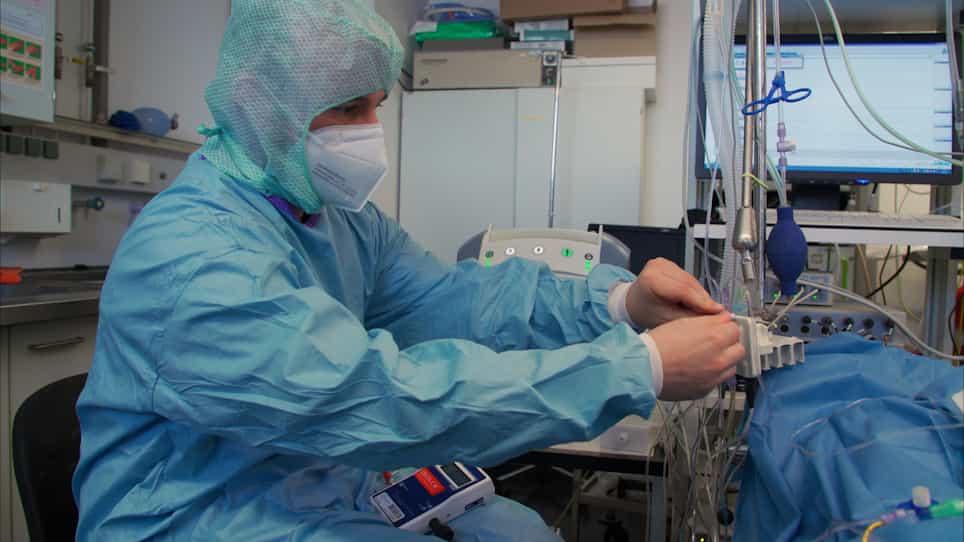
Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome (ARDS)
Published on: April 7, 2021
D H Livingston1, J D Richardson
1Department of Surgery, University of Louisville School of Medicine, Kentucky.

Abstract:
Twenty-eight patients surviving severe chest injury were studied prospectively (Group I) to assess the timing of recovery and the degree of residual pulmonary dysfunction. Pulmonary function tests (PFT) were obtained within 2 weeks of discharge and serially at intervals of 3 to 6 months. In addition, 16 patients injured 1 to 11 years previously (mean, 33 months) were recalled to determine long-term respiratory disability (Group II). Standard spirometric pulmonary function measurements were obtained. The mean age (36 yrs) and ISS (34) were the same in both groups. The majority of patients required intubation and mechanical ventilation, averaging 21 days in Group I and 18 days in Group II. PFTs were markedly abnormal soon after injury, averaging 40 to 50% of predicted values for all tests performed. Rapid improvement in all parameters was noted by 4 months after discharge and pulmonary function had almost returned to normal by the last followup exam (average, 65 to 90% of predicted). Results in Group II demonstrated continued improvement over long periods of followup. All patients who were employed preinjury had returned to work by 6 months after discharge except one. Long-term respiratory disability was present in less than 5% of patients studied. We conclude that recovery from severe chest injury occurs rapidly in most patients and serious long-term respiratory disability is uncommon. These results justify the commitment of major resources to the intensive care of patients with severe chest injuries.
Related Concept Videos
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:08
Pneumothorax II: Pathophysiology
 01:10
Atelectasis II: Pathophysiology