Laparoscopic rectopexy for rectal prolapse to reduce surgical-site infections and length of stay
Related Experiment Video
Updated: May 14, 2026
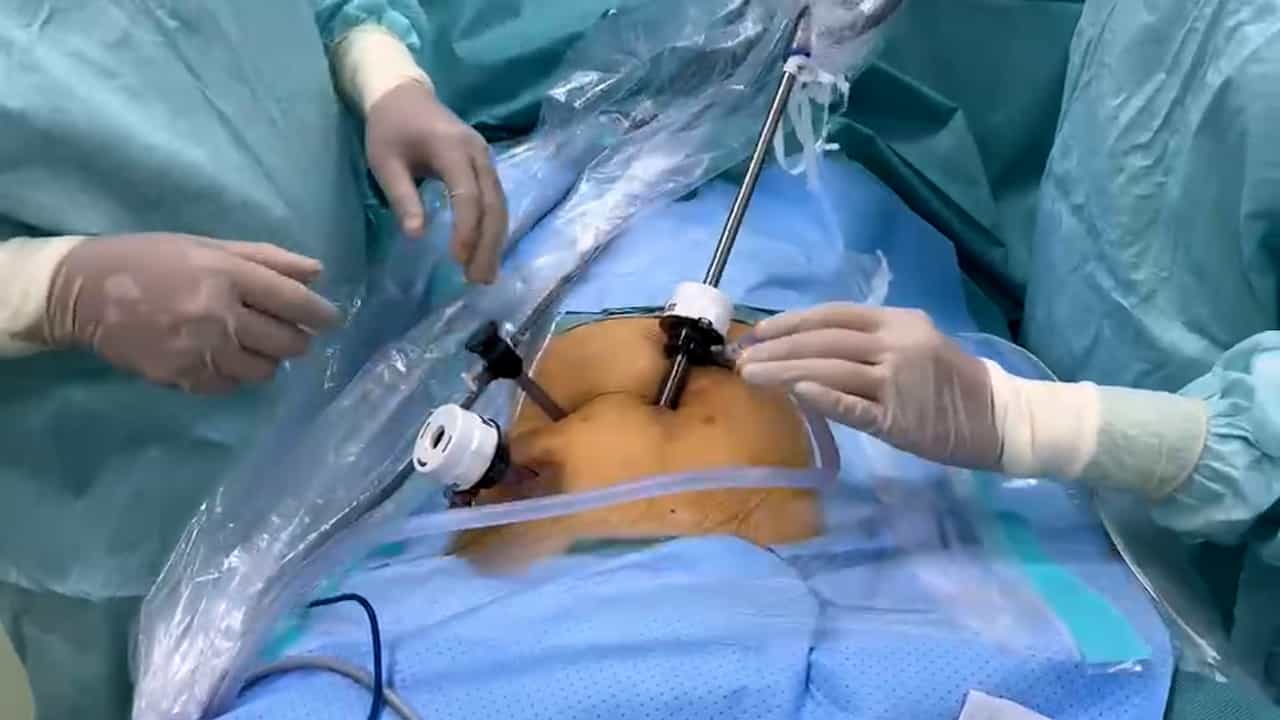
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
J Trent Magruder1, Jonathan E Efron, Elizabeth C Wick
1Colon and Rectal Division, Department of Surgery, The Johns Hopkins Hospital, 600 N. Wolfe Street, Baltimore, MD 21287, USA. jmagrud3@jhmi.edu

Background:
Rectal prolapse is commonly seen in patients with significant co-morbidities. Multiple approaches have been described, including the use of laparoscopy. The purpose of this study was to determine if laparoscopic approaches for repair of rectal prolapse are associated with less short-term morbidity than open approaches.
Methods:
The American College of Surgeons National Surgical Quality Improvement Program database was queried for patients who underwent laparoscopic or open rectopexy (R) or sigmoid resection and rectopexy (SR + R) between 2005 and 2008. Co-morbidities analyzed included diabetes, body mass index, chronic obstructive pulmonary disease, hypertension, cardiac (history of congestive heart failure, myocardial infarction, peripheral vascular disease, previous percutaneous cardiac intervention or surgery), and neurologic disorder (history of transient ischemic attack or cerebrovascular accident). Postoperative complications analyzed included surgical-site infections (SSIs), pneumonia, reintubation, pulmonary embolus, stroke, myocardial infarction, and sepsis. The χ (2) or t test/ANOVA were used to assess significance for categoric and continuous variables, respectively. Logistic regression analysis was used to determine risk factors for morbidity after rectal prolapse repair.
Results:
Altogether, 685 patients underwent surgical treatment of rectal prolapse. Most patients underwent open SR + R (open: 247 SR + R, 193 R; laparoscopic: 161 SR + R, 84 R). All patients had similar co-morbidity profiles. Patients undergoing laparoscopic R were significantly older (mean age 61.4 years) than those in the other three groups (p = 0.04). Operating time ranged from 128 min (open R) to 185 min (laparoscopic SR + R; p < 0.001). Open SR + R and open R were associated with significantly more morbidity than laparoscopic SR + R and R [odds ratio (OR) 0.42, 95 % confidence interval (CI) 0.22-0.83, p = 0.01]. Comparing all four procedures, there was a trend to decreased overall morbidity with laparoscopic R, but without statistical significance (OR 0.31, 95 % CI 0.07-1.40, p = 0.13). Length of hospital stay (LOS) and SSI rates were significantly lower with laparoscopic R than with the other three procedures.
Conclusions:
Patients who undergo laparoscopic rectopexy have a shorter LOS and lower SSI rate than patients who undergo other abdominal procedures for repair of rectal prolapse. Further study is necessary to determine the long-term outcomes from laparoscopic rectopexy, but in high-risk patients the laparoscopic approach can decrease perioperative risk.
Related Concept Videos
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: