Related Experiment Video
Updated: Aug 10, 2026
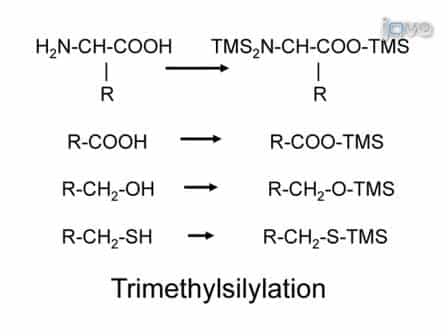

One-step Metabolomics: Carbohydrates, Organic and Amino Acids Quantified in a Single Procedure
Published on: June 25, 2010
Increased urinary metabolite excretion during fasting in disorders of propionate metabolism
1Nutrition Research Group, Clinical Research, Centre Harrow, United Kingdom.

Abstract:
Odd-chain fatty acids are recognized precursors of propionate in man, but their clinical significance in disorders of propionate metabolism has not been well studied. Urinary excretion of methylmalonate, methylcitrate, propionylglycine, and 3-hydroxypropionate was measured in five children with methylmalonic acidemia and three with propionic acidemia during frequent or continuous feeding and after 10-18 h of fasting. There was a significant (p less than 0.01) increase in the mean total measured metabolite excretion during fasting (fed 38.1 mumol/kg/h, fasting 54.6 in methylmalonic acidemia, fed 1.45, fasting 2.98 in propionic acidemia). Percentage rises in each subject were similar for all measured metabolites. These increases in metabolite excretion are most easily explained by mobilization and oxidation of odd-chain fatty acids in the fasting state. Prolonged fasting should be avoided in children with disorders of propionate metabolism.
More Related Videos
 11:06
Network Pharmacology Prediction and Metabolomics Validation of the Mechanism of Fructus Phyllanthi against Hyperlipidemia
Published on: April 7, 2023
 08:37
Assessment of Glutamine as a Fuel Source for Alveolar Macrophages Exposed to Chronic Ethanol Using an Extracellular Flux Bioanalyzer
Published on: November 15, 2024
Related Concept Videos
 01:21
Overview of Protein Metabolism
Amino acids play various roles in the body once they are absorbed into cells. They are restructured...
 01:24
Metabolic States of the Body: Fasting and Starvation
 01:22
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa
The pKa of a drug,...
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:14
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug