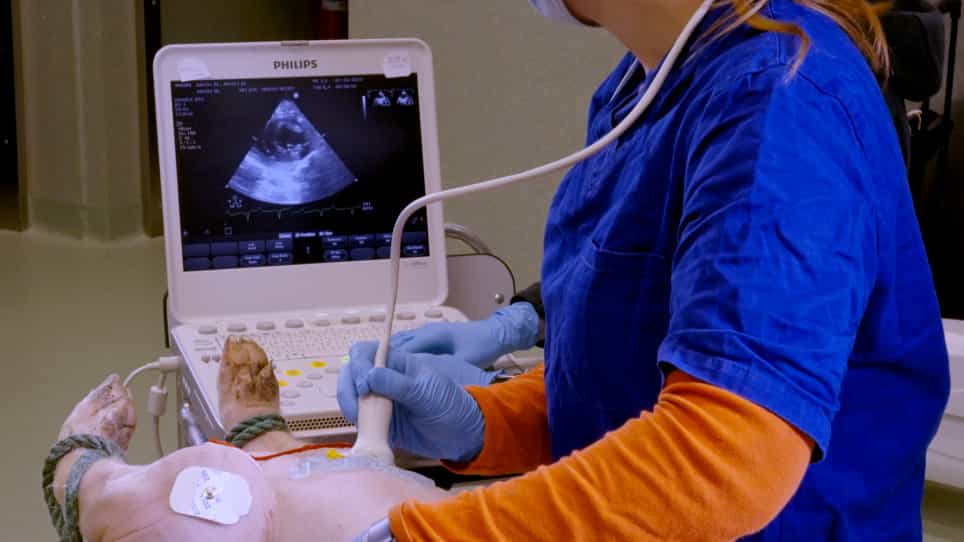
Corrected right ventricular end-diastolic volume and initial distribution volume of glucose correlate with cardiac
Junichi Saito1, Hironori Ishihara, Eiji Hashiba
1Department of Anesthesiology, Hirosaki University Graduate School of Medicine, 5 Zaifu-cho, Hirosaki, 036-8562, Japan. fix-you@hotmail.co.jp

Insights
Corrected right ventricular end-diastolic volume (cRVEDVI) and index of initial distribution volume of glucose (IDVGI) effectively correlate with cardiac index (CI) in cardiac surgery patients. These markers show potential for monitoring cardiac preload post-surgery, even with arrhythmias.
Area of Science:
- Cardiology
- Critical Care Medicine
- Cardiovascular Surgery
Background:
- Maintaining adequate cardiac output (CO) post-cardiac surgery relies on precise cardiac preload management.
- Cardiac index (CI) is a key indicator of hemodynamic stability.
- Arrhythmias can complicate the assessment of cardiac preload and CO.
Purpose of the Study:
- To evaluate the correlation between various cardiac preload indices and CI in post-cardiac surgery patients.
- To determine if arrhythmias affect the relationship between preload variables and CI.
- To identify reliable indirect markers for cardiac preload assessment.
Main Methods:
- Eighty-six cardiac surgical patients were enrolled, divided into non-arrhythmia (n=72) and arrhythmia (n=14) groups.
- Measurements of cardiac preload variables (RVEDVI, cRVEDVI, IDVGI, filling pressures) and CI were taken on ICU admission and the first two postoperative days.
- Statistical analysis assessed the linear correlation between preload variables and CI, with p < 0.05 considered significant.
Main Results:
- Corrected RV end-diastolic volume index (cRVEDVI) showed a significant linear correlation with CI in both non-arrhythmia (r=0.67) and arrhythmia (r=0.77) groups.
- Index of initial distribution volume of glucose (IDVGI) also demonstrated a linear correlation with CI in both groups (non-arrhythmia: r=0.49; arrhythmia: r=0.61).
- Uncorrected RVEDVI and cardiac filling pressures showed poor or no correlation with CI.
Conclusions:
- cRVEDVI and IDVGI are reliable indicators correlated with CI in cardiac surgery patients, irrespective of arrhythmias.
- These indices show promise as valuable indirect markers for monitoring cardiac preload.
- Accurate preload assessment using cRVEDVI and IDVGI can aid in optimizing hemodynamic management post-cardiac surgery.
Purpose:
Appropriate adjustment of cardiac preload is essential to maintain cardiac output (CO), especially in patients after cardiac surgery. This study was intended to determine whether index of right ventricular end-diastolic volume (RVEDVI), corrected RVEDVI using ejection fraction (cRVEDVI), index of initial distribution volume of glucose (IDVGI), or cardiac filling pressures are correlated with cardiac index (CI) following cardiac surgery in the presence or absence of arrhythmias.
Methods:
Eighty-six consecutive cardiac surgical patients were studied. Patients were divided into two groups: the non-arrhythmia (NA) group (n = 72) and the arrhythmia (A) group (n = 14). Three sets of measurements were performed: on admission to the ICU and daily on the first 2 postoperative days. The relationship between each cardiac preload variable and cardiac index (CI) was evaluated. A p value less than 0.05 indicated statistically significant differences.
Results:
Each studied variable was not different between the two groups immediately after admission to the ICU. cRVEDVI had a linear correlation with CI in both group (NA group: r = 0.67, n = 216, p < 0.001; A group: r = 0.77, n = 42, p < 0.001), but RVEDVI had a poor correlation with CI (NA group: r = 0.27, n = 216, p < 0.001; A group: r = 0.19, n = 42, p = 0.036). IDVGI had a linear correlation with CI (NA group: r = 0.49, n = 216, p < 0.001; A group: r = 0.61, n = 42, p < 0.001), Cardiac filling pressures had no correlation with CI.
Conclusion:
Our results demonstrated that cRVEDVI and IDVGI were correlated with CI in the presence or absence of arrhythmias. cRVEDVI and IDVGI have potential as indirect cardiac preload markers following cardiac surgery.

Related Concept Videos
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac output averages...
 01:05
Pulse
Pulse Rate and its Significance
Pulse rate, often measured in beats per minute (bpm), reflects the heart rate (HR), which is influenced by numerous factors such as stress, physical activity, and hormonal changes. A normal resting adult pulse rate falls between...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send blood...
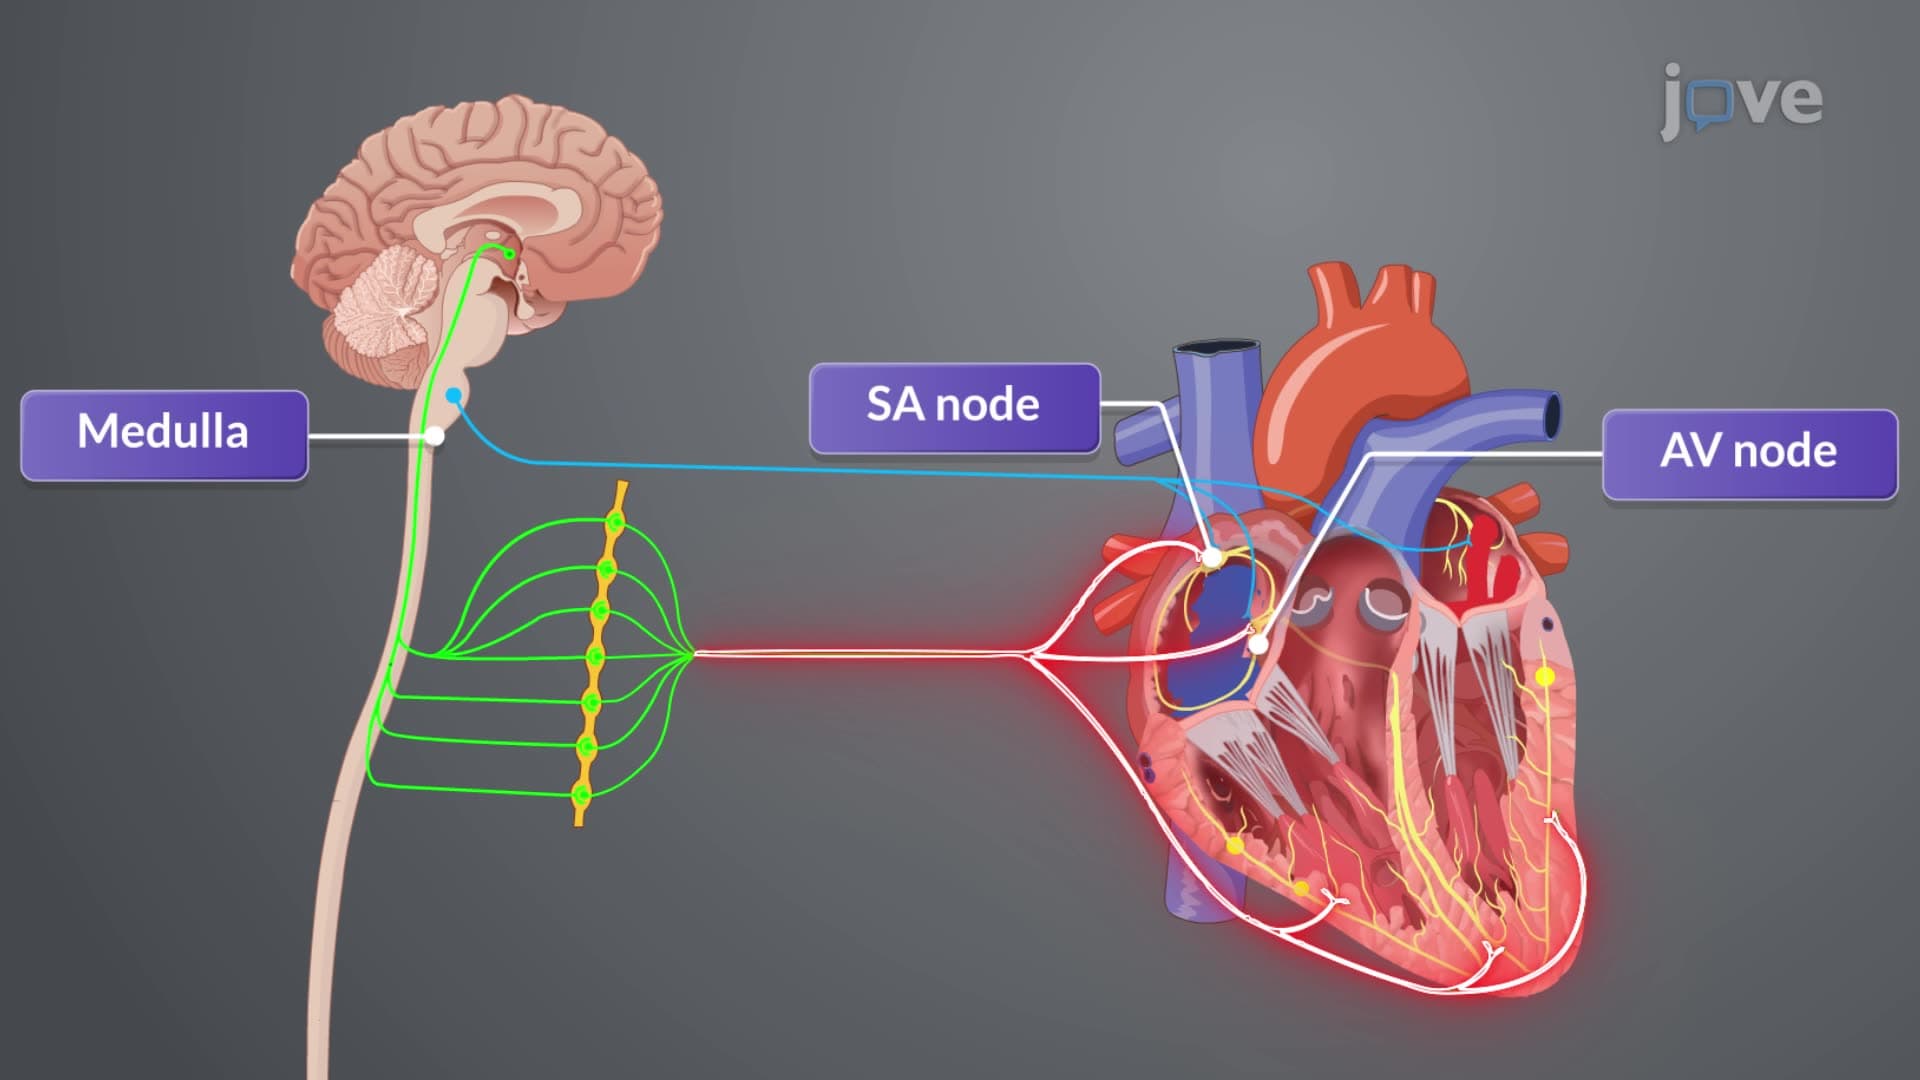 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...