Related Experiment Video
Updated: May 13, 2026
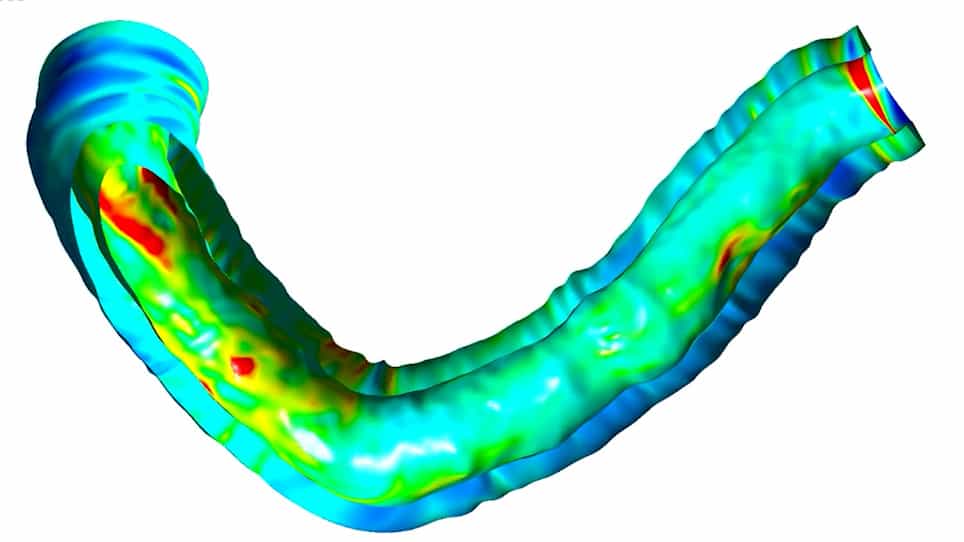

Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Vascular remodeling at both branch ostia in bifurcation disease assessed by intravascular ultrasound
Soo-Jin Kang1, Won-Jang Kim, Sung-Cheol Yun
1Department of Cardiology, University of Ulsan College of Medicine, Asan Medical Center, Seoul, Korea.

Insights
Constrictive remodeling is common in coronary artery bifurcation lesions, even with minimal plaque or calcification. This vascular remodeling contributes to significant luminal narrowing in both main and side branches.
Area of Science:
- Cardiovascular Medicine
- Interventional Cardiology
- Vascular Biology
Background:
- Coronary artery disease (CAD) involves complex lesion morphologies.
- Bifurcation lesions present unique challenges in assessment and treatment.
- Understanding vascular remodeling in these lesions is crucial for optimal outcomes.
Purpose of the Study:
- To evaluate vascular remodeling at main branch (MB) and side branch (SB) ostia.
- To compare remodeling patterns in left main (LM) versus non-LM coronary artery disease.
- To identify factors influencing lumen area in bifurcation lesions.
Main Methods:
- Intravascular ultrasound (IVUS) pullback was used to assess 169 bifurcation lesions.
- Remodeling index (RI) calculated as external elastic membrane (EEM) area at minimal lumen area (MLA) site divided by distal reference EEM area.
- Analysis included LM and non-LM bifurcations with >50% angiographic stenosis.
Main Results:
- Constrictive remodeling (RI < 1) was highly prevalent at both MB and SB ostia in LM (91%, 90%) and non-LM (76%, 92%) bifurcations.
- Lowest RI observed at SB ostia in non-LM bifurcations (0.80 ± 0.13).
- RI was not significantly related to plaque burden or calcification; plaque burden, RI, and distal EEM area independently affected MLA.
Conclusions:
- Constrictive remodeling is frequent at MB and SB ostia in coronary bifurcations, irrespective of plaque amount or calcification.
- This remodeling significantly contributes to further luminal narrowing.
- Findings highlight the importance of assessing vascular remodeling in bifurcation lesions.
Background:
The aim of this study was to assess vascular remodeling at both mainbranch (MB) and sidebranch (SB) ostia in left main (LM), and non-LM coronary artery disease.
Methods:
Using both pullback intravascular ultrasound, MB and SB ostia were evaluated in 169 bifurcation lesions with angiographic stenosis >50% before procedure. Remodeling index (RI) was the ratio of external elastic membrane (EEM) area at the minimal lumen area (MLA) site within the ostium to EEM area of distal reference.
Results:
In 81 LM bifurcation lesions, constrictive remodeling (RI < 1) was frequent at MB and SB ostia (91% and 90%). In 88 non-LM bifurcation lesions, constrictive remodeling was also frequent at the MB and SB ostia (76% and 92%). RI was the lowest at the SB ostium in non-LM bifurcation (0.80 ± 0.13). RI was related to neither large plaque burden nor extensive calcification. The non-LM bifurcation lesions with RI <1 at the SB ostium showed smaller distal carina angle (51 ± 25° vs. 64 ± 14°, P = 0.044) compared with those with RI >1. At all ostial sites of bifurcation lesions, plaque burden and RI at the ostium and EEM area of distal reference were the independent factors affecting the MLA within the corresponding ostium as a continuous variable.
Conclusions:
At both MB and SB ostia, constrictive remodeling was frequent even in the lesions with small amount of plaque and minimal calcification, which contribute further luminal narrowing. © 2012 Wiley Periodicals, Inc.

Related Concept Videos
 01:15
Aortic Regurgitation I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:20
Mitral Regurgitation I: Introduction