Related Experiment Video
Updated: May 13, 2026


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Cervical spine injuries and collar complications in severely injured paediatric trauma patients
M Chan1, W Al-Buali, T Charyk Stewart
1Paediatrics, University of British Columbia, Vancouver, British Columbia, Canada.

Insights
Cervical spine injuries affect 5% of pediatric trauma patients, especially those with traumatic brain injury. Collar complications occurred in 10%, linked to longer hospital stays and delayed clearance.
Area of Science:
- Pediatric Trauma Care
- Spinal Injury Management
- Critical Care Medicine
Background:
- Cervical spine (CS) injuries are a concern in pediatric trauma.
- Understanding the incidence and complications is crucial for patient outcomes.
Purpose of the Study:
- To determine the incidence of cervical spine (CS) injuries in severely injured pediatric trauma patients.
- To identify complications associated with CS collar use in this population.
Main Methods:
- Retrospective registry review of 365 pediatric trauma patients (0-17 years) with Injury Severity Score (ISS) ≥12.
- Analysis of CS injury incidence, suspected injuries, instability, and collar complications.
- Evaluation of factors associated with CS injuries and collar complications, including length of stay and Glasgow Coma Scale (GCS) scores.
Main Results:
- Clinically significant CS injuries occurred in 5% of patients, higher in those with traumatic brain injury (TBI) (9%) and in non-survivors (11%).
- CS collar complications were observed in 10% of patients, primarily erythema or ulcers, often identified around day 6.
- Patients with CS injuries or collar complications had higher ISS, longer intensive care unit (PICU) and hospital stays, and lower GCS scores.
Conclusions:
- CS injuries are prevalent in severely injured pediatric trauma patients, particularly those with TBI and non-survivors.
- CS collar complications are associated with lower GCS scores and prolonged CS clearance times.
- Optimizing CS collar management protocols and considering earlier advanced imaging may reduce complications.
Study Design:
A retrospective registry review.
Objectives:
To determine the incidence of cervical spine (CS) injuries and collar complications in severely injured paediatric trauma patients.
Setting:
Regional Trauma Centre, Children's Hospital.
Methods:
A retrospective review of 365 paediatric severe trauma patients (0-17 years), defined as an Injury Severity Score (ISS)≥12, admitted to the paediatric intensive care unit (PICU).
Results:
Clinically significant CS injuries occurred in 5% (n=18/365) of trauma patients, in 9% (n=13/149) of traumatic brain injury (TBI) patients and in 11% (n=6/56) of in-hospital trauma deaths. CS injuries were suspected before imaging in 33% (n=6/18) of patients based on either motor/sensory impairment or shock. CS injuries were deemed unstable in 61% (n=11/18) of patients. Patients with CS injuries had higher ISS, and longer PICU and hospital stays (P<0.05). CS collar complications occurred in 10% of patients, mainly identified by day 6 and consisting of either erythema or ulcers. Patients with CS collar complications were older and more likely to have TBI, lower Glasgow Coma Scale (GCS) scores, longer PICU and hospital stays, and increased days to CS clearance (P<0.05). Three CS X-rays, together with flexion/extension views, were used most frequently for CS clearance.
Conclusion:
CS injuries were prevalent in severely injured paediatric trauma patients, particularly in those with TBI and in nonsurvivors. CS collar complications were associated with a lower GCS and longer CS clearance times. Attention to CS collar management protocols and earlier CS clearance with computed tomography/magnetic resonance imaging in obtunded patients might reduce CS collar complications.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:14
Spinal Cord Injury ll: Pathophysiology
 01:16
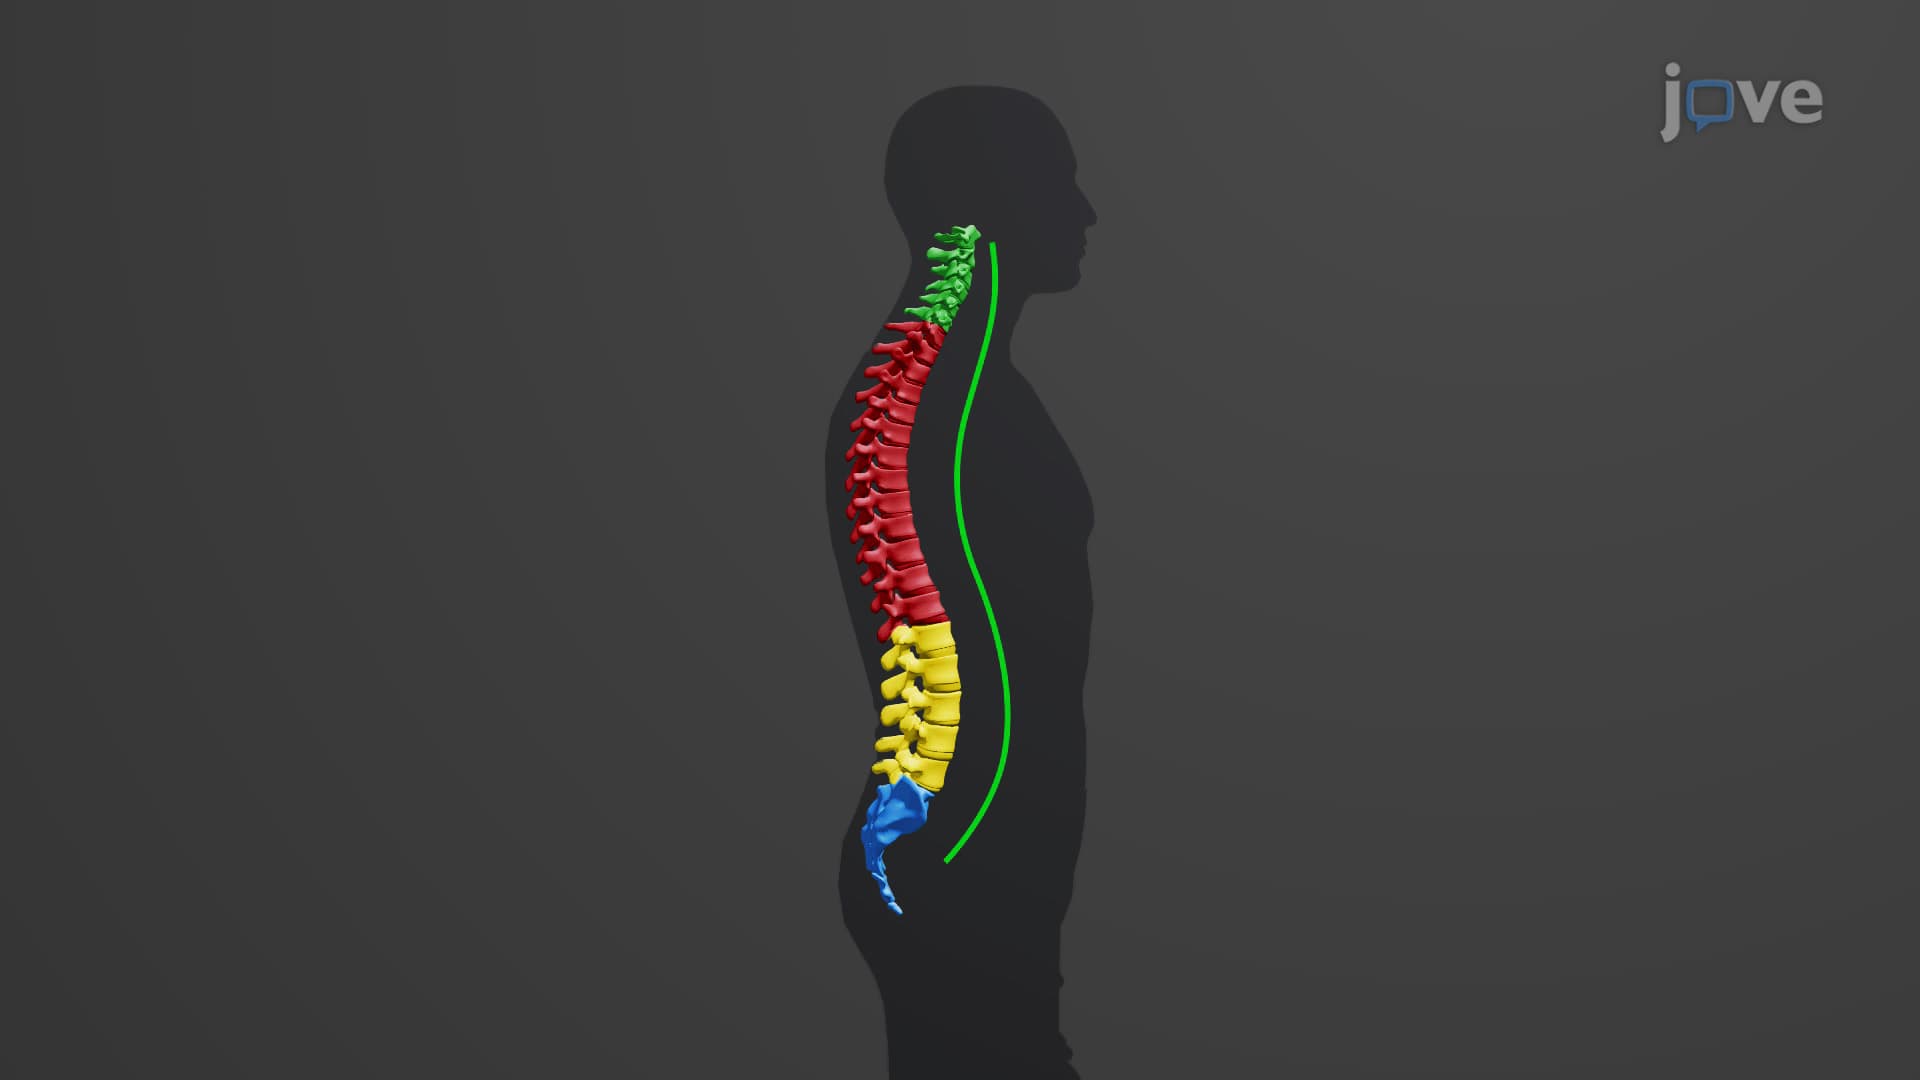
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the procedure...