Obliterative lower airway lesions in childhood: bronchoscopic diagnosis and clinical spectrum
Related Experiment Video
Updated: May 13, 2026
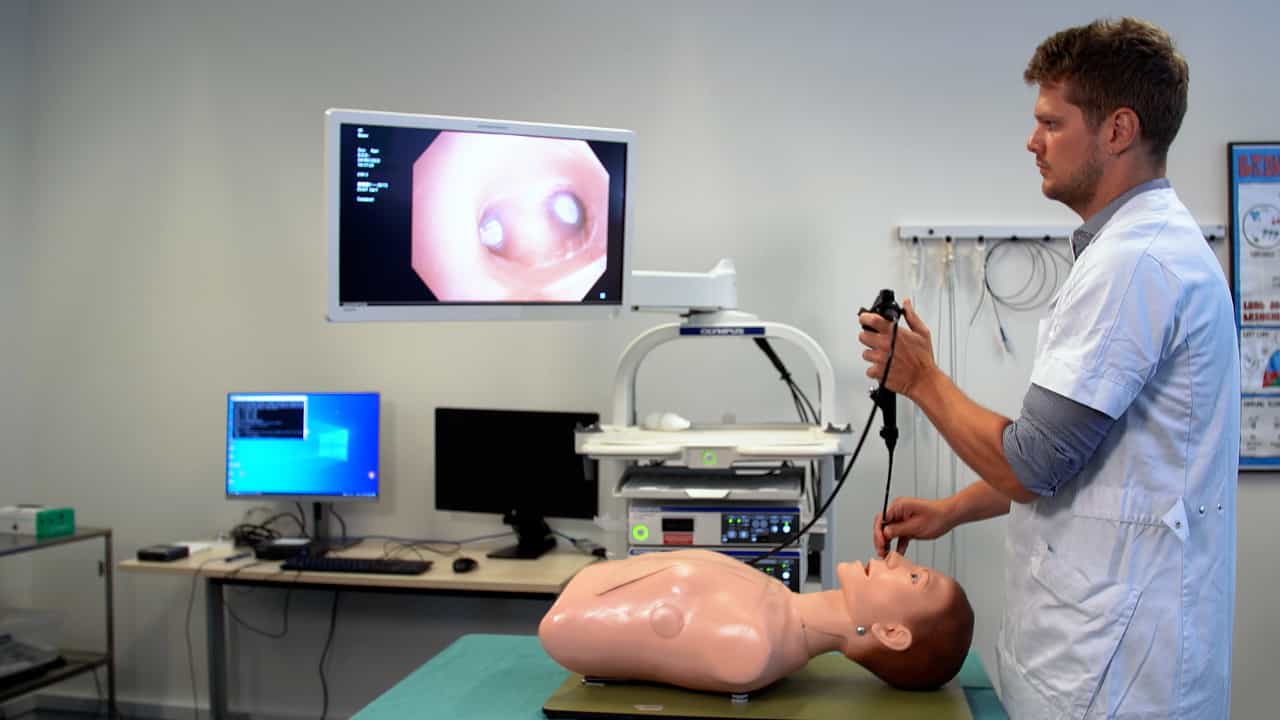
Systematic Bronchoscopy: the Four Landmarks Approach
Published on: June 23, 2023
Annabelle Quizon1, Pedrag Minic, Petr Pohunek
1Division of Pediatric Pulmonology, University of Miami-Miller School of Medicine, Miami, Florida.

Insights
This study expands understanding of large airway obliteration, identifying non-suppurative infections and immunosuppression as potential causes beyond cystic fibrosis. Bronchoscopy is highlighted for diagnosing these rare airway lesions.
Area of Science:
- Pulmonology
- Pediatric Respiratory Medicine
Background:
- Previous reports detailed airway abnormalities in children with chronic lung disease and cystic fibrosis.
- A common theory suggests inflammation leads to granulation tissue, pyogenic granuloma, and fibrosis, causing airway obliteration.
Observation:
- This series presents four cases of large airway obliteration.
- Conditions included non-suppurative chronic infections and potential immunosuppression.
- Bronchoscopy, including ultrathin scopes, visualized airway lumen obliteration.
Findings:
- Transbronchial intervention was unsuccessful in three cases.
- One case showed spontaneous resolution of airway obliteration.
- This suggests acquired obliterative airway lesions are a broader clinical entity.
Implications:
- Bronchoscopy is crucial for diagnosing and potentially intervening in these underrecognized airway lesions.
- Acquired airway obliteration should be considered in patients with non-resolving pulmonary infiltrates or impaired airway patency.
- The findings broaden the differential diagnosis for airway obstruction in pediatric and adult populations.
Abstract:
Previous reports have described structural airway abnormalities in children with non-cystic fibrosis chronic supportive lung disease as well as obliterative membranes in the major bronchi of cystic fibrosis patients. The putative paradigm proposed in the evolution of these membranes invokes intense inflammation resulting in granulation tissue and neovascularization with the formation of pyogenic granuloma and eventually fibrosis. Our series of four cases widens the spectrum of conditions that may be conducive to large airway obliteration to include non-suppurative chronic infections and possibly immunosuppression. Obliteration of lumina in proximal and distal airways was visualized on bronchoscopy, the latter by the use of the ultrathin bronchoscopes. An attempt at invasive intervention by transbronchial breaching of the obstruction was unsuccessful in three cases, and in one case, the obliterative process resolved spontaneously and without any radiologic trace, presumably by resorption or rupture or through development of collateral ventilation. This series highlights the use of bronchoscopy for diagnosis and occasionally for therapeutic intervention in hitherto little recognized obliterative airway lesions. These acquired obliterative lesions should be considered in the evaluation of patients with isolated non-resolving pulmonary infiltrates or other conditions in which bronchial and bronchiolar patency may be impaired.
Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:23
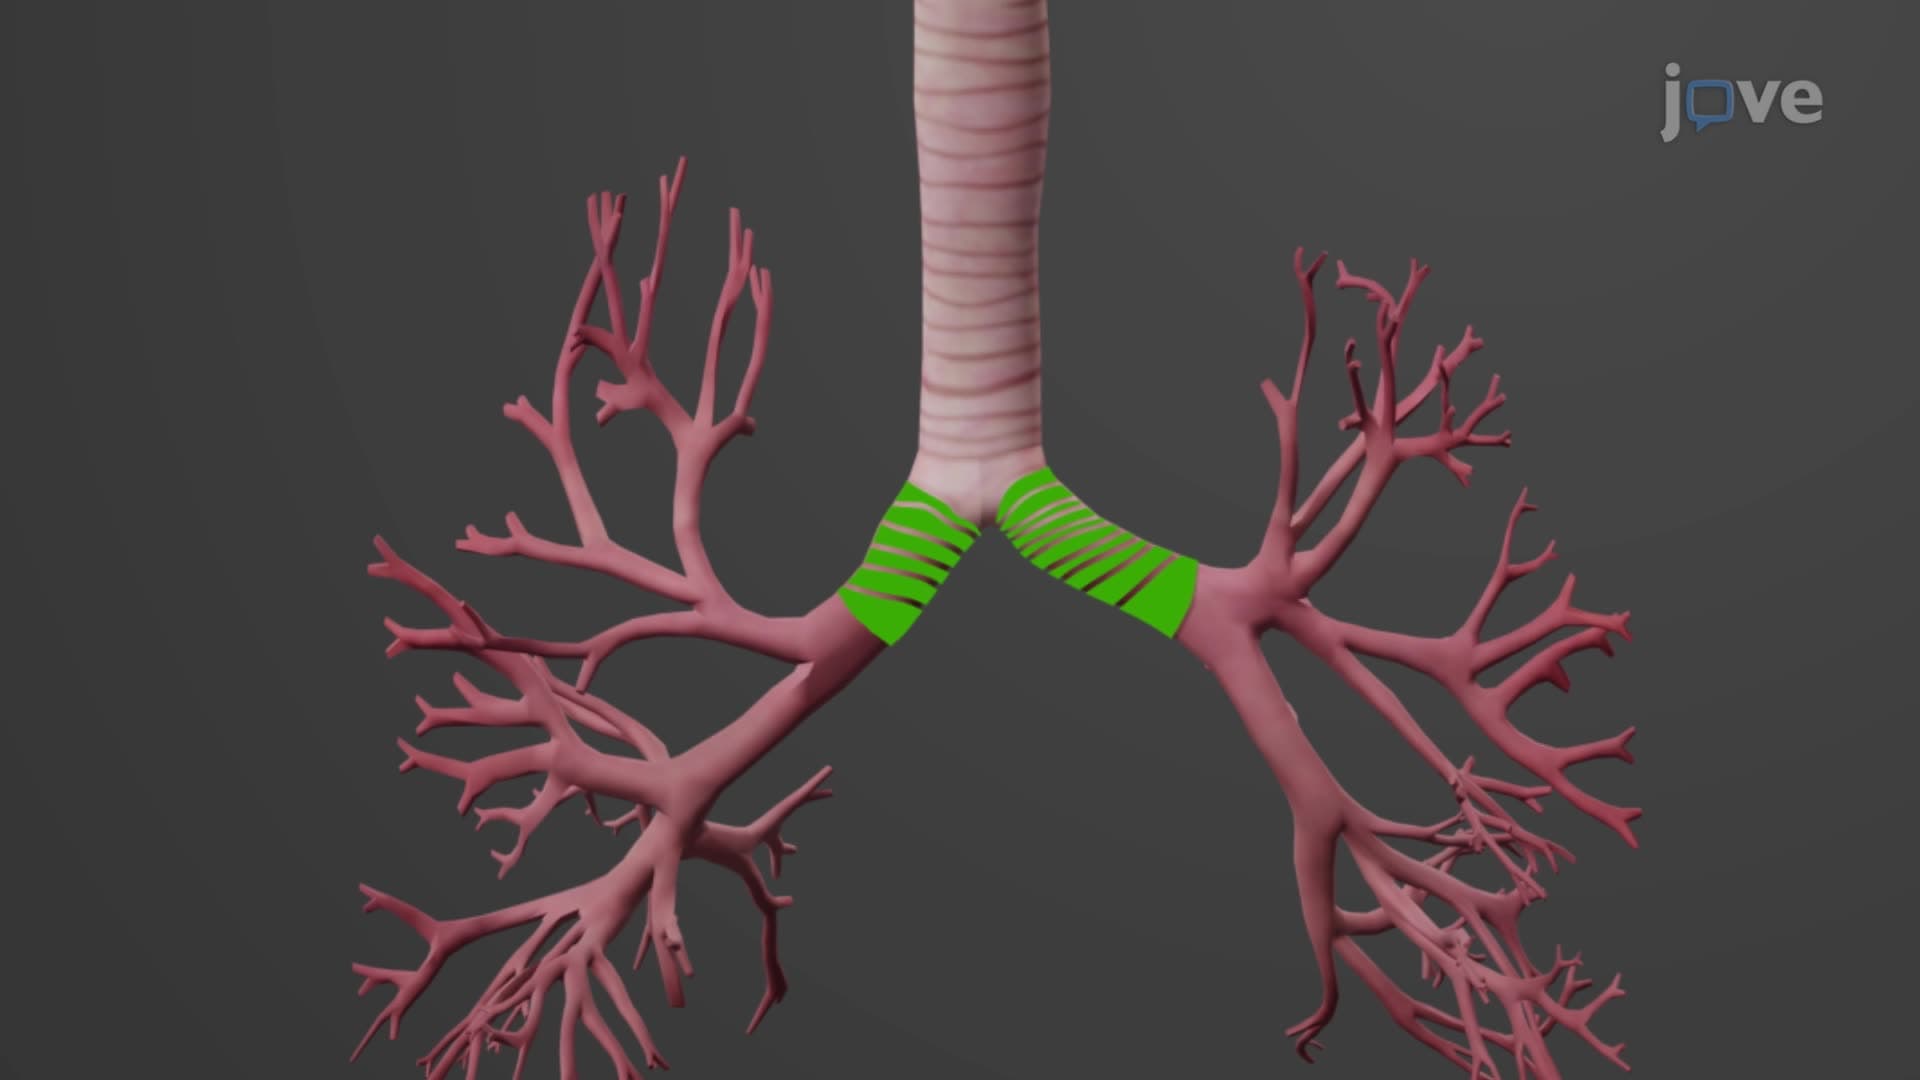
The Bronchial Tree
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations
 01:13
Asthma III: Clinical Manifestations
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include: