Related Experiment Video
Updated: May 13, 2026
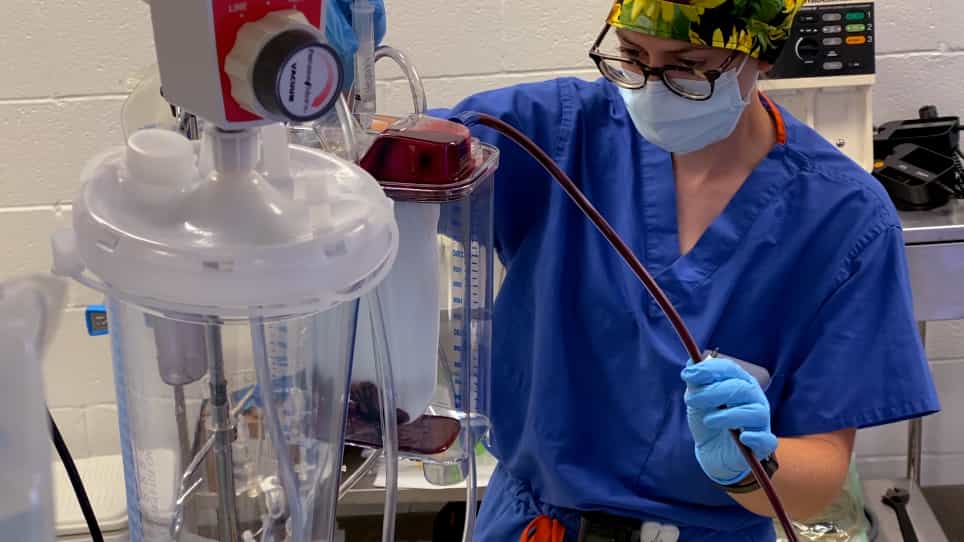

A Porcine Heterotopic Heart Transplantation Protocol for Delivery of Therapeutics to a Cardiac Allograft
Published on: February 14, 2022
[Heart transplantation and the subsequent treatment of AL amyloidosis]
1Interni hematologicka a onkologicka klinika LF MU a FN Brno, Pracoviste Bohunice. z.adam@fnbrno.cz

Insights
For patients with severe heart damage from AL amyloidosis, heart transplantation before chemotherapy improves treatment outcomes. This approach enables intensive AL amyloidosis treatment, offering hope for long-term remission.
Area of Science:
- Cardiology
- Hematology
- Oncology
Background:
- Severe heart damage from AL amyloid deposits contraindicates high-dose chemotherapy with autologous hematopoietic stem cell transplantation.
- AL amyloidosis-induced cardiac damage leads to life-threatening complications, often disrupting treatment schedules.
Observation:
- Heart transplantation was performed in three patients with AL amyloidosis-induced cardiac damage.
- Patients underwent assessment for AL amyloidosis treatment 3-6 months post-transplant.
- Chemotherapy regimens were adapted based on patient response and disease markers.
Findings:
- High-dose chemotherapy with melphalan and autologous stem cell transplantation was tolerated post-heart transplant.
- While not all patients achieved complete remission with initial therapy, subsequent treatments led to remission in some.
- One patient achieved complete hematologic remission with bortezomib-based therapy.
- Another patient achieved a very good partial remission with lenalidomide-based therapy.
- A third patient achieved complete hematologic remission, likely due to post-transplant immunosuppressive treatment.
Implications:
- Performing heart transplantation before AL amyloidosis treatment is beneficial for patients with severe cardiac involvement.
- A 3-month interval post-transplant allows for patient stabilization and assessment before initiating intensive AL amyloidosis therapy.
- Autologous stem cell harvesting and high-dose chemotherapy can be considered in suitable patients post-transplant.
- Alternative therapies are crucial if initial intensive treatment fails to induce remission.
Unlabelled:
Severe damage to the heart caused by AL amyloid deposits is a contraindication of high-dose chemotherapy with autologous haematopoietic stem cell transplantation. Severe heart damage caused by AL amyloid results in frequent life-threatening complications, even during the course of the classical chemotherapy treatment and it often makes keeping to the treatment schedule impossible. Scheduling heart transplantation before the treatment of AL amyloidosis will significantly improve the patients overall condition and enable them to undergo the intensive AL amyloidosis treatment with the hope that a long-term complete remission may be achieved.
Case Descriptions:
Transplantations of heart damaged by AL amyloid deposits were conducted in three patients; two men, age 48 and 54, and one woman, age 63. In the interval of 3-6 months from the heart transplantation before the scheduled AL amyloidosis treatment was initiated, an examination of bone marrow, the concentration of monoclonal immunoglobulin and free light chains was carried out. Both men had more than 10% of plasma cells in the bone marrow after the heart transplantation and the concentrations of the λ free light chains were pathologically increased. During the first-line therapy, autologous haematopoietic stem cells were harvested from peripheral blood after mobilizaton with granulocyte growth factor (filgrastim) at the dose of 5 µg/kg twice a day. During the administration of filgrastim until the end of the haematopoietic stem cell harvest, the combined immunosuppressive treatment was reduced and a corticosteroid dose was compensatory increased. The prophylactic antiviral drug valganciclovir was discontinued during the haematopoietic stem cell harvest. High-dose chemotherapy (melphalan 100 mg/m2) with autologous haematopoietic stem cell transplantation followed. In the interval from administering melphalan until the rise in neutrophil count over 2 x 10⁹/l, antiviral prophylaxis was discontinued again, the immunosuppressive drug doses were reduced and corticoid doses were slightly increased. High-dose chemotherapy with melphalan at the of 100 mg/m2 was tolerated without major complications and without mucositis; however, in neither of the male patients did it lead to a complete haematological remission. Consequently, the second-line therapy followed using bortezomib combined with dexamethasone and also with cyclophosphamide or doxorubicin. One of these two patients reached a complete haematological remission after the bortezomib therapy; the values of free light chains were normal, immunofixation was negative, and clonal plasma cells were absent in the bone marrow. In the case of the other patient, the bortezomib therapy only induced partial remission. In this case, the third-line therapy followed, applying a combination of lenalidomide, dexamethasone and cyclophosphamide. This therapy significantly reduced the values of free light chains; however, their ratio remained pathological. To conclude, the latter response can be described as a very good partial remission. Both men currently show no signs of disease activity and are in a good clinical condition 28 and 30 months after the heart transplantation. The third heart transplantation, due to severe heart damage by AL amyloid deposits, was conducted in a woman aged 63. An examination of this woman three months after the heart transplantation showed that the original pathological values of free light chains became normal. The woman had approx. 8% of clonal plasma cells before the heart transplantation. Three months after the heart transplantation the bone marrow contained only 3% of polyclonal plasma cells. In this case, the immunosuppressive treatment with corticosteroids after the heart transplantation probably induced a complete haematologic remission. The woman is in a complete AL amyloidosis remission seven months after the heart transplantation.
Conclusion:
It was beneficial to perform the heart transplantation first and to initiate the AL amyloidosis treatment no sooner than three months after the heart transplantation in patients with severe heart damage caused by AL amyloid deposits. If the patients are in a good clinical conditions, autologous haematopoietic stem cells can be harvested after the heart transplantation and high-dose chemotherapy can be offered to the patients. If this intensive treatment does not induce remission, it is necessary to apply additional alternative treatments.

Related Concept Videos
 01:29
Cardiomyopathy V: Interprofessional Care
 01:22
Heart Failure VI: Adjunct Therapies
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy