Related Experiment Video
Updated: May 13, 2026
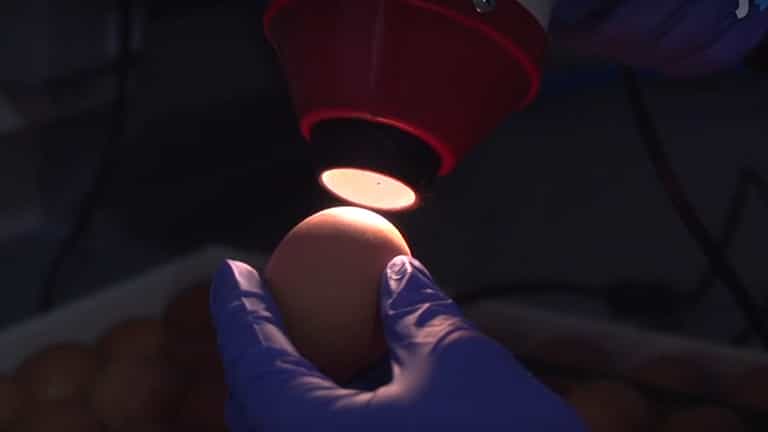

An In Ovo Model for Testing Insulin-mimetic Compounds
Published on: April 23, 2018
A novel insulin mimetic vanadium-flavonol complex: synthesis, characterization and in vivo evaluation in STZ-induced
Subramanian Iyyam Pillai1, Sorimuthu Pillai Subramanian, Muthusamy Kandaswamy
1Department of Inorganic Chemistry, University of Madras, Guindy Campus, Chennai 600 025, Tamil Nadu, India.

Abstract:
Since 1985, when Heyliger et al., first demonstrated a serendipitous discovery that oral administration of 0.8 mg/ml of sodium orthovanadate in drinking water to streptozotocin-induced diabetic rats resulted in normoglycemia, numerous extensive studies have been pursued on the anti-diabetic and insulinomimetic actions of vanadium. The acceptance of vanadium compounds as promising therapeutic antidiabetic agents has been slowed due to the concern for chronic toxicity associated with vanadium accumulation. In order to circumvent the toxic effects of vanadium, we have taken up a combinational approach wherein a novel vanadium-flavonol complex was synthesized, characterized and its toxic as well as insulin mimetic potential was evaluated in STZ-induced experimental diabetes in rats. The results indicate that the complex is non-toxic and possess anti-diabetic activity.
Insights
Researchers developed a novel vanadium-flavonol complex to treat diabetes. This non-toxic compound effectively lowers blood glucose levels in diabetic rats, offering a promising alternative to traditional vanadium therapies.
Area of Science:
- Biochemistry
- Pharmacology
- Toxicology
Background:
- Vanadium compounds show anti-diabetic and insulinomimetic potential, first observed in 1985.
- Concerns regarding chronic toxicity and vanadium accumulation have hindered clinical acceptance.
- A novel approach is needed to harness vanadium's benefits while mitigating risks.
Purpose of the Study:
- To synthesize and characterize a novel vanadium-flavonol complex.
- To evaluate the toxicological profile of this complex.
- To assess its anti-diabetic and insulin mimetic potential in experimental diabetes.
Main Methods:
- Synthesis and characterization of a new vanadium-flavonol complex.
- Toxicological evaluation in a rat model.
- Assessment of anti-diabetic activity in streptozotocin-induced diabetic rats.
Main Results:
- The synthesized vanadium-flavonol complex demonstrated non-toxicity.
- The complex exhibited significant anti-diabetic activity.
- Insulin mimetic potential was observed, suggesting therapeutic efficacy.
Conclusions:
- The novel vanadium-flavonol complex is non-toxic and possesses anti-diabetic properties.
- This complex represents a promising therapeutic strategy for managing diabetes.
- Further research into vanadium-flavonol complexes could lead to safer anti-diabetic treatments.


Related Concept Videos
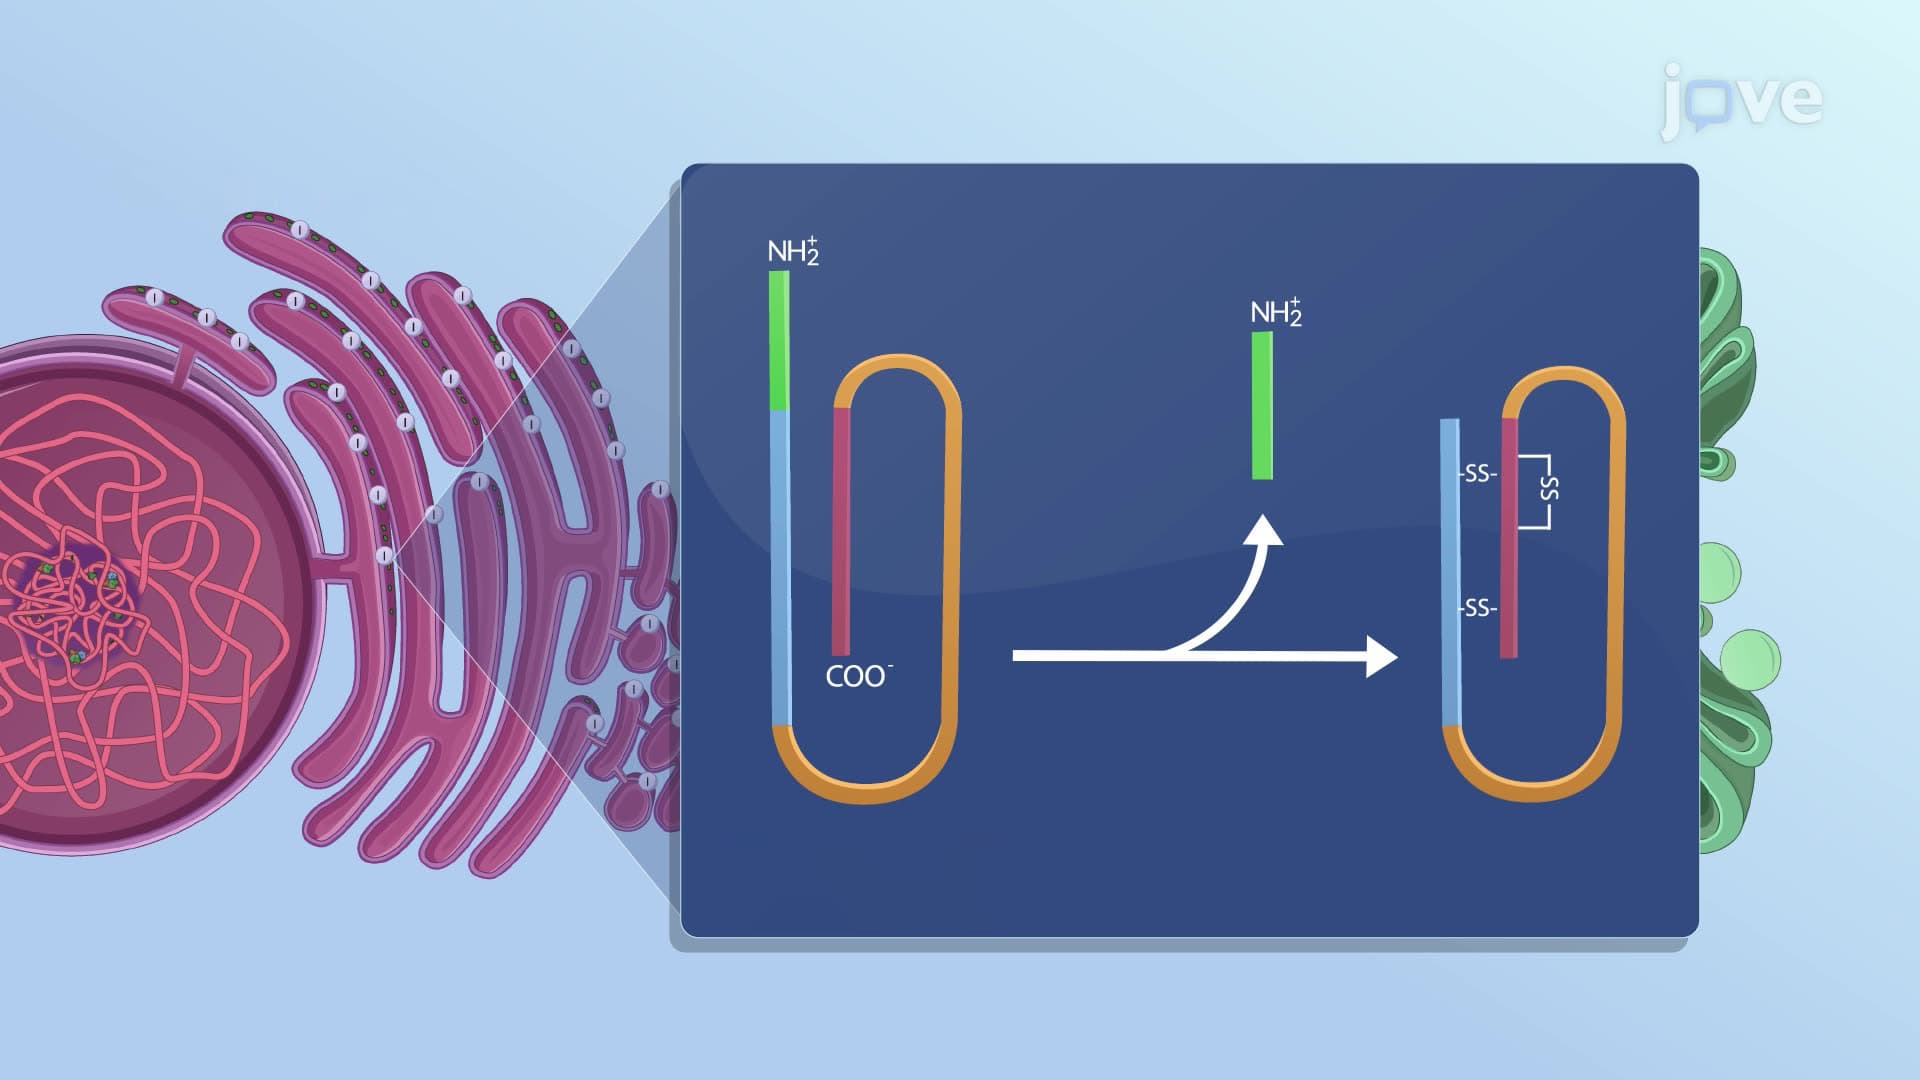 01:25
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:26
Oral Hypoglycemic Agents: Biguanides and Glitazones
 01:26
Diabetes Mellitus: Introduction
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:24
Type II Diabetes II: Pathophysiology
 01:25
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis