

Myocardial perfusion and the J curve association between diastolic blood pressure and mortality
Martin G Schultz1, Walter P Abhayaratna, Thomas H Marwick
1Menzies Research Institute Tasmania, University of Tasmania, Hobart, Australia.

Insights
Brachial diastolic blood pressure (DBP) is not a reliable indicator of subendocardial perfusion. The observed J-curve effect linking DBP to mortality is unlikely due to reduced heart blood flow or central hemodynamic issues.
Area of Science:
- Cardiology
- Physiology
- Medical Research
Background:
- The J-curve relationship between brachial diastolic blood pressure (DBP) and mortality is hypothesized to be linked to reduced myocardial perfusion.
- This study investigates the connection between DBP and subendocardial perfusion.
Purpose of the Study:
- To determine the relationship between DBP and subendocardial perfusion in patients with and without coronary artery disease (CAD).
- To examine central hemodynamic variables (aortic stiffness, central pulse pressure, augmentation index) potentially explaining the risk associated with low DBP.
Main Methods:
- Brachial DBP and radial tonometry were measured in 134 CAD patients, 134 control subjects, and 47 patients during dobutamine stress echocardiography.
- Central hemodynamics and subendocardial viability ratio (SEVR) were recorded.
- SEVR served as the marker for subendocardial perfusion.
Main Results:
- No significant differences in DBP or SEVR were found between control subjects and CAD patients.
- SEVR did not differ across DBP quartiles in either group.
- Associations between DBP and SEVR were attenuated after adjustments.
- DBP did not correlate significantly with central hemodynamics.
- SEVR was reduced in patients with inducible ischemia during stress, but DBP was not significantly different.
Conclusions:
- Brachial DBP is an inadequate marker for assessing subendocardial perfusion.
- The J-curve relationship between DBP and mortality is unlikely explained by reduced myocardial perfusion or adverse central hemodynamics.
Background:
The J-curve relationship between brachial diastolic blood pressure (DBP) and mortality is believed to be mediated through reduced myocardial perfusion. This study aimed to determine the relationship between DBP and subendocardial perfusion in patients with and without coronary artery disease (CAD) and to examine central hemodynamic variables that may explain the risk associated with low DBP (aortic stiffness, central pulse pressure, and augmentation index).
Methods:
Brachial DBP and radial tonometry were measured in 134 patients with CAD (aged 76±7years; 69% male), 134 individuals without a prior cardiovascular event (control subjects) (aged 77±2years; 69% male) and 47 patients (aged 63±10years) during dobutamine stress echocardiography. Central hemodynamics and subendocardial viability ratio (SEVR), a marker of subendocardial perfusion, were recorded by tonometry.
Results:
There was no difference in DBP or SEVR between control subjects and CAD patients (P > 0.05), nor was there a difference in SEVR across quartiles of DBP in CAD patients (P = 0.07) or control subjects (P = 0.14). After adjustment for age and height, associations between DBP and SEVR in control subjects (r = 0.185; P = 0.03) and CAD patients (r = 0.204; P = 0.02) were attenuated (P = 0.07 and P = 0.11, respectively). There were no significant relationships between DBP and central hemodynamics (P > 0.05 for all). At peak dobutamine stress, SEVR was significantly reduced in patients with inducible ischemia vs. those with nonischemic response (84±17 vs. 101±22%; P = 0.01). However, DBP was not significantly different (65±14 vs. 67±15mm Hg; P = 0.32).
Conclusions:
Brachial DBP is a poor marker of subendocardial perfusion. The J-curve relationship between DBP and mortality is unlikely attributable to reduced myocardial perfusion or adverse central hemodynamics.
More Related Videos


Related Concept Videos
 01:17
Measurement of Blood Pressure
 01:19
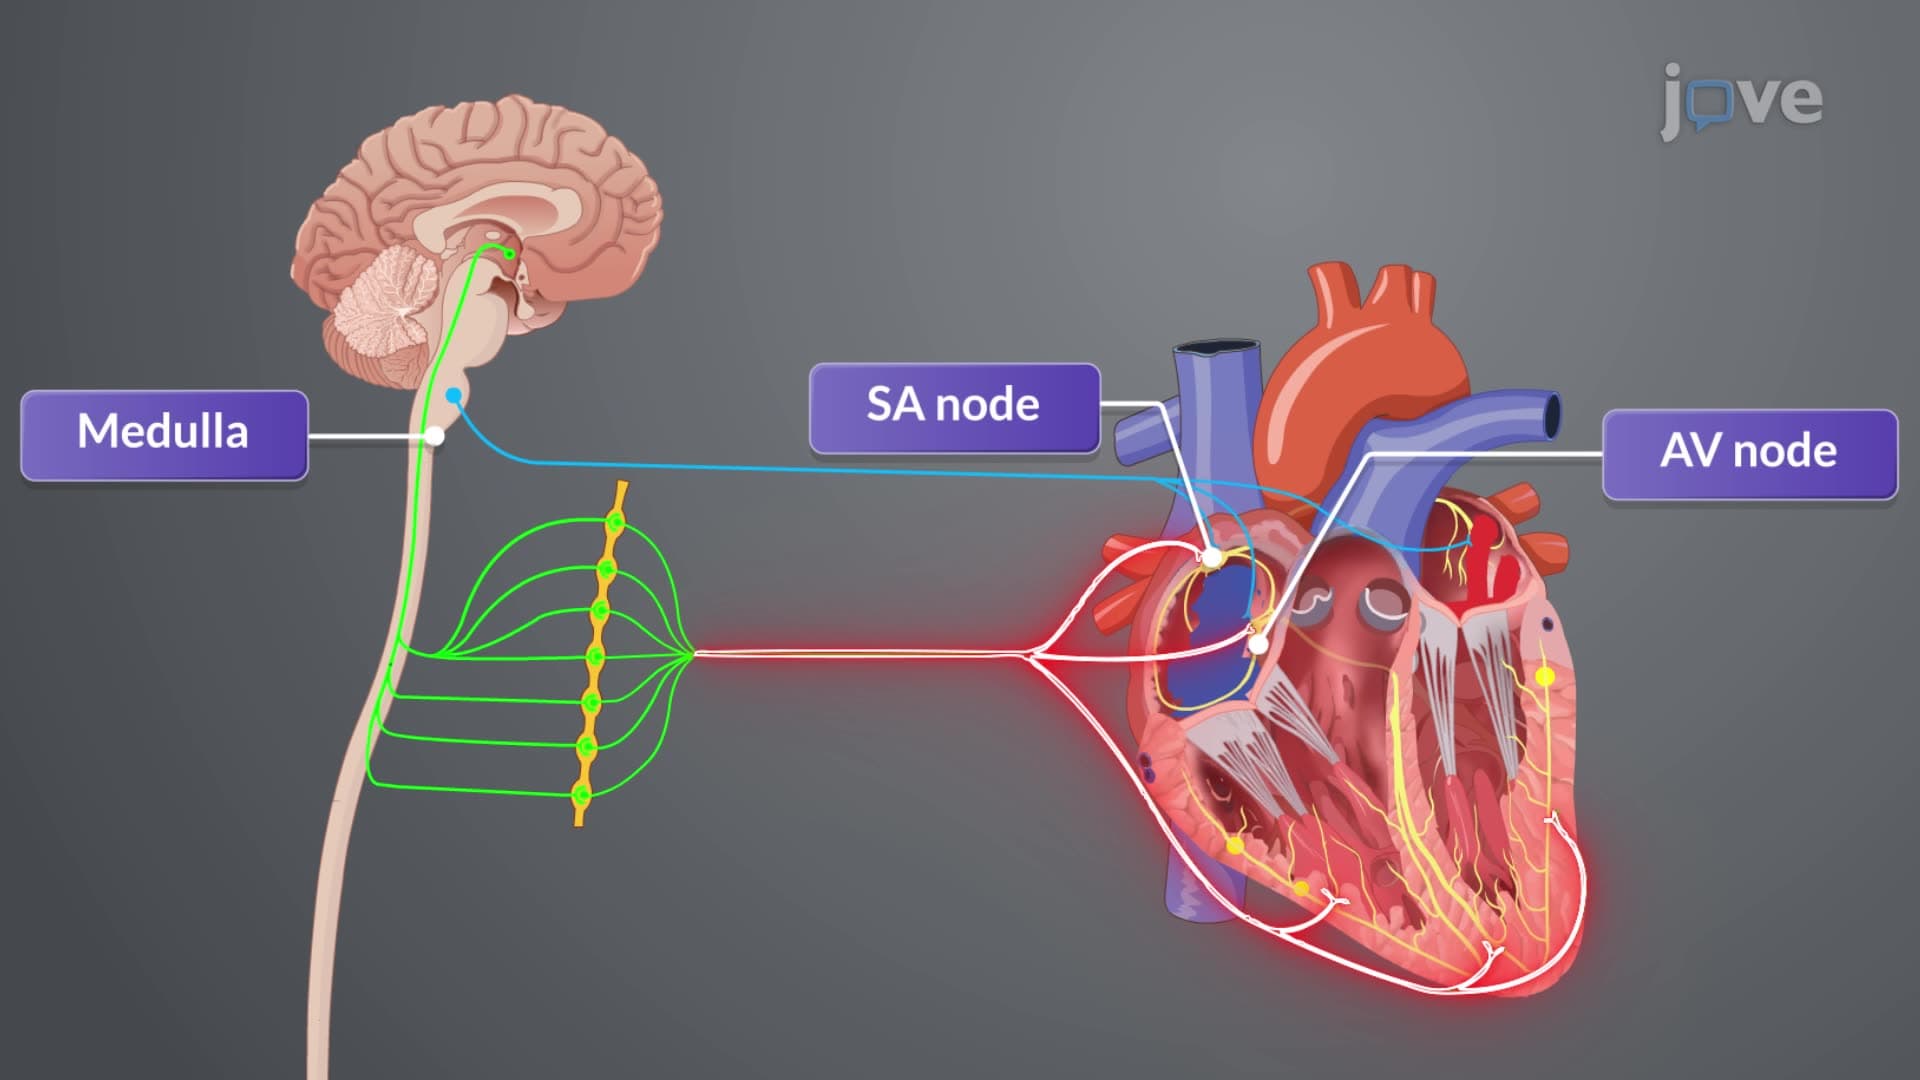
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:26
Coronary Artery Disease II: Pathophysiology
 01:24
Blood Pressure
 01:29
Hypertension II: Pathophysiology